| Program Name: | BadgerCare Plus and Medicaid | Handbook Area: | Pharmacy | | 09/06/2026 | Prior Authorization : Services Requiring Prior AuthorizationTopic #23777 Alhemo
Clinical PA is required for Alhemo.
PA requests for Alhemo must be completed, signed, and dated by the prescriber. PA requests for Alhemo must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Alhemo must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Alhemo may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Alhemo
Clinical criteria that must be documented for approval of a PA request for Alhemo are all of the following:
- The member's age must be consistent with FDA-approved product labeling for Alhemo.
- Alhemo must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- One of the following is true:
- The member has hemophilia A (congenital factor VIII deficiency) with or without factor VIII inhibitors.
- The member has hemophilia B (congenital factor IX deficiency) with or without factor IX inhibitors.
- One of the following is true:
- The member has severe hemophilia (factor activity less than 1%).
- The member experienced two or more episodes of spontaneous bleeding into joints.
- The prescriber will dose optimize four weeks after initiation by measuring concizumab-mtci plasma concentration utilizing concizumab ELISA prior to administration of the next scheduled dose.
- Alhemo will not be used for the treatment of breakthrough bleeds. (Note: Bypassing agents [for example, rFVIIa or aPCC] may be administered on an as-needed basis for the treatment of breakthrough bleeds in patients being treated with Alhemo.)
- Female patients of reproductive potential are not pregnant prior to initiating therapy with Alhemo and will use a highly effective form of contraception during treatment with Alhemo and for seven weeks after ending treatment.
- The prescription is written by or through consultation with a hematologist.
Supporting clinical information and a copy of the member's current medical records must be included with all PA requests for Alhemo. The supporting clinical information and the medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Alhemo are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Alhemo may be approved for up to 365 days. Renewal PA requests must include supporting clinical information and copies of the member's current medical records demonstrating that the member has had a reduction in the frequency of bleeding episodes since starting treatment with Alhemo.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #23658 Casgevy
Clinical PA is required for Casgevy.
If a PA request for Casgevy is approved, Casgevy will be covered under the pharmacy benefit. To bill ForwardHealth for Casgevy, pharmacy providers should submit a pharmacy noncompound drug claim and include the member's diagnosis code on the pharmacy claim submitted for Casgevy. The DOS submitted on the pharmacy claim must be the date the member received the infusion of Casgevy.
For specific questions about the billing or coverage of high cost, orphan, and accelerated approval drugs, providers may contact Provider Services or email DHSOrphanDrugs@dhs.wisconsin.gov.
Casgevy Cell and Gene Therapy Access Model Requirements for Treatment Centers
Casgevy is a State-Selected Model Drug in the CMS'
CGT
Access Model when used for the treatment of SCD. Casgevy used for β-thalassemia is not included in the CGT Access Model at this time.
The treatment center must agree to all of the following for members determined to be eligible in the CGT Access Model:
- Treatment center providers administering Casgevy for SCD must enroll and participate in the CMS-Designated Patient Registry through CIBMTR.
- Treatment center providers must be enrolled in CIBMTR before administering Casgevy to Wisconsin Medicaid members.
- Treatment center providers must also obtain member consent to participate in the CIBMTR Research Database Protocol under which this study will be governed and are responsible for submitting data to CIBMTR, per the CGT Access Model study requirements.
- Treatment center providers administering Casgevy for SCD must ensure Casgevy is not purchased through the 340B Drug Pricing Program (340B Program) when administered to eligible CGT Access Model members.
For assistance with enrollment in the CMS-Designated Patient Registry for the CMS CGT Access Model, providers may email CIBMTR at CGTModel@mcw.edu.
Requirements for Casgevy
Casgevy will be reimbursed separately from physician and clinical services associated with the administration of Casgevy. The pharmacy provider is required to establish a delivery process with the prescriber to ensure that the physician-administered Casgevy is delivered directly to the administering treatment center.
Pharmacy providers may only submit a claim to ForwardHealth for Casgevy that has been administered to a member. If Casgevy has been dispensed for a member but the dose is not administered to the member, the prescriber is responsible for notifying the dispensing pharmacy. If ForwardHealth has paid the dispensing pharmacy for any portion of the dispensing of Casgevy that is not administered to the member, the dispensing pharmacy is responsible for reversing any claims submitted to ForwardHealth.
Casgevy must be prescribed at a minimum recommended dose of 3.0 x 10⁶ CD34+ cells/kg of body weight.
The member must have full myeloablative conditioning administered before infusion of Casgevy. Full myeloablative conditioning must be administered between 48 hours and seven days before infusion of Casgevy.
Standard procedures for patient management after HSC transplantation should be followed after Casgevy infusion.
The prescriber must manage other concomitant medications (as applicable) consistent with FDA product labeling.
The member must not take disease-modifying therapies (for example, crizanlizumab, hydroxyurea, L-glutamine, voxelotor) for at least two months prior to mobilization.
The member must not take iron chelation therapy at least seven days prior to myeloablative conditioning. The member must not take non-myelosuppressive iron chelators for at least three months and myelosuppressive iron chelators for at least six months after Casgevy infusion.
Additional Requirement for Casgevy for Sickle Cell Disease Treatment
G-CSF must not be used prior to or with mobilization and conditioning.
PA Information for Casgevy
Conditions for Which PA Requests for Casgevy Will Be Considered for Review
ForwardHealth will only consider PA requests for Casgevy for the following clinical conditions:
Clinical Criteria for Casgevy for β-Thalassemia
The clinical criteria that must be documented for approval of a PA request for Casgevy for β-thalassemia are all of the following:
- Casgevy must be prescribed and administered by a physician and treatment center with expertise in treating β-thalassemia with Casgevy.
- The member has β-thalassemia, which requires regular RBC transfusions. The member has a history of transfusions for the past two years of at least 100 mL/kg/year of packed RBCs or at least 10 units/year of RBC transfusions in the previous two years.
- The member's age at the time of the planned infusion is consistent with the FDA-approved product labeling for Casgevy.
- The prescriber will provide documentation of completed negative screening for active infectious diseases including HBV, HCV, HIV 1 and 2 (HIV-1/HIV-2) and HTLV 1 and 2 (HTLV-1/HTLV-2), in accordance with clinical guidelines before collection of cells for manufacturing.
- The prescriber has attested that the member is clinically stable and fit for transplantation.
Clinical Criteria for Casgevy for Sickle Cell Disease
The clinical criteria that must be documented for approval of a PA request for Casgevy for SCD are all of the following:
- Casgevy must be prescribed and administered by a physician and treatment center with expertise in treating SCD with Casgevy.
- The prescribing provider attests that at least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response with hydroxyurea.
- The member has experienced a clinically significant adverse drug reaction with hydroxyurea.
- There is a clinically significant drug interaction between another drug(s) the member is taking and hydroxyurea.
- The member has a medical condition(s) that prevents the use of hydroxyurea.
- The prescribing provider attests that the member has SCD with a history of two or more VOEs per year within the previous 24 months or is currently receiving chronic transfusion therapy for recurrent VOCs (based on provider attestation).
- The member's age at the time of the planned infusion is consistent with the FDA-approved product labeling for Casgevy.
- The prescriber will provide documentation of completed negative screening for active infectious diseases including HBV, HCV, HIV 1 and 2 (HIV-1/HIV-2), and HTLV 1 and 2 (HTLV-1/HTLV-2) in accordance with clinical guidelines before collection of cells for manufacturing.
- The prescriber has attested that the member is clinically stable and fit for transplantation.
Conditions Not Approved for PA Requests for Casgevy
PA requests for Casgevy for β-thalassemia or SCD will not be approved if the member has any of the following conditions:
- Advanced liver disease that, in the opinion of the prescriber, renders the member not clinically fit and stable for transplantation
- A history of untreated Moyamoya disease or the presence of Moyamoya disease that, in the opinion of the prescriber, puts the member at risk of bleeding
- Current malignancy, myeloproliferative disorder, or significant immunodeficiency disorder, unless the prescribing provider attests that the member's condition would not deem the member ineligible for treatment
- Prior allogenic or autologous HSC transplant
Submitting PA Requests for Casegevy
PA requests for Casgevy must be completed, signed, and dated by the prescriber. PA requests for Casgevy must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Casgevy must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Casgevy may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
PA requests for Casgevy will be approved for 365 days.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug. Topic #24044 Cell and Gene Therapy Access Model
The Wisconsin DHS is participating in the CMS' CGT Access Model. This model allows DHS to enter into agreements with the manufacturers of two State-Selected Model Drugs for SCD:
Qualifications for BadgerCare Plus and Medicaid Members' Participation
Certain BadgerCare Plus and Medicaid members' treatment with these drugs will qualify for receiving it through the CGT Access Model. The Model cannot include members eligible under the separate CHIP portion of Badger Care Plus.
To be eligible, members must:
- Have a documented medical diagnosis of SCD.
- Have Wisconsin Medicaid as the primary payer for a State-Selected Model Drug.
- Have received an infusion of a State-Selected Model Drug.
- Have received that infusion while the CGT Access Model outcome-based agreements between DHS and the drug manufacturers are in effect.
Fertility Preservation
Fertility preservation is not a covered BadgerCare Plus or Medicaid benefit. It is only available to members who qualify to receive care through the CGT Access Model, as it is offered through the manufacturers of the drugs they are being treated with. Free fertility preservation services are not available to members with SCD whose treatment does not qualify for participation in the CGT Access Model. Providers should follow the drug manufacturers' guidance regarding referrals for fertility preservation for interested members receiving care through the model.
Managed Care Exemption
BadgerCare Plus and Medicaid members who participate in the CGT Access Model will be permanently exempted from having to be in an HMO once an infusion date has been scheduled, beginning the first of the month of the first round of apheresis. Either the member or the HMO may request exemption through a DHS nurse consultant. Appropriate documentation showing an approved PA and scheduled infusion date must accompany the exemption request.
Non-Emergency Medical Transportation
Transportation for any SCD-related appointments is considered a critical care ride. Critical care rides can be scheduled up to the same day as the appointment, and they are eligible for additional support from NEMT call center representatives, who can help schedule and coordinate rides. When members schedule rides, they must tell the agent that the ride is to an SCD-related appointment so the agent can document it as critical. Members may choose to have other people travel with them to their appointments, including children, attendants, other people under a member's care, or riders requested by a health care provider. When members schedule a ride, they should tell the agent if they are planning to bring someone with them to an appointment. Topic #17397 Crinone
PA requests for Crinone may be approved for the treatment of secondary amenorrhea.
Although Crinone is also indicated for use in ART treatment, ForwardHealth does not cover infertility treatment, including ART.
PA requests for Crinone for the treatment of secondary amenorrhea must be submitted using Section VI (Clinical Information for Drugs with Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA and the PA/RF.
PA requests for Crinone for the treatment of secondary amenorrhea may be submitted on the ForwardHealth Portal, by fax, or by mail. PA requests for Crinone may not be submitted using the STAT-PA system.
Clinical Criteria for Crinone
Crinone may be used for the treatment of the following conditions:
- Secondary amenorrhea
- Prevention of preterm labor in women with a current singleton pregnancy and either short cervical length or a history of preterm labor
Although Crinone is also indicated for use in ART treatment, ForwardHealth does not cover infertility treatment, including ART.
For Members Who Have Secondary Amenorrhea
Secondary amenorrhea is the cessation of menses for six or more months in a woman who previously had normal menstrual cycles. Women who are pregnant, breastfeeding, or in menopause are not considered to have secondary amenorrhea.
Clinical criteria that must be documented for approval of a PA request for Crinone for members who have secondary amenorrhea are all of the following:
- The member has secondary amenorrhea.
- The member's last menstrual cycle occurred more than six months ago.
- The member is not being treated for infertility.
- The member is not pregnant or breastfeeding.
- The member is not in menopause.
- The member is currently receiving estrogen therapy.
Crinone 4% will only be approved for every-other-day dosing up to a total of six doses.
In women who fail to respond to a trial of Crinone 4%, Crinone 8% will only be approved for every-other-day dosing up to a total of six doses.
Crinone 8% for Women with a Current Singleton Pregnancy and Either Short Cervical Length or a History of Preterm Labor
ForwardHealth covers Crinone 8% for daily dosing through 36 weeks gestation in women with a current singleton pregnancy and either short cervical length or a history of preterm labor.
PA is not required for coverage of Crinone 8% in these situations; however, providers are required instead to follow the procedures for Diagnosis-Restricted Drugs. Topic #20897 Cystic Fibrosis Drugs Containing a Cystic Fibrosis Transmembrane Conductance Regulator Potentiator
Clinical PA is required for all cystic fibrosis drugs containing a CFTR potentiator (for example, deutivacaftor, ivacaftor).
PA requests for cystic fibrosis drugs containing a CFTR potentiator will only be approved for one cystic fibrosis drug containing a CFTR potentiator per member. ForwardHealth does not cover treatment with more than one cystic fibrosis drug containing a CFTR potentiator.
PA requests for cystic fibrosis drugs containing a CFTR potentiator should be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
PA requests for cystic fibrosis drugs containing a CFTR potentiator may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical criteria that must be documented for approval of a PA request for cystic fibrosis drugs containing a CFTR potentiator are all of the following:
- The member has cystic fibrosis.
- The member's age is consistent with the FDA-approved indication for the use of the specific cystic fibrosis drug containing a CFTR potentiator.
- The member has a gene mutation consistent with the FDA-approved indication for the use of the specific cystic fibrosis drug containing a CFTR potentiator. (Note: A copy of the gene mutation test results must be included with an initial PA request.)
A copy of the member's medical records must be submitted with all PA requests for cystic fibrosis drugs containing a CFTR potentiator. Medical records should document the following:
- Current progress notes related to the member's cystic fibrosis treatment plan
- A copy of the member's current pulmonary function test results
Initial PA requests for cystic fibrosis drugs containing a CFTR potentiator may be approved for up to 183 days.
Renewal PA requests require that the member has been adherent with their entire cystic fibrosis medication regimen and that there is documentation demonstrating the member has experienced clinical improvement with the prescribed cystic fibrosis drug containing a CFTR potentiator. Renewal PA requests may be approved for up to a maximum of 365 days. Topic #22577 Dojolvi
Dojolvi requires clinical PA.
PA requests for Dojolvi must be completed, signed, and dated by the prescriber. PA requests for Dojolvi must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Dojolvi must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Dojolvi may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Dojolvi
Clinical criteria that must be documented for approval of a PA request for Dojolvi are all of the following:
- The member has a confirmed diagnosis of a long-chain fatty acid oxidation disorder.
- The member has a dietary assessment and a complete dietary treatment plan that includes all of the following:
- The member's height, weight, and estimated total daily caloric intake
- A copy of the prescription order for Dojolvi
- The target daily dosage of Dojolvi as a percentage of the member's total daily caloric intake
Note: Dojolvi is prescribed in milliliters, and the recommended target daily dosage is up to 35% of the member's total daily caloric intake divided into at least four doses.
Supporting clinical information and a copy of the member's current medical records must be included in all PA requests. The supporting clinical information and the medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
Topic #1414 Drugs That Require Paper Prior Authorization
Paper PA request submission is required to determine medical necessity for the following drugs. Diagnosis and information regarding the medical requirements for these drug categories must be provided on the PA request for members enrolled in BadgerCare Plus, Wisconsin Medicaid, and SeniorCare:
- Alitretinoin gel (when used to treat Kaposi's sarcoma lesions)
- BBG drugs
- BMN drugs
- Diagnosis-restricted drugs that require PA outside approved diagnoses
- Drugs without signed manufacturer rebate agreements*
- Fertility enhancement drugs (when used to treat conditions other than infertility)
- Impotence treatment drugs (when used for a condition other than impotence)
- Unlisted or investigational drugs*
* SeniorCare does not cover prescription drugs, even with a PA request, that do not have a signed rebate agreement between the Wisconsin DHS and the manufacturer; however, these drug products may be covered for BadgerCare Plus or Wisconsin Medicaid members if a paper PA request is submitted.
Submitting Paper Prior Authorization Requests
Paper PA requests that are faxed to ForwardHealth will receive an adjudication response via telephone one business day after they are received. Providers who submit PA requests by mail should be aware that this option requires additional time for the PA request to reach ForwardHealth and for ForwardHealth to complete the adjudication process.
To avoid delayed adjudication, do not fax and mail duplicate copies of the same PA request forms.
Pharmacy providers may contact Provider Services to determine the status of any PA request that has been submitted.
Approved, Returned, and Denied Paper Requests
A paper PA request submitted to ForwardHealth may be approved, returned, or denied.
When a PA request is approved:
- The "approved" box on the PA/RF is checked.
- The grant and expiration dates are indicated.
- A signature and a date signed are indicated.
- A specific days' supply is indicated.
When a PA request is returned:
- The "return" box on the PA/RF is checked.
- An explanation for the return is indicated.
A PA request is returned because additional information is needed or because information on the request must be corrected. A returned PA request is not the same as a denied request. Providers should correct or add the missing information to the original PA request and resubmit it to BadgerCare Plus or SeniorCare.
When a PA request is denied:
- The "denied" box on the PA/RF is checked and an explanation is given.
- A signature and date signed are indicated.
Topic #23659 Duvyzat
Duvyzat requires clinical PA.
PA requests for Duvyzat must be completed, signed, and dated by the prescriber. PA requests for Duvyzat must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Duvyzat may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Duvyzat
Clinical criteria for approval of a PA request for Duvyzat are all of the following:
- The member has a diagnosis of DMD.
- The member is able to ambulate.
- The member's age must be consistent with FDA-approved product labeling for Duvyzat.
- The prescription is written by or through consultation with a neurologist.
- The provider will obtain and evaluate the member's platelet count and triglyceride levels prior to and during treatment with Duvyzat.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Duvyzat. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If clinical criteria for Duvyzat are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Duvyzat may be approved for up to 365 days. Renewal PA requests must include supporting clinical information and copies of the member's current medical records.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #13678 Fertility and Impotence Drugs
According to Wis. Admin. Code §§ DHS 107.10(2)(f) and 107.10(2)(g), the following drugs require PA:
- Drugs identified by Wisconsin DHS that are sometimes used to enhance the prospect of fertility in males or females, when proposed to be used for treatment of a condition not related to fertility
- Drugs identified by DHS that are sometimes used to treat impotence, when proposed to be used for the treatment of a condition not related to impotence
These types of drugs are not covered unless a paper PA request is submitted on the PA/DGA and the drug is being used to treat a condition unrelated to fertility or impotence. Topic #22820 Hemgenix
Hemgenix requires clinical PA.
Hemgenix is covered and reimbursed under the pharmacy benefit. Providers should submit claims for Hemgenix to ForwardHealth using a noncompound drug claim. For specific questions about the billing or coverage of high cost, orphan, and accelerated approval drugs, providers may contact Provider Services or email DHSOrphanDrugs@dhs.wisconsin.gov.
Additional Requirements for Hemgenix
Physician-administered Hemgenix is reimbursed separately from physician and clinical services associated with the administration of Hemgenix. The pharmacy provider is required to establish a delivery process with the prescriber to ensure that physician-administered Hemgenix is delivered directly to the prescriber or an agent of the prescriber. Pharmacy providers may only submit a claim to ForwardHealth for Hemgenix that has been administered to a member. If Hemgenix has been dispensed for a member but the dose is not administered to the member, the prescriber is responsible for notifying the dispensing pharmacy. If ForwardHealth has paid the dispensing pharmacy for any portion of the dispensing of Hemgenix that is not administered to the member, the dispensing pharmacy is responsible for reversing any claims submitted to ForwardHealth.
Clinical Criteria for Hemgenix
Clinical criteria that must be documented for approval of a PA request for Hemgenix are all of the following:
- Hemgenix must be prescribed by a hematologist at a dose of 2 x 10¹³ genome copies (gc) per kilogram of body weight.
- The member has been diagnosed with hemophilia B (congenital Factor IX deficiency).
- The member is 18 years of age or older.
- The member must currently be treated with Factor IX prophylaxis therapy.
- The member must have a current or historical life-threatening hemorrhage, or have repeated, serious spontaneous bleeding episodes.
- The prescriber must include documentation of Factor IX inhibitor titer testing. In case of a positive test result for human Factor IX inhibitors, perform a re-test within approximately 2 weeks. If both the initial test and re-test results are positive, PA for Hemgenix will not be approved.
- The prescriber must include documentation of liver health assessments including, ALT, AST, ALP, total bilirubin, hepatic ultrasound, and hepatic elastography. If the member has radiological liver abnormalities and/or sustained liver enzyme elevations, documentation of a consultation with a hepatologist to assess eligibility for Hemgenix will be required.
Supporting clinical information and a copy of the member's current medical records must be included with all PA requests. The supporting clinical information and the medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
PA requests for Hemgenix will not be approved if the member has any of the following conditions:
- Prior or current malignancy or myeloproliferative disorder or significant immunodeficiency disorder
- Prior allogenic or autologous HSC transplant
Submitting PA Requests for Hemgenix
PA requests for Hemgenix must be completed, signed, and dated by the prescriber. PA requests for Hemgenix must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Hemgenix must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Hemgenix may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug. Topic #23718 Hympavzi
Hympavzi requires clinical PA.
PA requests for Hympavzi must be completed, signed, and dated by the prescriber. PA requests for Hympavzi must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Hympavzi must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Hympavzi may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Hympavzi
Clinical criteria that must be documented for approval of a PA request for Hympavzi for members with hemophilia are all of the following:
- The member's age must be consistent with FDA-approved product labeling for Hympavzi.
- Hympavzi must be prescribed in a dose and manner consistent with FDA-approved product labeling:
- One week after the loading dose, initiate maintenance dosing of 150 mg every week by subcutaneous injection on the same day each week, at any time of day.
- Consider a dose adjustment to 300 mg subcutaneous injection weekly in patients weighing greater than or equal to 50 kg when control of bleeding events is judged to be inadequate by the healthcare provider.
- One of the following is true:
- The member has hemophilia A (congenital factor VIII deficiency) with or without factor VIII inhibitors.
- The member has hemophilia B (congenital factor IX deficiency) with or without factor IX inhibitors.
- One of the following is true:
- The member has severe hemophilia (factor activity less than 1%).
- The member experienced two or more episodes of spontaneous bleeding into joints.
- Hympavzi must be used for routine prophylaxis to prevent or reduce the frequency of bleeding episodes.
- Hympavzi will not be used in combination with prophylactic factor replacement therapy (for example, factor VIII or factor IX products). Members must discontinue use of other prophylactic therapies prior to starting Hympavzi.
- Hympavzi will not be used for treatment of breakthrough bleeds. (Note: Factor VIII or factor IX products may be administered on an as-needed basis for treatment of breakthrough bleeds in patients being treated with Hympavzi.)
- Females of reproductive potential must have a negative pregnancy test prior to initiation of Hympavzi and must use effective contraception during treatment and for two months after the last dose.
- The prescription is written by or through consultation with a hematologist.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Hympavzi. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If clinical criteria for Hympavzi are met, initial PA requests may be approved for up to a maximum of 183 days.
Renewal PA requests for Hympavzi may be approved for up to 365 days. Renewal PA requests must include supporting clinical information and copies of the member's current medical records demonstrating that the member has had a reduction in the frequency of bleeding episodes since starting treatment with Hympavzi.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #22819 Imcivree
Imcivree requires clinical PA.
PA requests for Imcivree must be completed, signed, and dated by the prescriber. PA requests for Imcivree must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Imcivree must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Imcivree may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Conditions for Which PA Requests for Use of Imcivree Will Be Considered for Review
PA requests for Imcivree will only be approved to reduce excess body weight and maintain weight reduction long term for members with the identified clinical conditions:
- BBS
- HO
- POMC, PCSK1, or LEPR deficiency
Clinical Criteria for Imcivree for Members With Bardet-Biedl Syndrome
Clinical criteria that must be documented for approval of a PA request for Imcivree for members with BBS are all of the following:
- Imcivree must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The prescription is written by an endocrinologist or geneticist or through an endocrinology or genetics consultation.
- The member's current height, weight, and BMI are documented.
- The member has BBS.
- The prescriber has evaluated the member and determined that the member does not have any medical or medication contraindications to treatment with Imcivree.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Imcivree for members with BBS. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Imcivree for members with BBS are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Imcivree for members with BBS may be approved for up to 365 days. Renewal PA requests for members who have BBS must include supporting clinical information and copies of the member's current medical records demonstrating that the member's weight or BMI (for patients with continued growth potential) remains at least 5% below the member's baseline weight or their BMI.
Clinical Criteria for Imcivree for Members With Hypothalamic Obesity
Clinical criteria that must be documented for approval of a PA request for Imcivree for members with HO are all of the following:
- Imcivree must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The prescription is written by an endocrinologist or geneticist or through an endocrinology or genetics consultation.
- The member's current height, weight, and BMI are documented.
- The member has HO.
- The prescriber has evaluated the member and determined that the member does not have any medical or medication contraindications to treatment with Imcivree.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Imcivree for members with HO. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Imcivree for members with HO are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Imcivree for members with HO may be approved for up to 365 days. Renewal PA requests for members who have HO must include supporting clinical information and copies of the member's current medical records demonstrating that the member's weight or BMI (for patients with continued growth potential) remains at least 5% below the member's baseline weight or their BMI.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Imcivree for Members With a Proopiomelanocortin, Proprotein Convertase Subtilisin/Kexin Type 1, or Leptin Receptor Deficiency
Clinical criteria that must be documented for approval of a PA request for Imcivree for members with a POMC, PCSK1, or LEPR deficiency are all of the following:
- Imcivree must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The prescription is written by an endocrinologist or geneticist or through an endocrinology or genetics consultation.
- The member's current height, weight, and BMI are documented.
- The member has a POMC, PCSK1, or LEPR deficiency confirmed by genetic testing demonstrating variants in POMC, PCSK1, or LEPR genes that are interpreted as pathogenic, likely pathogenic, or of uncertain significance. (Note: A copy of the genetic testing results must be submitted with the PA request.)
- The prescriber has evaluated the member and determined that the member does not have any medical or medication contraindications to treatment with Imcivree.
A copy of the member's current medical records must be submitted with all PA requests for Imcivree for members with a POMC, PCSK1, or LEPR deficiency. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Imcivree for members with a POMC, PCSK1, or LEPR deficiency are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Imcivree for members with a POMC, PCSK1, or LEPR deficiency may be approved for up to 365 days. Renewal PA requests for members who have a POMC, PCSK1, or LEPR deficiency must include supporting clinical information and copies of the member's current medical records demonstrating that the member's weight or BMI (for patients with continued growth potential) remains at least 5% below the member's baseline weight or their BMI.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #23923 Javygtor and Zelvysia
Javygtor and Zelvysia require clinical PA.
PA requests for Javygtor and Zelvysia must be completed, signed, and dated by the prescriber. PA requests for Javygtor and Zelvysia must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Javygtor and Zelvysia may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Javygtor and Zelvysia
The clinical criteria that must be documented for approval of a PA request for Javygtor or Zelvysia includes both of the following:
- The prescriber has submitted detailed clinical justification for prescribing Javygtor or Zelvysia instead of sapropterin dihydrochloride (generic Kuvan).
- The clinical information must document why the member cannot use sapropterin dihydrochloride (generic Kuvan), including why it is medically necessary that the member receive Javygtor or Zelvysia instead of sapropterin dihydrochloride (generic Kuvan).
Supporting clinical documentation and a copy of the member's current medical records must be submitted with the PA request to support the member's need for Javygtor or Zelvysia. Initial PA requests for Javygtor or Zelvysia may be approved for up to 183 days.
Renewal PA requests may be approved for up to 365 days. Medical records must be submitted demonstrating clinical improvement and must reflect member compliance with Javygtor or Zelvysia. Topic #21397 Jynarque and Tolvaptan
Jynarque and tolvaptan require clinical PA.
PA requests for Jynarque and tolvaptan must be completed, signed, and dated by the prescriber. PA requests for Jynarque and tolvaptan must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Jynarque and tolvaptan may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Jynarque and Tolvaptan
The following clinical criteria must be met and documented for approval of a PA request for Jynarque or tolvaptan:
- The member has ADPKD.
- The member's age must be consistent with FDA-approved product labeling for the requested drug.
- The prescription is written by, or in consultation with, a nephrologist or kidney transplant specialist.
- The member has an eGFR equal to or greater than 25 mL/min per 1.73 m2.
- The member has a high risk for progression to ESRD due to one or more of the following:
- A confirmed annual eGFR decline of at least 5 mL/min/1.73 m2 in one year
- A confirmed annual eGFR decline of at least 2.5 mL/min/1.73 m2 per year over a period of five years
- A greater than 5% increase in total kidney volume per year on at least three repeated measurements (via CT or MRI, each at least six months apart)
- A truncated PDK1 mutation and early clinical signs (for example, hypertension, macroscopic hematuria, cyst infection, or flank pain before the age of 35)
- A Mayo classification (height adjusted total kidney volume by CT or MRI and age) of class 1C, 1D, and 1E
- Documentation of average kidney length greater than 16.5 cm per ultrasonography, CT, or MRI
A copy of the member's medical records must be submitted and should sufficiently document:
- The information listed in the clinical coverage criteria.
- Details regarding previous medication use.
- The member's current treatment plan.
If the clinical criteria for Jynarque or tolvaptan are met, initial PA requests may be approved for up to 183 days. Renewal PA requests for Jynarque or tolvaptan may be approved for up to 365 days.
Renewal PA Requests
Requests for renewal must meet the clinical criteria for initial PA approval and have documentation to support that there has been a decrease in the member's kidney disease progression. In order to confirm the necessary adherence, the claims history and medical records will be reviewed for all renewal requests. A copy of the pertinent medical records must be included with the PA request. Topic #23719 Lenmeldy
Lenmeldy requires clinical PA.
If a PA request for Lenmeldy is approved, Lenmeldy will be covered under the pharmacy benefit. To bill ForwardHealth for Lenmeldy, pharmacy providers should submit a noncompound drug claim.
For specific questions about the billing or coverage of high cost, orphan, and accelerated approval drugs, providers may contact Provider Services at 800-947-9627 or email DHSOrphanDrugs@dhs.wisconsin.gov.
Additional Requirements for Lenmeldy
Lenmeldy will be reimbursed separately from physician and clinical services associated with the administration of Lenmeldy. The pharmacy provider is required to establish a delivery process with the prescriber to ensure that the physician-administered Lenmeldy is delivered directly to the prescriber or an agent of the prescriber.
Pharmacy providers may only submit a claim to ForwardHealth for Lenmeldy that has been administered to a member. If Lenmeldy has been dispensed for a member but the dose is not administered to the member, the prescriber is responsible for notifying the dispensing pharmacy. If ForwardHealth has paid the dispensing pharmacy for any portion of the dispensing of Lenmeldy that is not administered to the member, the dispensing pharmacy is responsible for reversing any claims submitted to ForwardHealth.
Clinical Criteria for Lenmeldy
Clinical criteria that must be documented for approval of a PA request for Lenmeldy are all of the following:
- Lenmeldy must be prescribed and administered by a physician and treatment center with expertise in treating MLD and at a dose appropriate for the member's MLD subtype.
- The member has PSLI, PSEJ or ESEJ MLD.
- The member's age is consistent with the FDA-approved product labeling for Lenmeldy.
- The member will undergo HSC mobilization, apheresis, and myeloablative conditioning. The prescriber must confirm the member has been evaluated for renal and hepatic impairment and HSC transplantation is appropriate for the member.
- The member must have full myeloablative conditioning administered before infusion of Lenmeldy. Allow a minimum of 24 hours of washout before Lenmeldy infusion.
- The prescriber will provide documentation of completed negative screening for infectious diseases including HBV, HCV, HIV-1 and HIV-2, and HTLV-1 and HTLV-2 in accordance with clinical guidelines before collection of cells for manufacturing.
- Standard procedures for patient management after HSC transplantation should be followed after Lenmeldy infusion.
- The prescriber must manage other concomitant medications (as applicable), consistent with FDA product labeling.
- The member should not take anti-retroviral medications for at least one month prior to mobilization and for the expected duration for elimination of the medications.
- If a member requires anti-retroviral medications for HIV prophylaxis, mobilization and apheresis should be delayed until HIV infection is adequately ruled out.
Conditions Not Approved for PA Requests for Lenmeldy
PA requests for Lenmeldy will not be approved if the member has any of the following conditions:
- Advanced liver disease: (for example, alanine transaminases greater than 3 times upper limit of normal; direct bilirubin value greater than 2.5 times upper limit of normal; baseline prothrombin time [INR] greater than 1.5 times upper limit of normal; cirrhosis; bridging fibrosis and cirrhosis; or active hepatitis)
- Prior or current malignancy or myeloproliferative disorder or significant immunodeficiency disorder
- Prior allogenic or autologous HSC transplant or another gene therapy.
Submitting PA Requests for Lenmeldy
PA requests for Lenmeldy must be completed, signed, and dated by the prescriber. PA requests for Lenmeldy must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Lenmeldy must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Lenmeldy may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug. Topic #22579 Leqvio
Leqvio is a physician-administered drug that requires clinical PA.
All PA requests for Leqvio must be submitted with HCPCS code J1306 (Injection, inclisiran, 1 mg).
PA requests for Leqvio must be completed, signed, and dated by the prescriber. PA requests for Leqvio must be submitted using Section V (Clinical Information for Physician-Administered Drugs With Specific PA Criteria Addressed in the ForwardHealth Online Handbook) on the PA/PAD form. Clinical documentation supporting the use of Leqvio must be submitted with the PA request.
Prescribers are required to submit the completed PA/PAD form and a completed PA/RF to ForwardHealth.
PA requests for Leqvio may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Conditions for Which PA Requests for Use of Leqvio Will Be Considered for Review
ForwardHealth will only consider PA requests for Leqvio to treat the following identified clinical conditions:
ForwardHealth will approve up to one ACL inhibitor or one PCSK9 inhibitor at a time per member. ForwardHealth does not cover treatment with more than one ACL inhibitor and/or PCSK9 inhibitor.
Clinical Criteria for Leqvio for Members With Clinical Atherosclerotic Cardiovascular Disease
Clinical criteria that must be documented for approval of a PA request for Leqvio for members with clinical ASCVD are all of the following:
- The member has clinical ASCVD, as evidenced by one of the following:
- The member has CAD, which is supported by a history of myocardial infarction (heart attack), coronary revascularization, or angina pectoris.
- The member has a history of stroke.
- The member has symptomatic peripheral arterial disease as evidenced by one of the following:
- Intermittent claudication with an ABI of less than or equal to 0.9
- Peripheral arterial revascularization procedure or amputation due to atherosclerotic disease
- The member has taken Praluent or Repatha concurrently with a maximized statin regimen for at least three continuous months with failure to reach an LDL less than or equal to 70 mg/dL. The member must continue to take the maximally tolerated dose of a statin during treatment with Leqvio.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Leqvio. The supporting clinical information and medical records must document the following:
- Evidence that the member has clinical ASCVD
- A current lipid panel lab report
- Documentation of the member's current and previous lipid-lowering drug therapies, including the following for each trial:
- Drug name(s) and dosage
- Dates taken
- Lipid panel report prior to and during drug therapy (including dates taken)
- Reasons for discontinuation if drug therapy was discontinued
Initial and Renewal PA Requests for Leqvio for Members With Clinical Atherosclerotic Cardiovascular Disease
If the clinical criteria for Leqvio are met, initial PA requests may be approved for the initial and three-month doses.
Renewal PA requests for Leqvio may be approved for up to two doses per year. Renewal PA requests for members who have clinical ASCVD must include supporting clinical information and copies of the member's current medical records demonstrating evidence of LDL reduction of at least 30 percent from pre-treatment baseline or a decrease to 100 mg/dL or less. Members also must continue to take the maximized statin treatment regimen during treatment with Leqvio.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. A copy of the current lipid panel report (within the past 30 days) must be included with the PA request.
Clinical Criteria for Leqvio for Members With Heterozygous Familial Hypercholesterolemia
Clinical criteria that must be documented for approval of Leqvio for members with HeFH are all of the following:
- The member has been diagnosed by a specialist in cardiology or lipid management.
- The member has HeFH, as evidenced by clinical documentation that supports a definitive diagnosis of HeFH using either WHO criteria (Dutch Lipid Clinic Network clinical criteria with a score greater than eight) or Simon Broome diagnostic criteria.
- The member has taken Praluent or Repatha concurrently with a maximized statin regimen for at least three continuous months with failure to reach an LDL less than or equal to 100 mg/dL. The member must continue to take the maximally tolerated dose of a statin during treatment with Leqvio.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Leqvio. The supporting clinical information and medical records must document the following:
- Evidence that the member has HeFH
- A current lipid panel lab report
- Documentation of the member's current and previous lipid -lowering drug therapies, including the following for each trial:
- Drug name(s) and dosage
- Dates taken
- Lipid panel report prior to and during drug therapy (including dates taken)
- Reasons for discontinuation if drug therapy was discontinued
Initial and Renewal PA Requests for Leqvio for Members With Heterozygous Familial Hypercholesterolemia
If the clinical criteria for Leqvio are met, initial PA requests may be approved for the initial and three-month doses.
Renewal PA requests for Leqvio may be approved for up to two doses per year. Renewal PA requests for members who have HeFH must include supporting clinical information and copies of the member's current medical records demonstrating evidence of LDL reduction of at least 30 percent from pre-treatment baseline or a decrease to 130 mg/dL or less. Members also must continue to take the maximized statin treatment regimen during treatment with Leqvio. Topic #21417 Long-Term Hereditary Angioedema Prophylactic Drugs
Clinical PA is required for long-term HAE prophylactic drugs. Andembry, Dawnzera, Orladeyo, and Takhzyro are long-term HAE prophylactic drugs that require PA.
ForwardHealth does not cover treatment with more than one long-term HAE prophylactic drug at a time.
PA requests for long-term HAE prophylactic drugs must be completed, signed, and dated by the prescriber. PA requests for long-term HAE prophylactic drugs must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The prescriber is required to send the completed PA/DGA form to the pharmacy where the prescription will be filled. The pharmacy provider is required to complete a PA/RF and submit it along with the PA/DGA form received from the prescriber. Prescribers should not submit the PA forms to ForwardHealth.
PA requests for long-term HAE prophylactic drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Long-Term Hereditary Angioedema Prophylactic Drugs
The following clinical criteria must be met and documented for approval of a PA request for long-term HAE prophylactic drugs:
- The member has type I or type II HAE.
- HAE is documented based on evidence of a low C4 level, plus one of the following:
- The member has a low C1-INH antigenic level (C1-INH antigenic level below the lower limit of normal as defined by the laboratory performing the test).
- The member has a normal C1-INH antigenic level and a low C1-INH functional level (C1-INH functional level below the lower limit of normal as defined by the laboratory performing the test).
- The member's age must be consistent with FDA-approved product labeling for the drug requested.
- The prescription is written by or in consultation with an allergist, immunologist, hematologist, or a physician who specializes in HAE or related disorders.
- Medications known to cause angioedema (for example, angiotensin-converting enzyme inhibitors, estrogens, angiotensin II receptor blockers) have been evaluated and discontinued when appropriate.
- The member has no signs of current acute angioedema but has a history of clinical symptoms and signs consistent with HAE.
- The member requires HAE prophylaxis as evidenced due to one or more of the following:
- The member has a history of at least one severe HAE attack per month (defined as an attack that significantly interrupts daily activities despite short-term treatment).
- The member has experienced disabling symptoms for at least five days per month.
- The member has a history of laryngeal angioedema.
- One of the following is true:
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction that prevents the use of Haegarda.
- The member has a clinically significant drug interaction with Haegarda and another medication the member is taking, or the member has a medical condition(s) that prevents the use of Haegarda.
Supporting clinical information and a copy of the member's current medical records must be included in all PA requests. The supporting clinical information and the medical records must document the following:
- The frequency, severity, and duration of the HAE attacks
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for long-term HAE prophylactic drugs are met, initial PA requests may be approved for up to 183 days. Renewal PA requests for long-term HAE prophylactic drugs may be approved for up to 365 days.
Renewal PA Requests for Long-Term Hereditary Prophylactic Drugs
Renewal PA requests must meet the clinical criteria for initial PA requests for long-term HAE prophylactic drugs and have documentation to support that the member has experienced a reduction in the frequency, severity, or duration of HAE attacks versus the member's baseline since starting treatment. A copy of the member's current medical records must be included with the PA request for a long-term HAE prophylactic drug. Topic #21199 Luxturna
Luxturna requires clinical PA.
Note: The Select High Cost, Orphan, and Accelerated Approval Drugs data table identifies select high cost, orphan, and accelerated approval drugs and interim billing and coverage information for these drugs. The table also identifies which drugs have specific PA or policy requirements. For specific questions about the billing or coverage of high cost, orphan, and accelerated approval drugs listed in the Select High Cost, Orphan, and Accelerated Approval Drugs data table, providers may contact Provider Services or email DHSOrphanDrugs@dhs.wisconsin.gov.
Clinical Criteria for Luxturna
Clinical criteria that must be documented for approval of a PA request for Luxturna are all of the following:
- The member has a confirmed diagnosis of an inherited retinal dystrophy due to biallelic RPE65 mutations.
- The member has sufficient viable retinal cells (defined as an area of retinal thickness greater than 100 microns within the posterior pole) as measured by OCT.
- The member has remaining light perception in the eye(s) that will receive treatment.
- Luxturna is prescribed and administered by an ophthalmologist or retinal surgeon with experience providing subretinal injections.
If clinical criteria for Luxturna are met, PA requests may be approved on a unilateral basis for up to four weeks (one lifetime dose per eye). For consideration of continued therapy on the second eye, all of the following must apply:
- All clinical criteria for initial PA request approval must be met.
- Administration is planned within a close interval to the treatment of the first eye, but at least six days apart.
- The PA request is not for a repeat treatment of a previously treated eye.
Submitting PA Requests for Luxturna
For PA requests for Luxturna, the prescriber is required to complete, sign, and date the PA/DGA form, using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the form. The prescriber is required to send the completed PA/DGA form to the pharmacy where the prescription will be filled. The pharmacy provider is required to complete a PA/RF and submit it, along with the PA/DGA form received from the prescriber, to ForwardHealth using the PA submission option most appropriate for the drug.
PA requests for Luxturna may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system). Topic #23657 Lyfgenia
Clinical PA is required for Lyfgenia.
If a PA request for Lyfgenia is approved, Lyfgenia will be covered under the pharmacy benefit. To bill ForwardHealth for Lyfgenia, pharmacy providers should submit a pharmacy noncompound drug claim and must include the member's diagnosis code on the pharmacy claim submitted for Lyfgenia. The DOS submitted on the pharmacy claim must be the date the member receives the infusion of Lyfgenia.
For specific questions about the billing or coverage of high cost, orphan, and accelerated approval drugs, providers may contact Provider Services or email DHSOrphanDrugs@dhs.wisconsin.gov.
Lyfgenia Cell and Gene Therapy Access Model Requirements for Treatment Centers
Lyfgenia is a State-Selected Model Drug in the CMS'
CGT
Access Model when used for the treatment of SCD.
The treatment center must agree to all of the following for members determined to be eligible in the CGT Access Model:
- Treatment center providers administering Lyfgenia for SCD must enroll and participate in the CMS-Designated Patient Registry through CIBMTR .
- Treatment center providers must be enrolled in CIBMTR before administering Lyfgenia to Wisconsin Medicaid members.
- Treatment center providers must also obtain member consent to participate in the CIBMTR Research Database Protocol under which this study will be governed and are responsible for submitting data to CIBMTR, per the CGT Access Model study requirements.
- Treatment center providers administering Lyfgenia for SCD must ensure Lyfgenia is not purchased through the 340B Program when administered to eligible CGT Access Model members.
For assistance with enrollment in the CMS-Designated Patient Registry for the CMS CGT Access Model, providers may email CIBMTR at CGTModel@mcw.edu.
Requirements for Lyfgenia
Lyfgenia will be reimbursed separately from physician and clinical services associated with the administration of Lyfgenia. The pharmacy provider is required to establish a delivery process with the prescriber to ensure that the physician-administered Lyfgenia is delivered directly to the administering treatment center.
Pharmacy providers may only submit a claim to ForwardHealth for Lyfgenia that has been administered to a member. If Lyfgenia has been dispensed for a member but the dose is not administered to the member, the prescriber is responsible for notifying the dispensing pharmacy. If ForwardHealth has paid the dispensing pharmacy for any portion of the dispensing of Lyfgenia that is not administered to the member, the dispensing pharmacy is responsible for reversing any claims submitted to ForwardHealth.
Lyfgenia must be prescribed at a minimum recommended dose of 3 x 10⁶ CD34+ cells/kg of body weight.
The member must have full myeloablative conditioning administered before infusion of Lyfgenia. Full myeloablative conditioning must be administered a minimum of 48 hours before infusion of Lyfgenia.
Standard procedures for patient management after HSC transplantation should be followed after Lyfgenia infusion.
The prescriber must manage other concomitant medications (as applicable) consistent with FDA product labeling.
The member must not take disease-modifying therapies for SCD (for example, crizanlizumab, L-glutamine, voxelotor) for at least two months prior to mobilization.
The member must not take iron chelation therapy at least seven days prior to mobilization and conditioning. If the member takes iron chelation after apheresis, the member must discontinue iron chelation at least seven days prior to myeloablative conditioning. Myelosuppressive iron chelators are not recommended for six months after Lyfgenia infusion.
The member must not take erythropoietin for at least two months prior to mobilization.
The member must not take hydroxyurea at least two months prior to mobilization and two days prior to conditioning and will not resume until all cycles of apheresis are completed.
The member must not take prophylactic HIV anti-retroviral medications for at least one month prior to mobilization and until all cycles of apheresis are completed. Adjust time appropriately for long-acting anti-retroviral medications.
G-CSF must not be used prior to or with mobilization and conditioning. G-CSF is not recommended for at least 21 days after Lyfgenia infusion.
PA Information for Lyfgenia
Clinical Criteria for Lyfgenia
Clinical criteria that must be documented for approval of a PA request for Lyfgenia for SCD are all of the following:
- Lyfgenia must be prescribed and administered by a physician and at a treatment center with expertise in treating SCD with Lyfgenia.
- The prescribing provider attests that at least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response with hydroxyurea.
- The member has experienced a clinically significant adverse drug reaction with hydroxyurea.
- There is a clinically significant drug interaction between another drug(s) the member is taking and hydroxyurea.
- The member has a medical condition(s) that prevents the use of hydroxyurea.
- The prescribing provider attests that the member is currently receiving chronic transfusion therapy for recurrent VOEs or the member has experienced four or more VOEs in the previous 24 months.
- The member's age at the time of the planned infusion must be consistent with FDA-approved product labeling for Lyfgenia.
- The prescriber will provide documentation of completed negative screening for active infectious diseases including HBV, HCV, HIV 1 and 2 (HIV-1/HIV-2) and HTLV 1 and 2 (HTLV-1/HTLV-2), in accordance with clinical guidelines before collection of cells for manufacturing.
- The prescriber has attested that the member is clinically stable and fit for transplantation.
Conditions Not Approved for PA Requests for Lyfgenia
PA requests for Lyfgenia will not be approved if the member has any of the following conditions:
- Advanced liver disease (for example, alanine transaminases greater than three times the upper limit of normal, direct bilirubin value greater than 3 times the upper limit of normal, baseline prothrombin time [INR] greater than 1.5 times the upper limit of normal, cirrhosis, bridging fibrosis, or active hepatitis)
- A history of untreated Moyamoya disease or the presence of Moyamoya disease that, in the opinion of the prescriber, puts the member at risk of bleeding
- Current malignancy, myeloproliferative disorder, or significant immunodeficiency disorder, unless the prescribing provider attests that the member's condition would not deem the member ineligible for treatment
- Prior allogenic or autologous HSC transplant
Submitting PA Requests for Lyfgenia
PA requests for Lyfgenia must be completed, signed, and dated by the prescriber. PA requests for Lyfgenia must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Lyfgenia must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed and a completed PA/RF to ForwardHealth.
PA requests for Lyfgenia may be submitted Portal, by fax, or by mail (but not using the STAT-PA system).
PA requests for Lyfgenia will be approved for 365 days.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug. Topic #17877 Misoprostol
PA requests for misoprostol must be submitted using Section VI (Clinical Information for Drugs with Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA and the PA/RF.
PA requests for misoprostol may be submitted on the Portal, by fax, or by mail. PA requests for misoprostol may not be submitted using the STAT-PA system.
Clinical Criteria for Misoprostol
Clinical criteria that must be documented for approval of a PA request for misoprostol are all of the following:
- The member is currently taking at least one NSAID.
- The member is not pregnant.
- Misoprostol is being prescribed to reduce the risk of an NSAID-induced gastrointestinal ulcer.
Misoprostol may be approved for up to a maximum of 365 days.
Note: Coverage of misoprostol may be covered in gynecological procedures. However, coverage of misoprostol in conjunction with gynecological conditions is only allowed through the medical benefit. Topic #23617 Omvoh IV for Crohn's Disease and Ulcerative Colitis
Omvoh IV is a physician-administered drug that requires clinical PA.
All PA requests for Omvoh IV must be submitted with HCPCS code J2267 (Injection, mirikizumab-mrkz, 1 mg).
Note: Modifier JA (Administered intravenously) may be needed for billing.
PA requests for Omvoh IV must be completed, signed, and dated by the prescriber. PA requests for Omvoh IV must be submitted using Section V (Clinical Information for Physician-Administered Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) on the PA/PAD form. Clinical documentation supporting the use of Omvoh IV must be submitted with the PA request.
Prescribers are required to submit the complete PA/PAD form and a completed PA/RF to ForwardHealth. PA requests for Omvoh IV may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Conditions for Which PA Requests for Use of Omvoh IV Will Be Considered for Review
ForwardHealth will only consider PA requests for Omvoh IV to treat the following conditions:
- Crohn's disease
- Ulcerative colitis
Clinical Criteria for Omvoh IV for Crohn's Disease
Clinical criteria that must be documented for approval of a PA request for Omvoh IV for members with Crohn's disease are all of the following:
- The member has Crohn's disease.
- The member has been diagnosed by a gastroenterologist.
- Two of the following are true:
- The member has taken Cimzia for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Hadlima or Humira for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Selarsdi subQ or Steqeyma subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why Omvoh IV is being requested.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Omvoh IV for members with Crohn's disease. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
- The member's current weight
If the clinical criteria for Omvoh IV for members with Crohn's disease are met, PA requests will only be approved for the three intravenous induction doses.
Note: A separate PA request must be obtained for maintenance treatment with Omvoh subQ. PA for Omvoh subQ must be obtained through the pharmacy PA process.
Clinical Criteria for Omvoh IV for Ulcerative Colitis
Clinical criteria that must be documented for approval of a PA request for Omvoh IV for members with ulcerative colitis are all of the following:
- The member has ulcerative colitis.
- The member has been diagnosed by a gastroenterologist.
- Two of the following are true:
- The member has taken Hadlima or Humira for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Selarsdi subQ or Steqeyma subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Simponi subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Xeljanz or Xeljanz XR for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why Omvoh IV is being requested.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Omvoh IV. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Omvoh IV are met, PA requests will only be approved for the three IV induction doses.
Note: A separate PA request must be obtained for maintenance treatment with Omvoh subQ. PA for Omvoh subQ must be obtained through the pharmacy PA process. Topic #21200 Palynziq
Palynziq requires clinical PA.
PA requests for Palynziq must be completed, signed, and dated by the prescriber. PA requests for Palynziq must be submitted using using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
PA requests for Palynziq may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Palynziq
Clinical criteria that must be documented for approval of a PA request for Palynziq for members with PKU are all of the following:
- Palynziq must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The member has blood Phe levels greater than 600 micromole/L on existing management (for example, restriction of dietary Phe and protein intake).
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with sapropterin (Kuvan).
- There is a clinically significant drug interaction between another drug(s) the member is taking and sapropterin (Kuvan).
- The member has a medical condition(s) that prevents the use of sapropterin (Kuvan).
- Blood Phe levels will be obtained every four weeks until a maintenance dose is established. The drug dose should be titrated to the lowest effective dose. Once a maintenance dose is established, Phe levels will be monitored every six months.
- A copy of the member's medical records must be submitted and should document the following:
- The medical record contains sufficient documentation to satisfy the clinical coverage criteria above.
- The medical record contains details regarding previous medication use.
- The medical record describes the member's current treatment plan.
If the clinical criteria for Palynziq are met, initial PA requests may be approved for up to 183 days. Renewal PA requests for Palynziq may be approved for up to 365 days.
In addition to meeting the clinical criteria for initial PA request approval, renewal PA requests for Palynziq require the submission of medical records (for example, chart notes, laboratory values) with the most recent results to demonstrate at least one of the following:
- The member has achieved at least a 20% reduction in blood Phe level from pretreatment baseline.
- The member has achieved a blood Phe level less than or equal to 600 micromole/L.
Topic #19817 Personal Continuous Glucose Monitoring Devices and Supplies
ForwardHealth covers personal continuous glucose monitors and supplies in accordance with guidance from the American Diabetes Association and American Association of Clinical Endocrinology for diabetic members who are on insulin, need to check their blood sugar frequently, or are at risk for hypoglycemia. Adults and children, including infants and toddlers, may use a personal continuous glucose monitoring device and supplies to estimate blood glucose levels automatically, which will allow levels to be reviewed and tracked closely.
Coverage Criteria
Personal continuous glucose monitors and supplies are covered for members who meet all of these criteria:
- The member has a diagnosis of any type of diabetes, excluding pre-diabetes.
- The member or the member's caregiver has the cognitive ability to be educated about the device, the willingness to use the device, and the physical capability to use the device.
- The member has a written prescription dated within the last 12 months from a qualified health care professional on the member's medical team, including the name of the continuous glucose monitor prescribed.
- The prescribed continuous glucose monitor is appropriate for the member's age.
Continuous glucose monitors and supplies are covered under ForwardHealth's DME benefit.
Required Documentation
This documentation for fee-for-service claims must be kept in the member's medical record, dated within the last 12 months and must be produced upon the request of Wisconsin DHS:
- Documentation of the member's diabetes diagnosis
- A written prescription from a licensed, qualified health care professional on the member's medical team
- A qualified health care professional-ordered diabetic treatment plan
- The name of the prescribed glucose monitoring device
- Documentation that the member or the member's caregiver has the cognitive ability to be educated about the device, the willingness to use the device, and the physical capability to use the device
Prior Authorization
PA is required:
- For out-of-state, non-border-status providers.
- For prescription of a backup device.
- If a new device is required within three years of having had one dispensed. (Note: Continuous glucose monitors have an expected life of three years, and members can receive one every three years without PA.)
When a PA is needed, this information must be submitted:
- A completed PA/RF
- A completed PA/DMEA
- Documentation of the member's diabetes diagnosis
- A written prescription dated within the last 12 months, including the name of the continuous glucose monitor prescribed, from a licensed qualified health care professional on the member's medical team
- A qualified health care professional-ordered diabetic treatment plan
- The name of the prescribed glucose monitoring device
- Documentation that the member or the member's caregiver has the cognitive ability to be educated about the device, the willingness to use the device, and the physical capability to use the device
HMOs have the option to require PA for these devices. Topic #12997 Prior Authorization for Drugs Outside ForwardHealth-Allowed Diagnoses
PA requests for drugs outside the ForwardHealth-allowed diagnoses must be submitted on paper using a PA/RF and a PA/DGA. The prescriber is required to complete the appropriate section(s) of the PA/DGA as it pertains to the drug being requested and submit peer-reviewed medical literature to support the proven efficacy of the requested use of the drug to the pharmacy where the prescription will be filled. Topic #23837 Qfitlia
Qfitlia requires clinical PA.
PA requests for Qfitlia must be completed, signed, and dated by the prescriber. PA requests for Qfitlia must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Qfitlia must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Qfitlia may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Qfitlia
Clinical criteria for approval of a PA request for Qfitlia are all of the following:
- The member's age must be consistent with FDA-approved product labeling for Qfitlia.
- Qfitlia must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- Qfitlia must be used for routine prophylaxis to prevent or reduce the frequency of bleeding episodes.
- One of the following is true:
- The member has hemophilia A (congenital factor VIII deficiency) with or without factor VIII inhibitors.
- The member has hemophilia B (congenital factor IX deficiency) with or without factor IX inhibitors.
- The prescriber will monitor AT activity using an FDA-cleared test, target AT activity 15–35%, and modify the dosage based on AT activity levels as described in FDA product labeling.
- The prescriber will measure AT activity prior to initiation of Qfitlia. The prescriber will not initiate Qfitlia dosing if AT activity is less than 60%.
- The prescriber will avoid use of Qfitlia for a member with hepatic impairment (Child-Pugh Class A, B, and C). The prescriber must confirm the member has been evaluated for hepatic impairment.
- After Qfitlia is initiated, members may continue their prior CFC or BPA prophylaxis for the first seven days of treatment. The prescriber will discontinue CFC or BPA prophylaxis no later than seven days after the initial dose of Qfitlia.
- Qfitlia will not be used in combination with prophylactic factor replacement therapy (for example, factor VIII or factor IX inhibitors). Members must discontinue use of other prophylactic therapies prior to starting Qfitlia.
- Qfitlia will not be used for treatment of breakthrough bleeds. (Note: Factor VIII or factor IX products may be administered on an as-needed basis for treatment of breakthrough bleeds in patients being treated with Qfitlia.)
- The prescription is written by or through consultation with a hematologist.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Qfitlia. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If clinical criteria for Qfitlia are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Qfitlia may be approved for up to 365 days. Renewal PA requests must include supporting clinical information and copies of the member's current medical records demonstrating that the member has had a reduction in the frequency of bleeding episodes since starting treatment with Qfitlia.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #23342 Rezdiffra
Rezdiffra requires clinical PA.
PA requests for Rezdiffra must be completed, signed, and dated by the prescriber. PA requests for Rezdiffra must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. The prescriber should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Rezdiffra may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Rezdiffra
Clinical criteria that must be documented for approval of a PA request for Rezdiffra are all of the following:
- Rezdiffra must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The member has been diagnosed with noncirrhotic MASH, formerly known as NASH, with moderate to advanced liver fibrosis (consistent with stages F2 to F3 fibrosis) by a biopsy or noninvasive tests (such as FibroScan or MRE + MRI-PDFF).
- The member has taken Wegovy for at least six consecutive months and experienced an unsatisfactory therapeutic response, experienced a clinically significant adverse drug reaction, or the member has a medical condition(s) that prevents the use of Wegovy.
- The member will use the medication in conjunction with diet and exercise.
- The prescriber has documented that the member has not had significant alcohol consumption within the past year.
- The prescription is written by a liver specialist physician such as a gastroenterologist or hepatologist.
- The prescriber will monitor for elevations in liver tests and development of liver-related adverse reactions.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Rezdiffra. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Rezdiffra are met, initial PA requests may be approved for up to 183 days.
Initial Renewal PA Request
Initial renewal PA requests require documentation to support that the member is responding adequately to treatment (as documented in laboratory tests). A copy of the member's current medical records must be included with the PA request. Initial renewal PA requests for Rezdiffra may be approved for up to 183 days.
Subsequent Renewal PA Requests
Subsequent renewal PA requests require documentation to support that the member is responding adequately to treatment (as documented in laboratory tests and a biopsy or noninvasive tests [such as FibroScan or MRE + MRI-PDFF]) and has resolution of steatohepatitis without worsening of fibrosis or at least one stage improvement in fibrosis without worsening of steatohepatitis. A copy of the member's current medical records must be included with the PA request. Subsequent renewal PA requests for Rezdiffra may be approved for up to 365 days. Topic #21201 Select High Cost, Orphan, or Accelerated Approval Drugs
Prior Authorization Requirements for Select High Cost, Orphan, or Accelerated Approval Drugs
Select high cost, orphan, or accelerated approval drugs may require PA, but in some cases, ForwardHealth will not establish drug-specific clinical criteria. For PA requests for select high cost, orphan, or accelerated approval drugs without drug-specific clinical criteria, the prescriber is required to complete, sign, and date the PA/DGA form, using Section VII (Clinical Information for Other Drug Requests) of the form. The prescriber is required to send the completed PA/DGA form to the pharmacy where the prescription will be filled. The pharmacy provider is required to complete a PA/RF and submit it, along with the PA/DGA form received from the prescriber, to ForwardHealth using the PA submission option most appropriate for the drug.
If a high cost, orphan, or accelerated approval drug requires PA, but drug-specific clinical criteria are not established, PA requests for these drugs require the submission of medical records (for example, chart notes, laboratory values) to support that the drug being prescribed is for an FDA-approved indication and is medically necessary as defined by Wis. Admin. Code § DHS 101.03(96m). The drug must be prescribed in a dose and manner consistent with FDA-approved product labeling. These PA requests will be reviewed on a case-by-case basis for medical necessity.
PA requests for these drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Note: For specific questions about the billing or coverage of high cost, orphan, and accelerated approval drugs listed in the Select High Cost, Orphan, and Accelerated Approval Drugs data table, providers may contact Provider Services or email DHSOrphanDrugs@dhs.wisconsin.gov.
Claim Requirements for Physician-Administered-Drugs
Physician-administered drugs will be reimbursed separately from physician and clinical services associated with the administration of select, high cost, and accelerated approval drugs.
The pharmacy provider is required to establish a delivery process with the prescriber to ensure that physician-administered drugs are delivered directly to the prescriber, an agent of the prescriber, or a health care provider designated to administer the drug to the member. Pharmacy providers may only submit a claim to ForwardHealth for the physician-administered drug that has been administered to a member.
If a physician-administered drug has been dispensed for a member but the dose is not administered to the member, the prescriber or health care provider designated to administer the drug to the member is responsible for notifying the dispensing pharmacy. If ForwardHealth has paid the dispensing pharmacy for any portion of the dispensing of the physician-administered drug that is not administered to the member, the dispensing pharmacy is responsible for reversing any claims submitted to ForwardHealth.
Clinical Criteria for Select High Cost, Orphan, or Accelerated Approval Drugs
The Select High Cost, Orphan, and Accelerated Approval Drugs data table identifies high cost, orphan, and accelerated approval drugs that require PA to support that use will be for an FDA-approved indication; PA requests for these drugs will be reviewed on a case-by-case basis for medical necessity.
As new high cost, orphan, and accelerated approval drugs enter the market, ForwardHealth will use the Select High Cost, Orphan, and Accelerated Approval Drugs data table to identify whether or not these drugs require PA. For drugs that require PA, the table will indicate whether or not the drugs have drug-specific PA clinical criteria. Topic #23903 Sephience
Sephience requires clinical PA.
PA requests for Sephience must be completed, signed, and dated by the prescriber. PA requests for Sephience must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Sephience may be submitted on Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Sephience
Clinical criteria for approval of a PA request for Sephience are all of the following:
- Sephience must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The member has been diagnosed with hyperphenylalaninemia as documented by past medical history of at least two blood Phe measurements greater than or equal to 600 μmol/L.
- One of the following is true:
- The member has experienced an unsatisfactory therapeutic response with sapropterin dihydrochloride (generic Kuvan).
- The member has a clinically significant drug interaction between another drug(s) the member is taking and sapropterin dihydrochloride (generic Kuvan).
- The member has a medical condition(s) that prevents the use of sapropterin dihydrochloride (generic Kuvan).
- The member will be on a dietary protein and Phe-restricted diet that is based on blood Phe level.
- The provider will obtain and document the member's Phe concentration before initiating treatment.
- Sephience will not be used in combination with any other approved hyperphenylalaninemia drug therapy.
- Sephience is prescribed by a physician with expertise in treating hyperphenylalaninemia.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Sephience. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If clinical criteria for Sephience are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Sephience may be approved for up to 365 days. Renewal PA requests must include supporting clinical information and copies of the member's current medical records.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen and demonstrate that the member has had a reduction in Phe levels compared to baseline since starting treatment with Sephience. Topic #22818 Skyrizi IV for Crohn's Disease and Ulcerative Colitis
Skyrizi IV is a physician-administered drug that requires clinical PA.
All PA requests for Skyrizi IV must be submitted with HCPCS procedure code J2327 (Injection, risankizumab-rzaa, intravenous, 1 mg).
PA requests for Skyrizi IV must be completed, signed, and dated by the prescriber. PA requests for Skyrizi IV must be submitted using Section V (Clinical Information for Physician-Administered Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) on the PA/PAD form. Clinical documentation supporting the use of Skyrizi IV must be submitted with the PA request.
Prescribers are required to submit the completed PA/PAD form and a completed PA/RF to ForwardHealth. PA requests for Skyrizi IV may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Conditions for Which PA Requests for Use of Skyrizi IV Will Be Considered for Review
ForwardHealth will only consider PA requests for Skyrizi IV to treat the following clinical conditions:
- Crohn's disease
- Ulcerative colitis
Clinical Criteria for Skyrizi IV for Crohn's Disease
Clinical criteria that must be documented for approval of a PA request for Skyrizi IV for members with Crohn's disease are all of the following:
- The member has Crohn's disease.
- The member has been diagnosed by a gastroenterologist.
- Two of the following are true:
- The member has taken Cimzia for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Hadlima or Humira for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Selarsdi subQ or Steqeyma subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why Skyrizi IV is being requested.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Skyrizi IV for members with Crohn's disease. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Skyrizi IV for members with Crohn's disease are met, PA requests will only be approved for the three intravenous induction doses.
Note: A separate PA request must be obtained for maintenance treatment with Skyrizi subQ. PA for Skyrizi subQ must be obtained through the pharmacy PA process.
Clinical Criteria for Skyrizi IV for Ulcerative Colitis
Clinical criteria that must be documented for approval of a PA request for Skyrizi IV for members with ulcerative colitis are all of the following:
- The member has ulcerative colitis.
- The member has been diagnosed by a gastroenterologist.
- Two of the following are true:
- The member has taken Hadlima or Humira for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Selarsdi subQ or Steqeyma subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Simponi subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significatnt adverse drug reaction.
- The member has taken Xeljanz or Xeljanz XR for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why Skyrizi IV is being requested.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Skyrizi IV for members with ulcerative colitis. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Skyrizi IV for members with ulcerative colitis are met, PA requests will only be approved for the IV induction dose.
Note: A separate PA request must be obtained for maintenance treatment with Skyrizi subQ. PA requests for Skyrizi subQ must be obtained through the pharmacy PA process. Topic #23358 Skysona
Skysona requires clinical PA.
If a PA request for Skysona is approved, Skysona will be covered under the pharmacy benefit. Skysona is only indicated for use in boys. To bill ForwardHealth for Skysona, pharmacy providers should submit a pharmacy noncompound drug claim.
For questions about the billing or coverage of high cost, orphan, and accelerated approval drugs, providers may contact Provider Services or email DHSOrphanDrugs@dhs.wisconsin.gov.
Additional Requirements for Skysona
Skysona will be reimbursed separately from physician and clinical services associated with the administration of Skysona. The pharmacy provider is required to establish a delivery process with the prescriber to ensure that the physician-administered Skysona is delivered directly to the prescriber or an agent of the prescriber.
Pharmacy providers may only submit a claim to ForwardHealth for the Skysona that has been administered to a member. If Skysona has been dispensed for a member but the dose is not administered to the member, the prescriber is responsible for notifying the dispensing pharmacy. If ForwardHealth has paid the dispensing pharmacy for any portion of the dispensing of Skysona that is not administered to the member, the dispensing pharmacy is responsible for reversing any claims submitted to ForwardHealth.
Clinical Criteria for Skysona
Clinical criteria that must be documented for approval of a PA request for Skysona are all of the following:
- Skysona must be prescribed by a physician with expertise in treating early, active CALD at a minimum recommended dose of 5.0 X 10⁶ CD34+ cells/kg.
- The member has early, active CALD not due to head trauma. Early, active CALD is defined as asymptomatic or mildly symptomatic (neurologic function score less than or equal to 1) in boys who have gadolinium enhancement on brain MRI and Loes scores of 0.5–9.
- The member's age is consistent with the FDA-approved product labeling for Skysona.
- The member will undergo HSC mobilization, apheresis, and myeloablative conditioning. The prescriber must confirm the member has been evaluated for renal and hepatic impairment and HSC transplantation is appropriate for the member.
- The member must have full myeloablative and lymphodepleting conditioning administered before infusion of Skysona. Allow a minimum of 48 hours of washout before Skysona infusion.
- The prescriber will complete screening for infectious diseases including HBV, HCV, HIV 1 and 2 (HIV-1/HIV-2) and HTLV 1 and 2 (HTLV-1/HTLV-2) in accordance with clinical guidelines before collection of cells for manufacturing.
- Standard procedures for patient management after HSC transplantation should be followed after Skysona infusion.
- The prescriber must manage other concomitant medications (as applicable) consistent with FDA product labeling.
- The member must not take anti-retroviral medications for at least one month prior to stem cell mobilization and for the expected duration for elimination of the medications and until all cycles of apheresis are complete.
- If a member requires anti-retroviral medications for HIV prophylaxis, mobilization and apheresis should be delayed until HIV infection is adequately ruled out.
Submitting PA Requests for Skysona
PA requests for Skysona must be completed, signed, and dated by the prescriber. PA requests for Skysona must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Skysona must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Skysona may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval, including what may not be considered criteria to support the need for a drug. Topic #22097 Spinal Muscular Atrophy Drugs
Clinical PA is required for all SMA drugs.
ForwardHealth does not cover treatment using more than one SMA drug at a time. If a member is transitioning treatment from Spinraza to Evrysdi, a waiting period of 90 days from the last injection of Spinraza is required before starting Evrysdi. The member's current approved PA request for Spinraza will be end-dated upon approval of Evrysdi. If a member is transitioning treatment from Evrysdi to Spinraza, the member's current approved PA request for Evrysdi will be end-dated upon approval of Spinraza. If a member previously received treatment with Zolgensma or Itvisma, a PA request for another SMA drug treatment will be denied.
Claims Submission for Spinal Muscular Atrophy Drugs
SMA drugs, including Evrysdi, will be covered and reimbursed under the pharmacy benefit. Providers should submit claims for SMA drugs to ForwardHealth using a noncompound drug claim. For specific questions about the billing or coverage of high cost, orphan, and accelerated approval drugs Spinraza, Zolgensma, or Itvisma, providers may contact Provider Services or email DHSOrphanDrugs@dhs.wisconsin.gov.
Additional Requirements for Physician-Administered Spinal Muscular Atrophy Drugs
Physician-administered SMA drugs (for example, Spinraza, Zolgensma, and Itvisma) are reimbursed separately from physician and clinical services associated with the administration of SMA drugs. The pharmacy provider is required to establish a delivery process with the prescriber to ensure that the physician-administered SMA drugs are delivered directly to the prescriber or an agent of the prescriber.
Pharmacy providers may only submit a claim to ForwardHealth for the SMA drugs that have been administered to a member. If an SMA drug has been dispensed for a member but the dose is not administered to the member, the prescriber is responsible for notifying the dispensing pharmacy. If ForwardHealth has paid the dispensing pharmacy for any portion of the dispensing of an SMA drug that is not administered to the member, the dispensing pharmacy is responsible for reversing any claims submitted to ForwardHealth.
Evrysdi
Clinical Criteria for Evrysdi
The following clinical criteria must be met and documented for approval of a PA request for Evrysdi:
- Evrysdi is prescribed by a neurologist, pulmonologist, or other physician with expertise in treating SMA and in a manner consistent with the FDA-approved product labeling.
- The member receives medication counseling prior to initiating Evrysdi treatment, and the provider must comply with administration requirements per FDA labeling. (Medication must be dosed after a meal, patients are instructed to drink water after the dose is administered, and medication must be given within five minutes after it has been drawn up into the oral syringe.)
- The member has SMA type 1, 2, or 3, which has been confirmed by genetic testing (5q SMN1: homozygous mutation, homozygous gene deletion, or compound heterozygote).
- The member has at least two copies of the SMN2 gene.
- The prescriber submits exam values from at least one of the following exams (based on member age and motor ability) to establish a baseline motor ability:
- HINE (infant to early childhood)
- HFMSE
- RULM test (non-ambulatory members)
- CHOP INTEND
- 6MWT (ambulatory members)
- MFM32
- The prescriber indicates the member's pulmonary status, including any requirement for ventilator support.
ForwardHealth will consider coverage for Evrysdi on a case-by-case basis if any of the following circumstances are present for the member:
- Complete paralysis of the limbs
- Ventilator dependent for 16 or more hours per day (including non-invasive respiratory support)
A copy of the member's medical records must be submitted and should sufficiently document:
- The information listed in the clinical criteria for PA approval.
- Details regarding previous medication use.
- The member's current treatment plan.
ForwardHealth will deny PA requests for Evrysdi if any of the following circumstances are present:
- The member is currently involved in a clinical trial for an SMA drug.
- The member has received treatment with Zolgensma.
- The member has received treatment with Itvisma.
- The member is currently receiving treatment with Spinraza.
- The member is diagnosed with a non-SMN1 variant of SMA.
Initial PA requests for Evrysdi to treat SMA may be approved for up to 183 days.
Renewal PA Requests
In addition to meeting the clinical criteria for initial PA request approval, renewal PA requests for Evrysdi require the submission of medical records (for example, chart notes, assessment of neurological and motor function) with the most recent results (less than two months prior to the submission of the renewal PA request) documenting a positive clinical response to Evrysdi therapy from pretreatment baseline status as demonstrated by one or more of the following exams:
- HINE that demonstrates the following:
- Improvement or maintenance of previous improvement of at least a two-point (or maximal score) increase in the ability to kick or improvement or maintenance of previous improvement of at least a one-point increase in any other HINE milestone (for example, head control, rolling, sitting, crawling), excluding voluntary grasp
- Net positive improvement in condition, defined as building on previous improvement from the pretreatment baseline in a majority of the HINE motor milestones or achievement or maintenance of any new motor milestone(s) from the pretreatment baseline when the member would otherwise not be expected to do so (for example, sit unassisted, stand, walk)
- HFMSE that demonstrates one of the following:
- Improvement or maintenance of previous improvement of at least a three-point increase in score from pretreatment baseline
- Achievement and maintenance of any new motor milestone(s) from pretreatment baseline when the member would otherwise not be expected to do so
- RULM test that demonstrates one of the following:
- Improvement or maintenance of previous improvement of at least a two-point increase in score from pretreatment baseline
- Achievement and maintenance of any new motor milestone(s) from pretreatment baseline when the member would otherwise not be expected to do so
- CHOP INTEND that demonstrates one of the following:
- Improvement or maintenance of previous improvement of at least a four-point increase in score from pretreatment baseline
- Achievement and maintenance of any new motor milestone(s) from pretreatment baseline when the member would otherwise not be expected to do so
- MFM32 that demonstrates one of the following:
- Improvement or maintenance of previous improvement of at least a two-point increase in score from pretreatment baseline
- Achievement and maintenance of any new motor milestone(s) from pretreatment baseline when the member would otherwise not be expected to do so
Renewal PA requests for Evrysdi used to treat SMA may be approved for up to 365 days.
Submitting PA Requests for Evrysdi
PA requests for Evrysdi must be submitted using the PA/DGA form.
PA requests for Evrysdi must be completed, signed, and dated by the prescriber. PA requests for Evrysdi should be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Evrysdi may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Itvisma
Clinical Criteria for Itvisma
The following clinical criteria must be met and documented for approval of a PA request for Itvisma:
- Itvisma is prescribed by a neurologist, pulmonologist, or other physician with expertise in treating SMA and in a manner consistent with the FDA-approved product labeling.
- The member is 2 years of age or older.
- The member has SMA that has been confirmed by genetic testing (SMN1 mutation).
- The member does not have advanced SMA including, but not limited to, any of the following:
- Complete paralysis of the limbs
- Ventilator dependent for 16 or more hours per day (including non-invasive respiratory support)
- The prescriber submits the most recent pre-treatment anti-AAV9 antibody testing, demonstrating a titer ratio of less than 50 to 1.
A copy of the member's medical records must be submitted and should sufficiently document:
- The information listed in the clinical criteria for PA approval.
- Details regarding previous medication use.
- The member's current treatment plan.
Note: ForwardHealth covers one treatment per lifetime with Itvisma for members 2 years of age or older.
ForwardHealth will deny PA requests for Itvisma if any of the following circumstances are present:
- The member is currently involved in a clinical trial for an SMA drug.
- The member is diagnosed with a non-SMN1 variant of SMA.
- The member is under 2 years of age.
Submitting PA Requests for Itvisma
PA requests for Itvisma must be submitted using the PA/DGA form.
PA requests for Itvisma must be completed, signed, and dated by the prescriber. PA requests for Itvisma should be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Itvisma may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Spinraza
Clinical Criteria for Spinraza
The following clinical criteria must be met and documented for approval of a PA request for Spinraza:
- Spinraza is prescribed by a neurologist, pulmonologist, or other physician with expertise in treating SMA and in a manner consistent with the FDA-approved product labeling.
- The member has SMA type 1, 2, or 3, which has been confirmed by genetic testing (5q SMN1: homozygous mutation, homozygous gene deletion, or compound heterozygote).
- The member has at least two copies of the SMN2 gene.
- The prescriber submits exam values from at least one of the following exams (based on member age and motor ability) to establish a baseline motor ability:
- HINE (infant to early childhood)
- HFMSE
- RULM test (non-ambulatory members)
- CHOP INTEND
- 6MWT (ambulatory members)
- The prescriber indicates the member's pulmonary status, including any requirement for ventilator support.
ForwardHealth will consider coverage for Spinraza on a case-by-case basis if any of the following circumstances are present for the member:
- Complete paralysis of the limbs
- Ventilator dependent for 16 or more hours per day (including non-invasive respiratory support)
- Pre-symptomatic infants who have not yet developed symptoms but have undergone genetic studies indicating a high likelihood of developing SMA type 1, 2, or 3 (that is, less than three copies of the SMN2 gene)
A copy of the member's medical records must be submitted and should sufficiently document:
- The information listed in the clinical criteria for PA approval.
- Details regarding previous medication use.
- The member's current treatment plan.
ForwardHealth will deny PA requests for Spinraza if any of the following circumstances are present:
- The member is currently involved in a clinical trial for an SMA drug.
- The member has received treatment with Zolgensma.
- The member has received treatment with Itvisma.
- The member is currently receiving treatment with Evrysdi.
- The member is diagnosed with a non-SMN1 variant of SMA.
Initial PA requests for Spinraza to treat SMA may be approved for up to 210 days to allow for up to five doses of Spinraza.
Renewal PA Requests
In addition to meeting the clinical criteria for initial PA request approval, renewal PA requests for Spinraza require the submission of medical records (for example, chart notes, assessment of neurological and motor function) with the most recent results (less than one month prior to the submission of the renewal PA request) documenting a positive clinical response to Spinraza therapy from pretreatment baseline status as demonstrated by one or more of the following exams:
- HINE that demonstrates the following:
- Improvement or maintenance of previous improvement of at least a two-point (or maximal score) increase in the ability to kick or improvement or maintenance of previous improvement of at least a one-point increase in any other HINE milestone (for example, head control, rolling, sitting, crawling), excluding voluntary grasp
- Net positive improvement in condition, defined as building on of previous improvement from the pretreatment baseline in a majority of the HINE motor milestones or achievement or maintenance of any new motor milestone(s) from the pretreatment baseline when the member would otherwise not be expected to do so (for example, sit unassisted, stand, walk)
- HFMSE that demonstrates one of the following:
- Improvement or maintenance of previous improvement of at least a three-point increase in score from pretreatment baseline
- Achievement and maintenance of any new motor milestone(s) from pretreatment baseline when the member would otherwise not be expected to do so
- RULM test that demonstrates one of the following:
- Improvement or maintenance of previous improvement of at least a two-point increase in score from pretreatment baseline
- Achievement and maintenance of any new motor milestone(s) from pretreatment baseline when the member would otherwise not be expected to do so
- CHOP INTEND that demonstrates one of the following:
- Improvement or maintenance of previous improvement of at least a four-point increase in score from pretreatment baseline
- Achievement and maintenance of any new motor milestone(s) from pretreatment baseline when the member would otherwise not be expected to do so
Renewal PA requests for Spinraza used to treat SMA may be approved for up to 365 days.
Submitting PA Requests for Spinraza
PA requests for Spinraza must be submitted using the PA/DGA form.
PA requests for Spinraza must be completed, signed, and dated by the prescriber. PA requests for Spinraza should be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Spinraza may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Zolgensma
Clinical Criteria for Zolgensma
The following clinical criteria must be met and documented for approval of a PA request for Zolgensma:
- Zolgensma is prescribed by a neurologist, pulmonologist, or other physician with expertise in treating SMA and in a manner consistent with the FDA-approved product labeling.
- The member is less than 2 years old.
- The member has SMA, type 1, 2, or 3, which has been confirmed, by genetic testing (5q SMN1: homozygous mutation, homozygous gene deletion, or compound heterozygote).
- The member has at least two copies of the SMN2 gene.
- The member does not have advanced SMA including, but not limited to, any of the following:
- Complete paralysis of the limbs
- Ventilator dependent for 16 or more hours per day (including non-invasive respiratory support)
- The prescriber submits the most recent pre-treatment anti-AAV9 antibody testing, demonstrating a titer ratio of less than 50 to 1.
A copy of the member's medical records must be submitted and should sufficiently document:
- The information listed in the clinical criteria for PA approval.
- Details regarding previous medication use.
- The member's current treatment plan.
Note: ForwardHealth covers one treatment per lifetime with Zolgensma for pediatric members less than 2 years of age.
ForwardHealth will deny PA requests for Zolgensma if any of the following circumstances are present:
- The member is currently involved in a clinical trial for an SMA drug.
- The member has received prior treatment with Zolgensma.
- The member is currently receiving treatment with Spinraza or Evrysdi.
Note: If a member already has a current approved PA request for Spinraza or Evrysdi, ForwardHealth will end date the Spinraza or Evrysdi PA request upon approval of Zolgensma.
- The member is diagnosed with a non-SMN1 variant of SMA.
- The member is over 2 years of age.
Submitting PA Requests for Zolgensma
PA requests for Zolgensma must be submitted using the PA/DGA form.
PA requests for Zolgensma must be completed, signed, and dated by the prescriber. PA requests for Zolgensma should be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Zolgensma may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system). Topic #22337 Standard Pharmacy Policy for Covered and Noncovered Drugs
PA Policy for Covered Drugs
BadgerCare Plus, Medicaid, and SeniorCare members who were started on a drug outside of ForwardHealth (for example, a patient assistance program, manufacturer samples, other insurance, or cash) or are currently taking a non-preferred drug will not be exempt from meeting ForwardHealth PA criteria for that drug (unless specifically identified).
Types of Drugs That May Require PA
The following are types of drugs that may require PA:
- BBG and BMN drugs
- Diagnosis-restricted drugs that require PA outside ForwardHealth-approved diagnoses
- Drugs that follow PDL PA policy
- Drugs with established clinical PA criteria outside the PDL
- Requests for drugs by out-of-state pharmacies (for example, not in-state or border-status providers)
- Select high cost, orphan, and accelerated approval drugs
Standard Criteria for Drugs That Require PA
ForwardHealth has established the following standard criteria that may apply to a drug that requires PA:
- The drug must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The following will not be considered as criteria to support the need for a drug requiring PA:
- Nonadherence to previous prescribed drug treatment
- The member's or prescriber's preference for the use of the drug
- The member's or prescriber's preference for a less frequent dosing schedule
If applicable, the following will also not be considered as criteria to support the need for a drug requiring PA:
- The member's fear of needles
- The member's or prescriber's preference for the use of an oral agent
Supporting clinical information and a copy of the member's current medical records may be required with some PA requests. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Regardless whether the provider submits the member's medical records, the applicable PA form must sufficiently document supporting clinical information that the member meets PA criteria. If the submitted PA form does not clearly identify how the member meets PA criteria, the PA request may be returned or denied by ForwardHealth as incomplete.
Noncovered Drugs
Some drugs are not covered by Wisconsin Medicaid, BadgerCare Plus, or SeniorCare.
- Drugs when used for cosmetic use (such as eflornithine [Vaniqa], hydroquinone)
- Drugs when used for hair growth
- Less-than-effective drugs designated by the FDA
- Drugs without a manufacturer's rebate agreement
- Drugs when used to treat infertility (such as clomiphene, menotropins)
- Drugs when used to treat impotence (such as alprostadil, sildenafil)
Topic #19840 Strensiq
Strensiq requires clinical PA. PA requests for Strensiq must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form and the PA/RF.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
PA requests for Strensiq may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Strensiq
PA requests for Strensiq will only be approved for use to treat the following identified clinical conditions:
- Perinatal/infantile-onset HPP
- Juvenile-onset HPP
Clinical criteria that must be documented for approval of an initial PA request for Strensiq are all of the following:
- The member has perinatal/infantile-onset HPP or juvenile-onset HPP.
- The member was 18 years of age or younger at the onset of signs and/or symptoms of HPP.
- The member's current weight is provided.
- The member has clinical manifestations consistent with HPP (for example, skeletal abnormalities, respiratory problems, hypercalcemia, seizures).
- Findings on radiographic imaging support the diagnosis of HPP (for example, infantile rickets, alveolar bone loss, osteoporosis, low bone mineral content for age).
- The prescription is written by an endocrinologist or a provider who specializes in HPP.
- The member has a documented history of HPP-related skeletal abnormalities.
- The member has a serum alkaline phosphatase below the age-adjusted normal range.
- The member has a plasma pyridoxal-5'-phosphate level above the upper limit of normal.
- The member has a documented tissue-nonspecific alkaline phosphatase gene mutation.
Medical records must be provided to demonstrate the member meets the clinical criteria previously listed.
Note: A copy of the gene mutation testing must be included with an initial PA request.
If clinical criteria for Strensiq are met, initial PA requests may be approved for up to a maximum of 183 days.
Clinical criteria that must be documented for approval of an initial renewal PA request for Strensiq are all of the following:
- The member meets the clinical criteria for an initial PA request approval for Strensiq.
- The member has responded to treatment with Strensiq as evidenced by improvement in respiratory status, growth, or radiographic findings compared to their baseline prior to initiation of treatment with Strensiq.
Medical records must be provided to demonstrate that the member meets the clinical criteria previously listed.
Initial renewal PA requests for Strensiq may be approved for up to a maximum of 365 days.
Clinical criteria that must be documented for approval of a subsequent renewal PA request for Strensiq are all of the following:
- The member meets the clinical criteria for an initial PA request approval for Strensiq.
- The member has responded to treatment with Strensiq as evidenced by a sustained improvement in respiratory status, growth, or radiographic findings compared to their baseline prior to initiation of treatment with Strensiq.
Medical records must be provided to demonstrate that the member meets the clinical criteria previously listed.
Subsequent renewal PA requests for Strensiq may be approved for up to a maximum of 365 days. Topic #17857 Tasimelteon Tablets and Hetlioz LQ
Tasimelteon tablets and Hetlioz LQ require clinical PA.
PA requests for tasimelteon tablets or Hetlioz LQ must be completed, signed, and dated by the prescriber. PA requests for tasimelteon tablets or Hetlioz LQ must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of tasimelteon tablets or Hetlioz LQ must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for tasimelteon tablets or Hetlioz LQ may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Conditions for Which PA Requests for Use of Tasimelteon Tablets and Hetlioz LQ Will Be Considered for Review
PA requests for tasimelteon tablets or Hetlioz LQ will only be approved for use to treat the following identified clinical conditions:
- Non-24 (tasimelteon tablets PA requests only)
- Nighttime sleep disturbances in SMS (tasimelteon tablets and Hetlioz LQ PA requests)
Clinical Criteria for Tasimelteon Tablets for Members With Non-24-Hour Sleep-Wake Disorder
Clinical criteria that must be documented for approval of a PA request for tasimelteon tablets for members with Non-24 are all of the following:
- The member's age is consistent with the FDA-approved product labeling for tasimelteon tablets.
- The member has Non-24.
- One of the following is true:
- The member is totally blind (no light perception in either eye).
- The member is sighted (has light perception in either eye), and the following documentation has been submitted:
- The member has a history of insomnia, excessive daytime sleepiness, or both that alternates with time periods of being asymptomatic as the member rotates between alignment and misalignment with the environmental light-dark schedule.
- The member's symptoms have been present for at least three months.
- The member's daily sleep logs and actigraphy (for at least 14 days) have been submitted and demonstrate a gradual daily drift (typically later) in rest-activity patterns.
- The member's symptoms are not better explained by another current sleep, medical, neurologic, mental, or substance abuse disorder or medication use.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for tasimelteon tablets. The supporting clinical information and the medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for tasimelteon tablets are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for tasimelteon tablets may be approved for up to 365 days. Renewal PA requests for members who have Non-24 must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant increase in nighttime total sleep time or a decrease in daytime nap duration compared to the member's baseline prior to the initiation of tasimelteon tablets.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Tasimelteon Tablets and Hetlioz LQ for Members With Nighttime Sleep Disturbances in Smith-Magenis Syndrome
Clinical criteria that must be documented for approval of a PA request for tasimelteon tablets or Hetlioz LQ for members with nighttime sleep disturbances in SMS are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the drug requested.
- The member has nighttime sleep disturbances.
- The member has SMS.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for tasimelteon tablets or Hetlioz LQ. The supporting clinical information and the medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for tasimelteon tablets or Hetlioz LQ are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for tasimelteon tablets or Hetlioz LQ may be approved for up to 365 days. Renewal PA requests for members who have nighttime sleep disturbances in SMS must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant improvement in nighttime sleep quality compared to the member's baseline prior to the initiation of tasimelteon tablets or Hetlioz LQ.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #23842 Tremfya IV for Crohn's Disease and Ulcerative Colitis
Tremfya IV is a physician-administered drug that requires clinical PA.
All PA requests for Tremfya IV must be submitted with HCPCS procedure code J1628 (Injection, guselkumab, 1 mg).
PA requests for Tremfya IV must be completed, signed, and dated by the prescriber. PA requests for Tremfya IV must be submitted using Section V (Clinical Information for Physician-Administered Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) on the PA/PAD form. Clinical documentation supporting the use of Tremfya IV must be submitted with the PA request.
Prescribers are required to submit the completed PA/PAD form and a completed PA/RF to ForwardHealth.
PA requests for Tremfya IV may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Conditions for Which PA Requests for Use of Tremfya IV Will Be Considered for Review
ForwardHealth will only consider PA requests for Tremfya IV to treat these conditions:
- Crohn's disease
- Ulcerative colitis
Clinical Criteria for Tremfya IV for Crohn's Disease
Clinical criteria that must be documented for approval of a PA request for Tremfya IV for members with Crohn's disease are all of the following:
- The member has Crohn's disease.
- The member has been diagnosed by a gastroenterologist.
- Two of the following are true:
- The member has taken Cimzia for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Hadlima or Humira for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Selarsdi subQ or Steqeyma subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why Tremfya IV is being requested.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Tremfya IV for members with Crohn's disease. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
- The member's current weight
If the clinical criteria for Tremfya IV for members with Crohn's disease are met, PA requests will only be approved for three IV induction doses.
Note: A separate PA request must be obtained for maintenance treatment with Tremfya subQ. PA for Tremfya subQ must be obtained through the pharmacy PA process.
Clinical Criteria for Tremfya IV for Ulcerative Colitis
Clinical criteria that must be documented for approval of a PA request for Tremfya IV for members with ulcerative colitis are all of the following:
- The member has ulcerative colitis.
- The member has been diagnosed by a gastroenterologist.
- Two of the following are true:
- The member has taken Hadlima or Humira for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Selarsdi subQ or Steqeyma subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Simponi subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Xeljanz or Xeljanz XR for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why Tremfya IV is being requested.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Tremfya IV. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Tremfya IV are met, PA requests will only be approved for three IV induction doses.
Note: A separate PA request must be obtained for maintenance treatment with Tremfya subQ. PA for Tremfya subQ must be obtained through the pharmacy PA process. Topic #22377 Achondroplasia Drugs
Clinical PA is required for all achondroplasia drugs. Voxzogo and Yuviwel are achondroplasia drugs that require PA.
PA requests for achondroplasia drugs must be completed, signed, and dated by the prescriber. PA requests for achondroplasia drugs must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for achondroplasia drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Achondroplasia Drugs
The following clinical criteria must be met and documented for approval of a PA request for achondroplasia drugs:
- The member has achondroplasia.
- The achondroplasia drug must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The member's current height, weight, and growth velocity has been provided.
- The provider has submitted evidence that the member has open epiphyses.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for achondroplasia drugs. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for achondroplasia drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA Requests
Renewal PA requests for achondroplasia drugs may be approved for up to 183 days. Renewal PA requests must include copies of the member's current medical records demonstrating that the member had an increase in their growth velocity compared to their baseline prior to the initiation of achondroplasia drugs.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #24183 Voyxact
Voyxact requires clinical PA.
PA requests for Voyxact must be completed, signed, and dated by the prescriber. PA requests for Voyxact must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Voyxact must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Voyxact may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Voyxact
The following clinical criteria must be met and documented for approval of a PA request for Voyxact:
- Voyxact must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The prescription is written by, or in consultation with, a nephrologist or kidney transplant specialist.
- The member has biopsy-confirmed IgAN and is at risk for disease progression.
- The member's eGFR is equal to or greater than 30 mL/min.
- The member's uPCR is equal to or greater than 0.75 g/g in a 24-hour collection or their urine protein is equal to or greater than 1.0 g/day.
- The member is stable on a maximally tolerated dose of ACEi or ARB.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Voyxact. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If clinical criteria for Voyxact are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Voyxact may be approved for up to 365 days. Renewal PA requests require documentation to support that the member has a decrease in uPCR in a 24-hour collection or a urine total protein less than 1.0 g/day.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #23103 Vyjuvek
Vyjuvek requires clinical PA and is covered under the pharmacy benefit. Pharmacy providers should submit a pharmacy noncompound drug claim for Vyjuvek.
For questions about the billing or coverage of high cost, orphan, and accelerated approval drugs, providers may contact Provider Services or email dhsorphandrugs@dhs.wisconsin.gov.
Claim Requirements for Vyjuvek
Physician-administered Vyjuvek will be reimbursed separately from physician and clinical services associated with the administration of Vyjuvek.
The pharmacy provider is required to establish a delivery process with the prescriber to ensure that physician-administered Vyjuvek is delivered directly to the prescriber, an agent of the prescriber, or a health care provider designated to administer Vyjuvek to the member. Pharmacy providers may only submit a claim to ForwardHealth for the Vyjuvek that has been administered to a member.
If Vyjuvek has been dispensed for a member but the dose is not administered to the member, the prescriber or health care provider designated to administer Vyjuvek to the member is responsible for notifying the dispensing pharmacy. If ForwardHealth has paid the dispensing pharmacy for any portion of the dispensing of Vyjuvek that is not administered to the member, the dispensing pharmacy is responsible for reversing any claims submitted to ForwardHealth.
Clinical Criteria for Vyjuvek
The following clinical criteria must be met and documented for approval of a PA request for Vyjuvek:
- Vyjuvek must be prescribed by a dermatologist or wound care specialist.
- Vyjuvek must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The member has been diagnosed with dystrophic epidermolysis bullosa with mutation(s) in the collagen type VII alpha 1 chain gene.
- The prescriber must include documentation of at least one cutaneous wound that is appropriate to be treated with Vyjuvek and confirm that the wound does not appear to be infected.
- The prescriber must include documentation of the size of the wound area(s) to be treated and confirm the calculated dose of Vyjuvek will not exceed the recommended maximum weekly dose.
- The prescriber must include documentation that the member's treatment plan includes the appropriate administration of Vyjuvek by someone (a health care professional, caregiver, or the member themselves) who is trained on the wound dressing care requirements for treatment with Vyjuvek.
- The prescriber must include documentation that the member's treatment plan addresses the requirement for Vyjuvek to be properly prepared at a pharmacy for administration to the member's wound(s) within eight hours of mixing of the Vyjuvek gel with the Vyjuvek biological suspension.
Supporting clinical information and a copy of the member's current medical records must be included in all PA requests for Vyjuvek. The supporting clinical information and the medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If clinical criteria for Vyjuvek are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Vyjuvek may be approved for up to 365 days. Renewal PA requests must include supporting clinical information and copies of the member's current medical records.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen and demonstrate that the member has had a reduction in wound areas compared to baseline since starting treatment with Vyjuvek.
Submitting PA Requests for Vyjuvek
PA requests for Vyjuvek must be completed, signed, and dated by the prescriber. PA requests for Vyjuvek must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Vyjuvek must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Vyjuvek may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system). Topic #23838 Vykat XR
Vykat XR requires clinical PA.
PA requests for Vykat XR must be completed, signed, and dated by the prescriber. PA requests for Vykat XR must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Vykat XR must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Vykat XR may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Vykat XR
Clinical criteria for approval of a PA request for Vykat XR are all of the following:
- The member's age must be consistent with FDA-approved product labeling for Vykat XR.
- Vykat XR must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The member has hyperphagia with Prader-Willi Syndrome.
- The member has Prader-Willi Syndrome confirmed by genetic testing.
- The member's fasting plasma glucose and HbA1c have been tested and blood glucose has been optimized in patients with hyperglycemia.
- The prescriber will monitor fasting blood glucose at least once every week for the first two weeks, then at least once every four weeks as clinically indicated.
- The prescriber will monitor HbA1c every three months and as clinically indicated.
- The prescription is written by or through consultation with an endocrinologist.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Vykat XR. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
- The member's current weight
If clinical criteria for Vykat XR are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Vykat XR may be approved for up to 183 days. Renewal PA requests must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a reduction in hyperphagic symptoms compared to their baseline prior to the initiation of Vykat XR.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #21437 Wakix
Wakix requires clinical PA.
PA requests for Wakix must be completed, signed, and dated by the prescriber. PA requests for Wakix must be submitted using the Prior Authorization Drug Attachment for Wakix form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Wakix form and a completed PA/RF to ForwardHealth.
PA requests for Wakix may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Wakix
PA requests for Wakix will only be approved for use to treat the following symptoms of narcolepsy:
Narcolepsy With Cataplexy
Clinical criteria for approval of a PA request for Wakix to treat narcolepsy with cataplexy are all of the following:
- The member has narcolepsy with cataplexy.
- The member's age must be consistent with FDA-approved product labeling for Wakix.
- The prescriber has reviewed the member's current medication list to evaluate for potential drug interactions (for example, CYP2D6 inhibitors, CYP3A4 inducers, and drugs that increase the QT interval).
- The member is not currently taking any sedative hypnotics.
- For members currently taking CNS depressants (for example, anxiolytics, barbiturates, or opioids), the prescriber has evaluated the CNS depressants and determined they are not contributing to the member's daytime sleepiness.
- An overnight PSG sleep study and MSLT have been performed for the member using standard protocols, and the prescribing provider has submitted medical record documentation supporting a clinical correlation between the test results and a diagnosis of narcolepsy.
- The overnight PSG test results and provider interpretation have been submitted with the PA request and include documentation of the following:
- Total sleep time documented is at least 360 minutes.
- The member experienced minimal sleep interruptions (for example, respiratory events or periodic leg movements).
- Provider interpretation indicates that an adequate night's sleep was achieved.
- The MSLT results and provider interpretation have been submitted with the PA request and include documentation of the following:
- The MSLT was conducted the morning after the overnight PSG.
- Average sleep latency for all naps is eight minutes or less.
- The member achieved at least two SOREMPs. A SOREMP period within 15 minutes of sleep onset on the preceding nocturnal PSG may replace one of the SOREMPs on the MSLT.
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with a stimulant.
- The member has a medical condition(s) that prevents treatment with a stimulant.
- There is a clinically significant drug interaction between another medication the member is taking and stimulants.
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response that occurred after the medication had been titrated to a maximum recommended daily dose or experienced a clinically significant adverse drug reaction with armodafinil or modafinil.
- The member has a medical condition(s) that prevents treatment with armodafinil or modafinil.
- There is a clinically significant drug interaction between another medication the member is taking and armodafinil or modafinil.
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction to at least one of the following:
Initial PA requests for Wakix may be approved for up to 183 days.
In addition to documenting the previously listed clinical information on the Prior Authorization Drug Attachment for Wakix form, medical records must be submitted with the PA request to support the member's condition of narcolepsy with cataplexy.
Renewal PA requests may be approved for up to 365 days. Medical records must be submitted demonstrating clinical improvement, including a decrease in cataplexy or a decrease in the member's EDS. A decrease in a member's EDS must be supported by an ESS questionnaire, MWT, or MSLT. Medical records must also reflect patient compliance with medication use.
Narcolepsy Without Cataplexy
Clinical criteria for approval of a PA request for Wakix to treat narcolepsy without cataplexy are all of the following:
- The member has narcolepsy without cataplexy.
- The member's age must be consistent with FDA-approved product labeling for Wakix.
- The prescriber has reviewed the member's current medication list to evaluate for potential drug interactions (for example, CYP2D6 inhibitors, CYP3A4 inducers, and drugs that increase the QT interval).
- The member is not currently taking any sedative hypnotics.
- For members currently taking CNS depressants (for example, anxiolytics, barbiturates, or opioids), the prescriber has evaluated the CNS depressants and determined they are not contributing to the member's daytime sleepiness.
- An overnight PSG sleep study and MSLT have been performed for the member using standard protocols, and the prescribing provider has submitted medical record documentation supporting a clinical correlation between the test results and a diagnosis of narcolepsy.
- The overnight PSG test results and provider interpretation have been submitted with the PA request and include documentation of the following:
- Total sleep time documented is at least 360 minutes.
- The member experienced minimal sleep interruptions (for example, respiratory events or periodic leg movements).
- Provider interpretation indicates that an adequate night's sleep was achieved.
- The MSLT results and provider interpretation have been submitted with the PA request and include documentation of the following:
- The MSLT was conducted the morning after the overnight PSG.
- Average sleep latency for all naps is eight minutes or less.
- The member achieved at least two SOREMPs. A SOREMP period within 15 minutes of sleep onset on the preceding nocturnal PSG may replace one of the SOREMPs on the MSLT.
- The member has EDS that interferes with normal activities on a daily basis.
- An ESS questionnaire, MWT, or MSLT has been performed for the member, confirming that the member has EDS. (Note: Test results for the ESS questionnaire, the MWT, or MSLT must be submitted with the PA request.)
- The prescriber ruled out or treated the member for other causes of EDS including:
- Other sleep disorders, including sleep apnea.
- Chronic pain or illness that disrupts normal sleep patterns.
- Mood disorders such as depression.
- Caffeine or nicotine use causing poor quality of nighttime sleep.
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with a stimulant.
- The member has a medical condition(s) that prevents treatment with a stimulant.
- There is a clinically significant drug interaction between another medication the member is taking and stimulants.
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response that occurred after the medication had been titrated to a maximum recommended daily dose or experienced a clinically significant adverse drug reaction with armodafinil or modafinil.
- The member has a medical condition(s) that prevents treatment with armodafinil or modafinil.
- There is a clinically significant drug interaction between another medication the member is taking and armodafinil or modafinil.
Initial PA requests for Wakix may be approved for up to 183 days.
In addition to documenting the previously listed clinical information on the Prior Authorization Drug Attachment for Wakix form, medical records must be submitted with the PA request to support the member's condition of narcolepsy without cataplexy.
Renewal PA requests may be approved for up to 365 days. Medical records must be submitted demonstrating clinical improvement, including a decrease in the member's EDS. A decrease in a member's EDS must be supported by an ESS questionnaire, MWT, or MSLT. Medical records must also reflect patient compliance with medication use. Topic #16437 Xyrem and Xywav
Xyrem and Xywav require clinical PA.
PA requests for Xyrem or Xywav must be completed, signed, and dated by the prescriber. PA requests Xyrem or Xywav must be submitted using the Prior Authorization Drug Attachment for Xyrem and Xywav form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Xyrem and Xywav form and a completed PA/RF.
PA requests for Xyrem or Xywav may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Quantity limits apply to Xyrem and Xywav. Members are limited to a maximum nightly dose of 18 mL (9 g) of Xyrem or Xywav, which is equivalent to 540 mL (270 g) of Xyrem or Xywav per month.
PA requests for Xyrem or Xywav will only be approved for one drug per member. ForwardHealth does not cover treatment with both Xyrem and Xywav.
Clinical Criteria for Xyrem and Xywav
PA requests for Xyrem or Xywav will only be approved to treat one of the following:
- Symptoms of narcolepsy:
- Idiopathic hypersomnia
Narcolepsy With Cataplexy
Clinical criteria for approval of a PA request for Xyrem or Xywav to treat narcolepsy with cataplexy are all of the following:
- The member has narcolepsy with cataplexy.
- The member is 7 years of age or older.
- The member does not have a succinic semialdehyde dehydrogenase deficiency.
- The prescriber has counseled the member on the contraindication between Xyrem or Xywav and alcohol.
- The member has agreed to be abstinent from alcohol while being treated with Xyrem or Xywav.
- The member does not have a history of substance abuse, addiction, or diversion.
- The member is not currently taking any sedative hypnotics.
- For members currently taking CNS depressants (for example, anxiolytics, barbiturates, or opioids), the prescriber has evaluated the CNS depressants and determined they are not contributing to the member's daytime sleepiness.
- An overnight PSG sleep study and MSLT have been performed for the member using standard protocols, and the prescribing provider has submitted medical record documentation supporting a clinical correlation between the test results and a diagnosis of narcolepsy with cataplexy.
- The overnight PSG test results and provider interpretation have been submitted with the PA request and include documentation of the following:
- Total sleep time documented is at least 360 minutes.
- The member experienced minimal sleep interruptions (for example, respiratory events or periodic leg movements).
- Provider interpretation indicates an adequate night's sleep was achieved.
- The MSLT results and provider interpretation have been submitted with the PA request and include documentation of the following:
- The MSLT was conducted the morning after the overnight PSG.
- Average sleep latency for all naps is eight minutes or less.
- The member achieved at least two SOREMPs. A SOREMP within 15 minutes of sleep onset on the preceding nocturnal PSG may replace one of the SOREMPs on the MSLT.
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with a stimulant.
- The member has a medical condition(s) that prevents treatment with a stimulant.
- There is a clinically significant drug interaction(s) with another medication(s) the member is taking and a stimulant.
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response that occurred after the medication had been titrated to a maximum recommended daily dose or experienced a clinically significant adverse drug reaction with armodafinil or modafinil.
- The member has a medical condition(s) that prevents treatment with armodafinil or modafinil.
- There is a clinically significant drug interaction(s) with another medication(s) the member is taking and armodafinil or modafinil.
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction to at least one of the following:
Note: The prescriber is required to submit detailed clinical justification for prescribing Xywav instead of Xyrem. The clinical information must document why the member cannot use Xyrem, including why it is medically necessary that the member receive Xywav instead of Xyrem.
Initial PA requests for Xyrem or Xywav to treat narcolepsy with cataplexy may be approved for up to 183 days.
In addition to documenting the previously listed clinical information on the Prior Authorization Drug Attachment for Xyrem and Xywav form, medical records must be submitted with the PA request to support the member's medical condition of narcolepsy with cataplexy.
Renewal PA requests may be approved for up to 365 days. Medical records must be submitted demonstrating clinical improvement, including a decrease in cataplexy or a decrease in the member's EDS. A decrease in a member's EDS must be supported by an ESS questionnaire, MWT, or MSLT. Medical records must also reflect patient compliance with medication use and safety precautions for Xyrem or Xywav.
Narcolepsy Without Cataplexy
Clinical criteria for approval of a PA request for Xyrem or Xywav to treat narcolepsy without cataplexy are all of the following:
- The member has narcolepsy without cataplexy.
- The member is 7 years of age or older.
- The member does not have a succinic semialdehyde dehydrogenase deficiency.
- The prescriber has counseled the member on the contraindication between Xyrem or Xywav and alcohol.
- The member has agreed to be abstinent from alcohol while being treated with Xyrem or Xywav.
- The member does not have a history of substance abuse, addiction, or diversion.
- The member is not currently taking any sedative hypnotics.
- For members currently taking CNS depressants (for example, anxiolytics, barbiturates, or opioids), the prescriber has evaluated the CNS depressants and determined they are not contributing to the member's daytime sleepiness.
- An overnight PSG sleep study and MSLT have been performed for the member using standard protocols, and the prescribing provider has submitted medical record documentation supporting a clinical correlation between the test results and a diagnosis of narcolepsy without cataplexy.
- The overnight PSG test results and provider interpretation have been submitted with the PA request and include documentation of the following:
- Total sleep time documented is at least 360 minutes.
- The member experienced minimal sleep interruptions (for example, respiratory events or periodic leg movements).
- Provider interpretation indicates an adequate night's sleep was achieved.
- The MSLT results and provider interpretation have been submitted with the PA request and include documentation of the following:
- The MSLT was conducted the morning after the overnight PSG.
- Average sleep latency for all naps is eight minutes or less.
- The member achieved at least two SOREMPs. A SOREMP within 15 minutes of sleep onset on the preceding nocturnal PSG may replace one of the SOREMPs on the MSLT.
- The member has EDS that interferes with normal activities on a daily basis.
- An ESS questionnaire, MWT, or MSLT has been performed for the member, confirming that the member has EDS. (Note: Test results for the ESS questionnaire, MWT, or MSLT must be submitted with the PA request.)
- The prescriber ruled out or treated the member for other causes of EDS, including:
- Other sleep disorders, including sleep apnea.
- Chronic pain or illness that disrupts normal sleep patterns.
- Mood disorders such as depression.
- Caffeine or nicotine use causing poor quality of nighttime sleep.
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with a stimulant.
- The member has a medical condition(s) that prevents treatment with a stimulant.
- There is a clinically significant drug interaction(s) with another medication(s) the member is taking and a stimulant.
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response that occurred after the medication had been titrated to a maximum recommended daily dose or experienced a clinically significant adverse drug reaction with armodafinil or modafinil.
- The member has a medical condition(s) that prevents treatment with armodafinil or modafinil.
- There is a clinically significant drug interaction(s) with another medication(s) the member is taking and armodafinil or modafinil.
Note: The prescriber is required to submit detailed clinical justification for prescribing Xywav instead of Xyrem. The clinical information must document why the member cannot use Xyrem, including why it is medically necessary that the member receive Xywav instead of Xyrem.
Initial PA requests for Xyrem or Xywav to treat narcolepsy without cataplexy may be approved for up to 183 days.
In addition to documenting the previously listed clinical information on the Prior Authorization Drug Attachment for Xyrem and Xywav form, medical records must be submitted with the PA request to support the member's medical condition of narcolepsy without cataplexy.
Renewal PA requests may be approved for up to 365 days. Medical records must be submitted demonstrating clinical improvement, including a decrease in the member's EDS. A decrease in a member's EDS must be supported by an ESS questionnaire, MWT, or MSLT. Medical records must also reflect patient compliance with medication use and safety precautions for Xyrem or Xywav.
Idiopathic Hypersomnia
Clinical criteria for approval of a PA request for Xyrem or Xywav to treat idiopathic hypersomnia are all of the following:
- The member has idiopathic hypersomnia.
- The member is 18 years of age or older.
- The member does not have a succinic semialdehyde dehydrogenase deficiency.
- The prescriber has counseled the member on the contraindication between Xyrem or Xywav and alcohol.
- The member has agreed to be abstinent from alcohol while being treated with Xyrem or Xywav.
- The member does not have a history of substance abuse, addiction, or diversion.
- The member is not currently taking any sedative hypnotics.
- For members currently taking CNS depressants (for example, anxiolytics, barbiturates, or opioids), the prescriber has evaluated the CNS depressants and determined they are not contributing to the member's daytime sleepiness.
- An overnight PSG sleep study and MSLT have been performed for the member using standard protocols, and the prescribing provider has submitted medical record documentation supporting a clinical correlation between the test results and a diagnosis of idiopathic hypersomnia.
- The overnight PSG test results and provider interpretation have been submitted with the PA request and include documentation of the following:
- Total sleep time documented is at least 360 minutes.
- The member experienced minimal sleep interruptions (for example, respiratory events or periodic leg movements).
- Provider interpretation indicates an adequate night's sleep was achieved.
- The MSLT results and provider interpretation have been submitted with the PA request and include documentation of the following:
- The MSLT was conducted the morning after the overnight PSG.
- Average sleep latency for all naps is eight minutes or less.
- The member achieved fewer than two SOREMPs or no SOREMPs if the REM sleep latency on the preceding nocturnal PSG was 15 minutes or less.
- The member has EDS that interferes with normal activities on a daily basis.
- An ESS questionnaire, MWT, or MSLT has been performed for the member, confirming that the member has EDS. (Note: Test results for the ESS questionnaire, MWT, or MSLT must be submitted with the PA request.)
- The prescriber ruled out or treated the member for other causes of EDS, including:
- Other sleep disorders, including sleep apnea.
- Chronic pain or illness that disrupts normal sleep patterns.
- Mood disorders such as depression.
- Caffeine or nicotine use causing poor quality of nighttime sleep.
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response that occurred after the medication had been titrated to a maximum recommended daily dose or experienced a clinically significant adverse drug reaction with armodafinil or modafinil.
- The member has a medical condition(s) that prevents treatment with armodafinil or modafinil.
- There is a clinically significant drug interaction(s) with another medication(s) the member is taking and armodafinil or modafinil.
Initial PA requests for Xyrem or Xywav to treat idiopathic hypersomnia may be approved for up to 183 days.
In addition to documenting the previously listed clinical information on the Prior Authorization Drug Attachment for Xyrem and Xywav form, medical records must be submitted with the PA request to support the member's medical condition of idiopathic hypersomnia.
Renewal PA requests may be approved for up to 365 days. Medical records must be submitted demonstrating clinical improvement, including a decrease in the member's EDS. A decrease in a member's EDS must be supported by an ESS questionnaire, MWT, or MSLT. Medical records must also reflect patient compliance with medication use and safety precautions for Xyrem or Xywav. Topic #23339 Zokinvy
Zokinvy requires clinical PA.
PA requests for Zokinvy must be completed, signed, and dated by the prescriber. PA requests for Zokinvy must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Zokinvy must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Zokinvy may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval, including what may not be considered criteria to support the need for a drug.
Clinical Criteria for Zokinvy
Clinical criteria that must be documented for approval of a PA request for Zokinvy are all of the following:
- Zokinvy is being prescribed in a dose and manner consistent with FDA-approved product labeling.
- One of the following is true:
- The member has Hutchinson-Gilford Progeria Syndrome.
- The member has a processing-deficient Progeroid Laminopathy with one of the following:
- Heterozygous LMNA mutation with progerin-like protein accumulation
- Homozygous or compound heterozygous ZMPSTE24 mutations
- The member is not taking any strong or moderate CYP3A inhibitors or inducers.
- The member is not taking midazolam.
- The member is not taking lovastatin, simvastatin, or atorvastatin.
- The member's current height and weight have been documented.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Zokinvy. The supporting clinical information and the medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Zokinvy are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Zokinvy may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #23357 Zynteglo
Clinical PA is required for Zynteglo.
If a PA request for Zynteglo is approved, Zynteglo will be covered under the pharmacy benefit.
To bill ForwardHealth for Zynteglo, pharmacy providers should submit a pharmacy noncompound drug claim.
For questions about the billing or coverage of high cost, orphan, and accelerated approval drugs, providers may contact Provider Services or email DHSOrphanDrugs@dhs.wisconsin.gov.
Additional Requirements for Zynteglo
Zynteglo will be reimbursed separately from physician and clinical services associated with the administration of Zynteglo. The pharmacy provider is required to establish a delivery process with the prescriber to ensure that the physician-administered Zynteglo is delivered directly to the prescriber or an agent of the prescriber.
Pharmacy providers may only submit a claim to ForwardHealth for the Zynteglo that has been administered to a member. If Zynteglo has been dispensed for a member but the dose is not administered to the member, the prescriber is responsible for notifying the dispensing pharmacy. If ForwardHealth has paid the dispensing pharmacy for any portion of the dispensing of Zynteglo that is not administered to the member, the dispensing pharmacy is responsible for reversing any claims submitted to ForwardHealth.
Clinical Criteria for Zynteglo
Clinical criteria that must be documented for approval of a PA request for Zynteglo are all of the following:
- Zynteglo must be prescribed by a physician with expertise in treating β-thalassemia at a minimum recommended dose of 5.0 X 10⁶ CD34+ cells/kg of body weight.
- The member has β-thalassemia, which requires regular RBC transfusions. The member has a history of transfusions for the past two years of at least 100 mL/kg/year of packed RBCs or with eight or more transfusions of packed RBCs per year.
- The member's age is consistent with the FDA-approved product labeling for Zynteglo.
- The member will undergo HSC mobilization, apheresis, and myeloablative conditioning. The prescriber must confirm the member has been evaluated for renal and hepatic impairment and HSC transplantation is appropriate for the member.
- The member must have full myeloablative conditioning administered before infusion of Zynteglo. Allow a minimum of 48 hours of washout before Zynteglo infusion.
- The prescriber will complete screening for infectious diseases including HBV, HCV, HIV 1 and 2 (HIV-1/HIV-2) and HTLV 1 and 2 (HTLV-1/HTLV-2) in accordance with clinical guidelines before collection of cells for manufacturing.
- Standard procedures for patient management after HSC transplantation should be followed after Zynteglo infusion.
- The prescriber must manage other concomitant medications (as applicable) consistent with FDA product labeling.
- The member must not take anti-retroviral medications or hydroxyurea for at least one month prior to mobilization, or for the expected duration for elimination of the medications, and until all cycles of apheresis are completed.
- If a member requires anti-retroviral medications for HIV prophylaxis, mobilization and apheresis should be delayed until HIV infection is adequately ruled out.
- The member must stop iron chelation at least seven days prior to myeloablative conditioning. The member will not use myelosuppressive iron chelators for at least six months after Zynteglo infusion.
PA requests for Zynteglo will not be approved if the member has any of the following conditions:
- Advanced liver disease (for example, alanine transaminases greater than three times the upper limit of normal, direct bilirubin value greater than 2.5 times the upper limit of normal, baseline prothrombin time [INR] greater than 1.5 times the upper limit of normal, cirrhosis, bridging fibrosis, or active hepatitis)
- Prior or current malignancy or myeloproliferative disorder or significant immunodeficiency disorder
- Prior allogenic or autologous HSC transplant
Submitting PA Requests for Zynteglo
PA requests for Zynteglo must be completed, signed, and dated by the prescriber. PA requests for Zynteglo must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Zynteglo must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Zynteglo may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug. Topic #24323 Wegovy Injection and Wegovy Tablets
Wegovy injection and Wegovy tablets require clinical PA.
PA requests for Wegovy injection or Wegovy tablets must be completed, signed, and dated by the prescriber. PA requests for Wegovy injection or Wegovy tablets must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Wegovy injection or Wegovy tablets must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Wegovy injection or Wegovy tablets may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Conditions for Which PA Requests for Use of Wegovy Injection or Wegovy Tablets Will Be Considered for Review
PA requests for Wegovy injection will only be approved for use in the identified clinical conditions:
- To reduce the risk of MACE in overweight or obese adults with established cardiovascular disease
- To treat MASH in adults
- To reduce excess body weight and maintain weight reduction long term in pediatric patients aged 12–17 years old with obesity
PA requests for Wegovy tablets will only be approved to reduce the risk of MACE in overweight or obese adults with established cardiovascular disease.
Clinical Criteria for Wegovy Injection and Wegovy Tablets to Reduce the Risk of Major Adverse Cardiovascular Events in Overweight or Obese Adults With Established Cardiovascular Disease
Clinical criteria that must be documented for approval of a PA request for Wegovy injection or Wegovy tablets to reduce the risk of MACE in overweight or obese adults with established cardiovascular disease are all of the following:
- Wegovy must be prescribed in a dose and manner consistent with the FDA-approved product labeling.
- The member has established cardiovascular disease, as evidenced by one of the following:
- Prior myocardial infarction (heart attack)
- Prior stroke
- Peripheral arterial disease as evidenced by one of the following:
- Intermittent claudication with an ABI of less than or equal to 0.9
- Peripheral arterial revascularization procedure or amputation that is due to atherosclerotic disease
- The member has a BMI greater than or equal to 27.
- The member has agreed to follow a reduced-calorie diet and increase their physical activity.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Wegovy injection or Wegovy tablets to reduce the risk of MACE in overweight or obese adults with established cardiovascular disease. The supporting clinical information and medical records must document the following:
- Evidence that the member has established cardiovascular disease
- The member's current BMI (within the past three months)
- The member's current treatment plan
If clinical criteria for Wegovy injection or Wegovy tablets to reduce the risk of MACE in overweight or obese adults with established cardiovascular disease are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests require documentation to support the member continues to follow a reduced-calorie diet and maintains physical activity. A copy of the member's current medical records must be included with the PA request.
Renewal PA requests for Wegovy injection or Wegovy tablets to reduce the risk of MACE in overweight or obese adults with established cardiovascular disease may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Wegovy Injection to Treat Metabolic Dysfunction-Associated Steatohepatitis
Clinical criteria that must be documented for approval of a PA request for Wegovy injection to treat MASH are all of the following:
- Wegovy must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The member has been diagnosed with noncirrhotic MASH, formerly known as NASH, with moderate to advanced liver fibrosis (consistent with stages F2 to F3 fibrosis) by a biopsy or noninvasive tests (such as FibroScan or MRE + MRI-PDFF).
- The member has agreed to follow a reduced-calorie diet and increase their physical activity.
- The prescription is written by a liver specialist physician such as a gastroenterologist or hepatologist.
- The prescriber will monitor for elevations in liver tests and development of liver-related adverse reactions.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Wegovy injection to treat MASH. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Wegovy injection to treat MASH are met, initial PA requests may be approved for up to 183 days.
Initial Renewal PA Request
Initial renewal PA requests require documentation to support that the member is responding adequately to treatment (as documented in laboratory tests). A copy of the member's current medical records must be included with the PA request. Initial renewal PA requests for Wegovy injection to treat MASH may be approved for up to 183 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Subsequent Renewal PA Requests
Subsequent renewal PA requests require documentation to support that the member is responding adequately to treatment (as documented in laboratory tests and a biopsy or noninvasive tests [such as FibroScan or MRE + MRI-PDFF]) and has resolution of steatohepatitis without worsening of fibrosis or at least one stage improvement in fibrosis without worsening of steatohepatitis. A copy of the member's current medical records must be included with the PA request. Subsequent renewal PA requests for Wegovy injection to treat MASH may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Wegovy Injection to Reduce Excess Body Weight and Maintain Weight Reduction Long Term in Pediatric Patients Aged 12 Years and Older With Obesity
Clinical criteria that must be documented for approval of a PA request for Wegovy injection to reduce excess body weight and maintain weight reduction long term in pediatric patients aged 12 years and older with obesity are all of the following:
- Wegovy must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The member is 12–17 years of age.
- The member has a BMI greater than or equal to the 95th percentile standardized by age and gender.
- The member has agreed to follow a reduced-calorie diet and increase their physical activity.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Wegovy injection to reduce excess body weight and maintain weight reduction long term in pediatric patients aged 12 years and older with obesity. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- The member's current BMI (within the past three months)
- The member's current treatment plan
If the clinical criteria for Wegovy injection to reduce excess body weight and maintain weight reduction long term in pediatric patients aged 12 years and older with obesity are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests require documentation to support the member has had a reduction in BMI compared to their baseline prior to the initiation of Wegovy injection. A copy of the member's current medical records must be included with the PA request. Renewal PA requests for Wegovy injection to reduce excess body weight and maintain weight reduction long term in pediatric patients aged 12 years and older with obesity may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #960 An Overview
Depending on the service being requested, most PA requests must be comprised of the following:
Topic #446 Attachments
In addition to the PA/RF or PA/DRF, a service-specific PA attachment must be submitted with each PA request. The PA attachment allows a provider to document the clinical information used to determine whether or not the standards of medical necessity are met for the requested service(s). Providers should include adequate information for ForwardHealth to make a reasonable judgment about the case.
To reduce processing time for mailed or faxed pharmacy PA requests, ForwardHealth will scan each form with a barcode as it is received. Topic #447 Obtaining Forms and Attachments
Only pharmacy providers may obtain paper versions of all PA forms and attachments. All other providers must complete most PA attachments from the ForwardHealth Portal.
Paper Forms (for Pharmacy Providers Only)
Paper versions of all PA forms and PA attachments are available by writing to ForwardHealth. Include a return address, the name of the form, the form number (if applicable), and mail the request to the following address:
ForwardHealth
Form Reorder
313 Blettner Blvd
Madison WI 53784
Providers may also call Provider Services to order paper copies of forms.
Downloadable Forms (for Pharmacy Providers Only)
Most PA attachments can be downloaded and printed in their original format from the Portal. Many forms are available in fillable PDF and fillable Microsoft Word formats.
Web PA Via the Portal
Providers may complete the PA/RF and PA attachments through the Portal. Topic #4620 Pharmacy Prior Authorization Forms
PA/PDL forms, PA drug attachment forms, and the PA/DGA form are available on the Forms page of the ForwardHealth Portal. Topic #448 Prior Authorization Request Form
The PA/RF is used by ForwardHealth and is mandatory for most providers when requesting PA. The PA/RF serves as the cover page of a PA request.
Note: When submitting PA requests on the Portal, providers will see panels that will prompt them to answer the questions on the PA/RF. The Portal will generate a PA/RF for them at the end of the process.
Providers are required to complete the basic provider, member, and service information on the PA/RF. Each PA request is assigned a unique ten-digit number. ForwardHealth remittance information will report to the provider the PA number used to process the claim for prior authorized services.
Under Wis. Stat. § 49.45(4), personally identifiable information about program applicants and members is confidential and is used for purposes directly related to ForwardHealth administration such as determining eligibility of the applicant, processing PA requests, or processing provider claims for reimbursement. The use of the PA/RF is mandatory to receive PA for certain items. Failure to supply the information requested by the form may result in denial of PA or payment for the service.
The provision of services that are greater than or significantly different from those authorized may result in nonpayment of the billing claim(s).
Providers should use the following process types on the PA/RF to request PA for the corresponding service areas.
| Process Type |
Description |
| 111 |
Physical therapy |
| 112 |
Occupational therapy |
| 113 |
Speech and language therapy |
| 117 |
Physician services, including rural health clinics and federally qualified health centers |
| Physician-administered drugs |
| Botox to treat migraines |
| IV ketamine infusion therapy |
| 118 |
Chiropractic |
| 120 |
Home care |
| Home health therapy |
| Intermittent skilled nursing |
| Private duty nursing |
| 121 |
Personal care |
| 122 |
Vision |
| 123 |
Audiology/Hearing aid |
| 124 |
Dental |
| 125 |
Orthodontics |
| 126 |
Intensive in-home treatment service, HealthCheck Other Service |
| 127 |
Genetic testing |
| 129 |
Child/adolescent day treatment, a HealthCheck Other Service |
| Adult mental health day treatment |
| 130 |
DME: Wheelchairs, accessories, and home health equipment |
| DME: Pediatric hospital beds and cribs |
| 131 |
Drugs |
| 132 |
DMS |
| 133 |
Transplants |
| 135 |
Ventilators |
| 136 |
Substance abuse day treatment |
| 139 |
Oxygen and respiratory equipment |
| 140 |
DME: Orthotics, footwear, prosthetics |
| 142 |
Behavioral treatment |
| 145 |
Residential substance use disorder |
| 146 |
Housing support |
| 148 |
Intensive outpatient program |
| 160 |
Physical therapy Birth to 3 |
| 161 |
Occupational therapy Birth to 3 |
| 162 |
Speech and language therapy Birth to 3 |
| 999 |
Brain injury |
| Ambulance |
Topic #4619 Prior Authorization Request Form Completion Instructions for Pharmacy Services and Diabetic Supplies
ForwardHealth requires certain information to enable the programs to authorize and pay for medical services provided to eligible members.
Members of ForwardHealth are required to give providers full, correct, and truthful information for the submission of correct and complete claims for reimbursement. This information should include, but is not limited to, information concerning enrollment status, accurate name, address, and member
identification number (Wis. Admin. Code § DHS 104.02[4]).
Under Wis. Stat. § 49.45(4), personally identifiable information about program applicants and members is confidential and is used for purposes directly related to ForwardHealth administration such as determining eligibility of the applicant, processing PA requests, or processing provider claims for reimbursement. The use of the PA/RF is mandatory to receive PA for certain items. Failure to supply the information requested by the form may result in denial of PA or payment for the service.
Providers should make duplicate copies of all paper documents mailed to ForwardHealth. Providers may submit PA requests, along with all applicable service-specific attachments, via the ForwardHealth Portal, by fax to ForwardHealth at 608-221-8616, or by mail to the following address:
ForwardHealth
Prior Authorization
Ste 88
313 Blettner Blvd
Madison WI 53784
The provision of services that are greater than or significantly different
from those authorized may result in nonpayment of the billing claim(s).
SECTION I ― PROVIDER INFORMATION
Element 1 — HealthCheck Other Services and Wisconsin Chronic Disease
Program (WCDP)
Enter an "X" in the box next to HealthCheck Other Services if the
services requested on the PA/RF are for HealthCheck Other Services. Enter an "X" in the box next to
WCDP if the services requested on the PA/RF
are for a WCDP member.
Element 2 — Process Type
Enter the process type 131 — Drugs. The process type is a three-digit code
used to identify a category of service requested.
Element 3 — Phone Number — Billing Provider
Enter the phone number, including the area code, of the office, clinic,
facility, or place of business of the billing provider.
Element 4 — Name and Address — Billing Provider
Enter the name and complete address (street, city, state, and ZIP+4 code)
of the billing provider. Providers are required to include both the ZIP code
and the four-digit extension for timely and accurate billing. The name listed
in this element must correspond with the billing provider number listed in
Element 5a.
Element 5a — Billing Provider Number
Enter the NPI of the billing provider. The
NPI in this element must correspond with the provider name listed in Element
4.
Element 5b — Billing Provider Taxonomy Code
Enter the national 10-digit alphanumeric taxonomy code that corresponds to
the NPI of the billing provider in Element 5a.
Element 6a — Name — Prescribing / Referring / Ordering Provider
Enter the prescribing provider's name.
Element 6b — National Provider Identifier — Prescribing / Referring / Ordering Provider
Enter the prescribing provider's 10-digit NPI.
SECTION II ― MEMBER INFORMATION
Element 7 — Member ID Number
Enter the member ID. Do not enter any other numbers or letters. Use the
ForwardHealth identification card or Wisconsin's EVS to obtain the correct number.
Element 8 — Date of Birth — Member
Enter the member's date of birth in mm/dd/ccyy format.
Element 9 — Name — Member
Enter the member's last name, followed by their first name and middle
initial. Use the EVS to obtain the correct spelling of the member's name. If
the name or spelling of the name on the ForwardHealth card and the EVS do not
match, use the spelling from the EVS.
Element 10 — Address — Member
Enter the complete address of the member's place of residence, including
the street, city, state, and ZIP code. If the member is a resident of a
nursing home or other facility, include the name of the nursing home or
facility.
SECTION III — DIAGNOSIS / TREATMENT INFORMATION
Element 11 — Diagnosis — Primary Code and Description
Enter the appropriate ICD diagnosis code and description with the highest level of specificity most relevant to the service/procedure requested. The ICD diagnosis code must correspond with the ICD description.
Element 12 — Diagnosis — Secondary Code and Description
Enter the appropriate secondary ICD diagnosis code and description with the highest level of specificity most
relevant to the service/procedure requested, if applicable. The ICD diagnosis code must correspond with the ICD description.
Element 13 — Requested PA Start Date
Enter the requested start DOS in mm/dd/ccyy format, if a specific start date is requested.
Element 14 — Rendering Provider Number
Enter the provider ID of the provider who will be performing the service,
only if this number is different from the billing provider ID listed in
Element 5a.
Element 15 — Rendering Provider Taxonomy Code
Enter the national 10-digit alphanumeric taxonomy code that corresponds to
the provider who will be performing the service, only if this code is
different from the taxonomy code listed for the billing provider in Element
5b.
Element 16 — Service Code or National Drug Code (NDC)
Enter the appropriate NDC for each
service/procedure/item requested.
Element 17 — Modifiers
Enter the modifier(s) corresponding to the service code listed if a modifier
is required.
Element 18 — POS
Enter the appropriate place of service code designating where the requested item would be
provided/performed/dispensed.
Element 19 — Description of Service or Drug Name and Strength
Enter a written description corresponding to the appropriate NDC for
each item requested.
Element 20 — Quantity
Enter the appropriate quantity (for example, days' supply) requested for the
procedure code listed.
Element 21 — Charge
Enter the provider's usual and customary charge for each
service/procedure/item requested. If the quantity is greater than "1.0,"
multiply the quantity by the charge for each service/procedure/item requested.
Enter that total amount in this element.
Note: The charges indicated on the request form should reflect
the provider's usual and customary charge for the procedure requested.
Providers are reimbursed for authorized services according to provider
Terms of Reimbursement issued by the Wisconsin DHS.
Element 22 — Total Charges
Enter the anticipated total charges for this request.
Element 23 — Signature — Requesting Provider
The original signature of the provider requesting/performing/dispensing
this service/procedure/item must appear in this element.
Element 24 — Date Signed
Enter the month, day, and year the PA/RF was signed (in mm/dd/ccyy format). Topic #7797 Prior Authorization Request Form Completion Instructions for Prescribers for Drugs
ForwardHealth requires certain information to enable the programs to authorize and pay for medical services provided to eligible members.
Members of ForwardHealth are required to give providers full, correct, and truthful information for the submission of correct and complete claims for reimbursement. This information should include, but is not limited to, information concerning enrollment status, accurate name, address, and member identification number (Wis. Admin. Code § DHS 104.02[4]).
Under Wis. Stat. § 49.45(4), personally identifiable information about program applicants and members is confidential and is used for purposes directly related to ForwardHealth administration such as determining eligibility of the applicant, processing PA requests, or processing provider claims for reimbursement. The use of this form is mandatory to receive PA of certain procedures/services/items. Failure to supply the information requested by the form may result in denial of PA or payment for the service.
Providers should make duplicate copies of all paper documents mailed to ForwardHealth. Providers may submit PA requests, along with all applicable service-specific attachments, via the ForwardHealth Portal, by fax to ForwardHealth at 608-221-8616, or by mail to the following address:
ForwardHealth
Prior Authorization
Ste 88
313 Blettner Blvd
Madison WI 53784
The provision of services that are greater than or significantly different from those authorized may result in nonpayment of the billing claim(s).
SECTION I — PROVIDER INFORMATION
Element 1 — HealthCheck Other Services and Wisconsin Chronic Disease Program (WCDP)
Leave the box next to HealthCheck Other Services blank. Enter an "X" in the box next to WCDP if the services requested on the PA/RF are for a WCDP member.
Element 2 — Process Type
Enter process type 117 — Physician Services. The process type is a three-digit code used to identify a category of service requested. PA requests will be returned without adjudication if no process type is indicated.
Element 3 — Phone Number — Billing Provider
Enter the phone number, including the area code, of the office, clinic, facility, or place of business of the billing provider.
Element 4 — Name and Address — Billing Provider
Enter the name and complete address (street, city, state, and ZIP+4 code) of the billing provider. Providers are required to include both the ZIP code and four-digit extension for timely and accurate billing. The name listed in this element must correspond with the billing provider number listed in Element 5a.
Element 5a — Billing Provider Number
Enter the NPI of the billing provider. The NPI in this element must correspond with the provider name listed in Element 4.
Element 5b — Billing Provider Taxonomy Code
Enter the national 10-digit alphanumeric taxonomy code that corresponds to the NPI of the billing provider in Element 5a.
Element 6a — Name — Prescribing / Referring / Ordering Provider
Enter the prescribing/referring/ordering provider's name.
Element 6b — National Provider Identifier — Prescribing / Referring / Ordering Provider
Enter the prescribing/referring/ordering provider's 10-digit NPI.
SECTION II — MEMBER INFORMATION
Element 7 — Member ID Number
Enter the member ID. Do not enter any other numbers or letters. Use the ForwardHealth identification card or Wisconsin's EVS to obtain the correct number.
Element 8 — Date of Birth — Member
Enter the member's date of birth in mm/dd/ccyy format.
Element 9 — Name — Member
Enter the member's last name, followed by their first name and middle initial. Use the EVS to obtain the correct spelling of the member's name. If the name or spelling of the name on the ForwardHealth card and the EVS do not match, use the spelling from the EVS.
Element 10 — Address — Member
Enter the complete address of the member's place of residence, including the street, city, state, and ZIP code. If the member is a resident of a nursing home or other facility, include the name of the nursing home or facility.
SECTION III — DIAGNOSIS / TREATMENT INFORMATION
Element 11 — Diagnosis — Primary Code and Description
Enter the appropriate ICD diagnosis code and description with the highest level of specificity most relevant to the service/procedure requested. The ICD diagnosis code must correspond with the ICD description.
Element 12 — Diagnosis — Secondary Code and Description
Enter the appropriate secondary ICD diagnosis code and description with the highest level of specificity most relevant to the service/procedure requested, if applicable. The ICD diagnosis code must correspond with the ICD description.
Element 13 — Requested PA Start Date
Enter the requested start DOS in mm/dd/ccyy format.
Element 14 — Rendering Provider Number
Enter the prescriber's NPI, only if the NPI is different from the NPI of the billing provider listed in Element 5a.
Element 15 — Rendering Provider Taxonomy Code
Enter the national 10-digit alphanumeric taxonomy code that corresponds to the prescriber only if this code is different from the taxonomy code listed for the billing provider in Element 5b.
Element 16 — Service Code or National Drug Code (NDC) (not required)
Element 17 — Modifiers (not required)
Element 18 — POS
Enter the appropriate place of service code designating where the requested item would be provided/performed/dispensed.
Element 19 — Description of Service or Drug Name and Strength
Enter the drug name and dose for each item requested (for example, drug name, milligrams, capsules).
Element 20 — Quantity
Enter the appropriate quantity (for example, days' supply) requested for each item requested.
Element 21 — Charge (not required)
Element 22 — Total Charges (not required)
Element 23 — Signature — Requesting Provider
The original signature of the provider requesting this item must appear in this element.
Element 24 — Date Signed
Enter the month, day, and year the PA/RF was signed (in mm/dd/ccyy format). Topic #15937 Prior Authorization/Drug Attachment
When completing the PA/DGA form, prescribers should complete the most appropriate section as it pertains to the drug being requested. The specific sections are as follows:
- HealthCheck Other Services drug requests
- Diagnosis-restricted drug requests
- Drugs with specific PA criteria addressed in the ForwardHealth Online Handbook
- Other drug requests
Prescribers are required to fill out the appropriate section(s), then provide a handwritten signature and date on the PA/DGA form. Once completed, the prescriber should send the PA/DGA form to the pharmacy. The pharmacy should complete a PA/RF and submit it to ForwardHealth, along with the PA/DGA form from the prescriber.
Clinical Information for HealthCheck Other Services Drug Requests
If the prescriber writes a prescription for a drug that is not covered under the member's ForwardHealth benefit plan, the prescriber is required document the clinical rationale to support the medical necessity of the drug being requested as a HealthCheck Other Services PA request. Include documentation of the drug name, quantity, dose, duration of therapy, previous treatments, and detailed reasons why other covered drug treatments were discontinued or not used. Medical records and peer-reviewed medical literature should be provided as necessary to support the PA request. This information should be documented in Section IV (Clinical Information for HealthCheck Other Services Drug Requests) of the PA/DGA form.
When completing the PA/DGA form, prescribers should provide the diagnosis code and description, complete Section IV, and use Section VIII (Additional Information), if needed. Prescribers are reminded to provide a handwritten signature and date on the form before submitting it to the pharmacy provider where the prescription will be filled. The pharmacy provider is required to complete a PA/RF before submitting the PA/DGA form and supporting documentation to ForwardHealth. Prescribers should not submit the PA/DGA form to ForwardHealth.
Note: HealthCheck Other Services is limited to members under 21 years of age.
Clinical Information for Diagnosis-Restricted Drug Requests
If the prescriber writes a prescription with a diagnosis outside the ForwardHealth-allowed diagnoses for a drug, the prescriber is required to include peer-reviewed medical literature to support the proven efficacy and safety of the requested use of the drug. Documentation of previous treatments and detailed reasons why other covered drug treatments were discontinued or not used are required. Medical records should be provided as necessary to support the PA request. This information should be documented in Section V (Clinical Information for Diagnosis-Restricted Drug Requests) of the PA/DGA form.
When completing the PA/DGA form, prescribers should provide the diagnosis code and description, complete Section V, and use Section VIII (Additional Information), if needed. Prescribers are reminded to provide a handwritten signature and date on the form before submitting it to the pharmacy provider where the prescription will be filled. The pharmacy provider is required to complete a PA/RF before submitting the forms and supporting documentation to ForwardHealth. Prescribers should not submit PA/DGA forms to ForwardHealth.
Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook
If a prescriber writes a prescription for one of the following drugs, a PA request must be submitted on the PA/DGA form:
- Abilify MyCite
- Achondroplasia drugs
- Agamree
- Alhemo
- BBG drugs
- Bonsity
- Bylvay
- Casgevy
- Cayston
- Cholbam
- Crinone
- Cystic fibrosis drugs containing a CFTR potentiator
- Cytokine and CAM antagonist drugs used to treat alopecia areata, DIRA, ERA, GPP, NMOSD, NOMID, PMR, and SSc-ILD
- Dojolvi
- Duvyzat
- Emflaza
- Finasteride/tadalafil
- Glatopa
- Hemgenix
- Hetlioz LQ
- Hympavzi
- Immunomodulators, atopic dermatitis drugs
- Imcivree
- Javygtor
- Jaythari
- Jesduvroq
- Jynarque
- Kymbee
- Lenmeldy
- Lipotropics, ACL inhibitor drugs
- Lipotropics, apo-B inhibitor drugs
- Livmarli
- Long-term HAE prophylactic drugs
- Luxturna
- Lyfgenia
- Methamphetamine
- Misoprostol
- Nucala
- Opsynvi
- Opzelura (for vitiligo)
- Palynziq
- Pyquvi
- Qfitlia
- Redemplo
- Rezdiffra
- Sephience
- Skysona
- SMA drugs
- Strensiq
- Tasimelteon tablets
- Tavaborole
- Teriparatide
- Tezspire
- Tobi Podhaler
- Tolvaptan
- Tryngolza
- Vafseo
- Velsipity (for ulcerative colitis)
- Vigadrone
- Vigafyde
- Voyxact
- Vyjuvek
- Vykat XR
- Wegovy injection and Wegovy tablets
- Zelvysia
- Zeposia (for ulcerative colitis)
- Zokinvy
- Zynteglo
This information should be documented using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
When completing the PA/DGA form, prescribers should provide the diagnosis code and description, complete Section VI, and use Section VIII (Additional Information), if needed. Prescribers are reminded to provide a handwritten signature and date on the form before submitting it to the pharmacy provider where the prescription will be filled. The pharmacy provider is required to complete a PA/RF before submitting the forms and supporting documentation to ForwardHealth. Prescribers should not submit PA/DGA forms to ForwardHealth.
Clinical Information for Other Drug Requests
If the prescriber writes a prescription for a drug that requires the use of the PA/DGA form and has not been previously referenced in the above PA/DGA sections, the prescriber is required to document the clinical rationale to support the medical necessity of the drug being requested. Documentation of previous treatments and detailed reasons why other covered drug treatments were discontinued or not used are required. In addition, if the drug requested is a non-preferred PDL drug, prescribers are required to specifically address why other preferred PDL drugs cannot be used. Medical records and peer-reviewed medical literature should be provided as necessary to support the PA request. This information should be documented in Section VII (Clinical Information for Other Drug Requests) of the PA/DGA form.
If the pharmacy submitting the PA request is an out-of-state pharmacy providing a non-emergency service and the drug being requested does not have specific PA criteria established, additional documentation is required to be submitted. PA request documentation must demonstrate that the member has a medical condition for which the requested drug has FDA approval (medical records must be provided to verify the member's medical condition). Additionally, the drug must be prescribed in a dose and manner consistent with the FDA-approved product labeling.
When completing the PA/DGA form, prescribers should provide the diagnosis code and description, complete Section VII, and use Section VIII (Additional Information), if needed. Prescribers are reminded to provide a handwritten signature and date on the form before submitting it to the pharmacy provider where the prescription will be filled. The pharmacy provider is required to complete a PA/RF before submitting the forms and supporting documentation to ForwardHealth. Prescribers should not submit PA/DGA forms to ForwardHealth.
Prescribers and pharmacy providers are required to retain a completed copy of the PA request form(s).
Note: For assistance in identifying PDL drugs that require completion of Section VI and Section VII of the PA/DGA form, providers may refer to the Preferred Drug List Quick Reference. Topic #22580 Prior Authorization/Physician-Administered Drug Attachment
Individual sections on the PA/PAD form identify specific types of physician-administered drug PA requests that require clinical PA, and ForwardHealth has defined criteria for those sections. Prescribers must submit the PA/PAD form along with the PA/RF to request PA.
When completing the PA/PAD form, prescribers must complete the most appropriate section as it pertains to the physician-administered drug being requested. The specific sections are as follows:
- Clinical information for diagnosis-restricted physician-administered drug requests
- Clinical information for physician-administered drugs with specific PA criteria addressed in the ForwardHealth Online Handbook
- Clinical information for other physician-administered drug requests
- Additional information (Prescribers should complete this section if more space is needed on the PA/PAD form, or the prescriber is including additional information.)
Prescribers must fill out the appropriate section(s), then sign and date the PA/PAD form.
PA requests for physician-administered drugs must be completed, signed, and dated by the prescriber. PA requests for physician-administered drugs must be submitted using the PA/PAD form. Clinical documentation supporting the use of a physician-administered drug must be submitted with the PA request.
Prescribers are required to submit the completed PA/PAD form and a completed PA/RF to ForwardHealth.
PA requests for physician-administered drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Prescribers are reminded that they are required to complete, sign, and date each PA form when submitting the PA request. Prescribers are required to retain a completed copy of the PA request form(s).
Clinical Information for Diagnosis-Restricted Physician-Administered Drug Requests
If the prescriber orders a drug that is a physician-administered drug with a diagnosis outside the ForwardHealth-allowed diagnoses, the prescriber must submit peer-reviewed medical literature to support the proven efficacy and safety of the requested use of the physician-administered drug. Prescribers must also include documentation of previous treatments and detailed reasons why other covered drug treatments were discontinued or not used. Medical records should be provided as necessary to support the PA request.
This information should be documented in Section IV (Clinical Information for Diagnosis-Restricted Physician-Administered Drug Requests) of the PA/PAD form.
When completing the PA/PAD form, prescribers should provide the diagnosis code and description, complete Section IV, and use Section VII (Additional Information) if needed. Prescribers are reminded to sign and date the form before submitting the PA/PAD form and the PA/RF to ForwardHealth. Clinical documentation supporting the use of the physician-administered drug must be submitted with the PA request.
Clinical Information for Physician-Administered Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook
If the prescriber orders one of the following drugs, a PA request must be submitted on the PA/PAD form:
This information should be documented using Section V (Clinical Information for Physician-Administered Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/PAD form. Prescribers should refer to the appropriate topic in the Online Handbook for the drug-specific clinical PA criteria.
When completing the PA/PAD form, prescribers should provide the diagnosis code and description, complete Section V, and use Section VII (Additional Information) if needed. Prescribers are reminded to sign and date the form before submitting the PA/PAD with the PA/RF to ForwardHealth. Clinical documentation supporting the use of the physician-administered drug must be submitted with the PA request.
Clinical Information for Other Physician-Administered Drug Requests
If the prescriber orders a drug that is a physician-administered drug that requires the use of the PA/PAD form and has not been previously referenced in the above PA/PAD sections, the prescriber must document the clinical rationale to support the medical necessity of the physician-administered drug being requested. Documentation of previous treatments and detailed reasons why other covered drug treatments were discontinued or not used is required. Medical records and peer-reviewed medical literature should be provided as necessary to support the PA request.
PA documentation must demonstrate that the member has a medical condition for which the requested drug has FDA approval. (Medical records must be provided to verify the member's medical condition.)
Additionally, the drug must be prescribed in a dose and manner consistent with the FDA-approved product labeling.
This information should be documented in Section VI (Clinical Information for Other Physician-Administered Drug Requests) of the PA/PAD form.
When completing the PA/PAD form, prescribers should provide the diagnosis code and description, complete Section VI, and use Section VII (Additional Information) if needed. Prescribers are reminded to sign and date the form before submitting the PA/PAD form with the PA/RF to ForwardHealth. Clinical documentation supporting the use of the physician-administered drug must be submitted with the PA request.
Additional Information
Additional diagnostic and clinical information explaining the need for the drug requested may be included in Section VII of the PA/PAD form. If the space provided in the other sections is not sufficient, additional information may be included here. Topic #449 Supporting Clinical Documentation
Certain PA requests may require additional supporting clinical documentation to justify the medical necessity for a service(s). Supporting documentation may include, but is not limited to, X-rays, photographs, a provider's prescription, clinical reports, and other materials related to the member's condition.
All supporting documentation submitted with a PA request must be clearly labeled and identified with the member's name and member identification number. Securely packaged X-rays and dental models will be returned to providers.
Photographs submitted to ForwardHealth as additional supporting clinical documentation for PA requests will not be returned to providers and will be disposed of securely. Topic #450 Clerical Review
The first step of the PA request review process is the clerical review. This is an administrative process to verify the provider, member, diagnosis, and treatment information indicated on the PA/RF and PA/DRF forms. Examples of information verified during the clerical review include:
- Valid provider and member information.
- All required elements are complete.
- Forms, attachments, and additional supporting clinical documentation are signed and dated.
- A current provider's prescription for the service is attached, if required.
Drug-related PA requests with clerical errors and omissions will be returned to pharmacy providers due to inaccurate or incomplete information. Any inaccurate or incomplete non-drug PA requests will be recorded as Incomplete ? PA Denied. Since having to return a PA request for corrections or additional information can delay approval and delivery of services to a member, providers should ensure that all clerical information is correctly and completely entered on the PA/RF or PA/DRF. Topic #451 Clinical Review
Upon verifying the completeness and accuracy of clerical items, a PA request is reviewed to evaluate whether or not each service being requested meets Wisconsin Medicaid's definition of "medically necessary," as well as other criteria.
The PA attachment allows a provider to document the clinical information used to determine whether the standards of medical necessity are met for the requested service. Wisconsin Medicaid considers certain factors when determining whether to approve or deny a PA request pursuant to Wis. Admin. Code § DHS 107.02(3)(e).
It is crucial that a provider include adequate information on the PA attachment so that the ForwardHealth consultant performing the clinical review can determine that the service(s) being requested meets all the elements of Wisconsin Medicaid's definition of "medically necessary," including elements that are not strictly medical in nature. Documentation must provide the justification for the service requested specific to the member's current condition and needs. Pursuant to Wis. Admin. Code § DHS 101.03(96m), "medically necessary" is a service under Wis. Admin. Code ch. DHS 107 that meets certain criteria.
Determination of Medical Necessity
The definition of "medically necessary" is a legal definition identifying the standards that must be met for approval of the service. The definition imposes parameters and restrictions that are both medical and nonmedical.
The determination of medical necessity is based on the documentation submitted by the provider. For this reason, it is essential that documentation is submitted completely and accurately and that it provides the justification for the service requested, specific to the member's current condition and needs. To be approved, a PA request must meet all of the standards of medical necessity including those that are not strictly medical in nature.
To determine if a requested service is medically necessary, ForwardHealth consultants obtain direction and/or guidance from multiple resources including:
- Federal and state statutes
- Wisconsin Administrative Code
- PA guidelines set forth by Wisconsin DHS
- Standards of practice
- Professional knowledge
- Scientific literature
Topic #4617 An Overview
ForwardHealth will make a decision regarding 24-hour PA requests, such as PA requests for brand medically necessary drugs, within 24 hours with the receipt of all the necessary information and telephone or fax the decision to the provider who submitted the PA request. Topic #424 Approved Requests
PA requests are approved for varying periods of time based on the clinical justification submitted. The provider receives a copy of a PA decision notice when a PA request for a service is approved. Providers may then begin providing the approved service on the grant date given.
An approved request means that the requested service, not necessarily the code, was approved. For example, a similar procedure code may be substituted for the originally requested procedure code. Providers are encouraged to review approved PA requests to confirm the services authorized and confirm the assigned grant and expiration dates.
Listing Procedure Codes Approved as a Group on the Decision Notice Letter
In certain circumstances, ForwardHealth will approve a PA request for a group
of procedure codes with a total quantity approved for the entire group. When
this occurs, the quantity approved for the entire group of codes will be
indicated with the first procedure code. All of the other approved procedure
codes within the group will indicate a quantity of zero.
Providers may submit claims for any combination of the procedure codes in the
group up to the approved quantity. Topic #4724 Communicating Prior Authorization Decisions
ForwardHealth will make a decision regarding a provider's PA request within 20 working days from the receipt of all the necessary information. After processing the PA request, ForwardHealth will send the provider a decision notice letter. Providers will receive a decision notice letter for PA requests that were approved, approved with modifications, or denied. The decision notice letter will clearly indicate what is approved or what correction or additional information ForwardHealth needs to continue adjudicating the PA request.
Providers submitting PA requests via the ForwardHealth Portal will receive a decision notice letter via the Portal. Topic #5037 Decision Notice Letters and Returned Provider Review Letters on the Portal
Providers can view PA decision notices and provider review letters via the secure area of the ForwardHealth Portal. PA decision notices and provider review letters can be viewed when the PA is selected on the Portal.
Note: The PA decision notice or the provider review letter will not be available until the day after the PA request is processed by ForwardHealth. Topic #425 Denied Requests
When a PA request is denied, both the provider and the member are notified. The provider receives a PA decision notice, including the reason for PA denial. The member receives a Notice of Appeal Rights letter that includes a brief statement of the reason PA was denied and information about their right to a fair hearing. Only the member, or authorized person acting on behalf of the member, can appeal the denial.
Providers may call Provider Services for clarification of why a PA request was denied.
Providers are required to discuss a denied PA request with the member and are encouraged to help the member understand the reason the PA request was denied.
Providers have three options when a PA request is denied:
- Choose not to provide the service.
- Submit a new PA request. Providers are required to submit a copy of the original denied PA request and additional supporting clinical documentation and medical justification along with a new PA/RF or PA/DRF.
- Provide the service as a noncovered service.
The member may choose to receive a service as a noncovered service:
- When the member does not appeal the decision of the denied PA request.
- When the member appeals the decision but the decision is upheld.

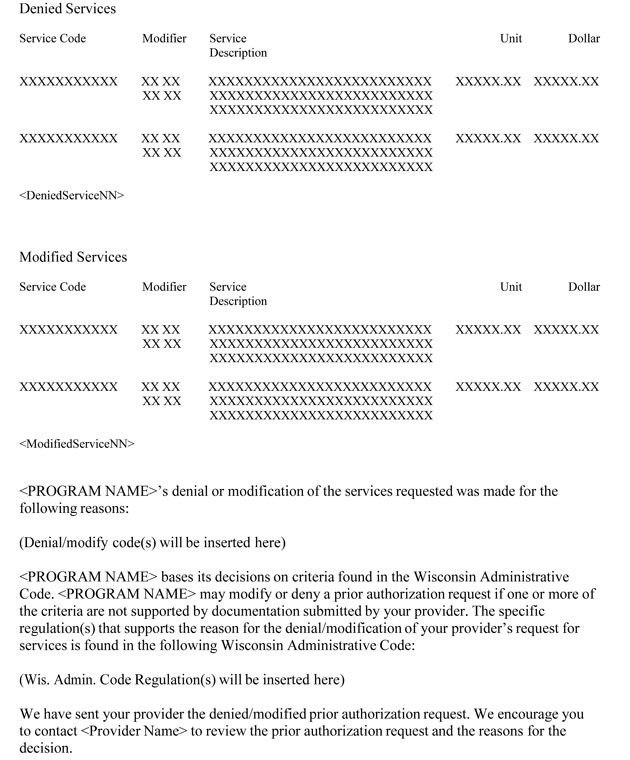

 Topic #12837 Pharmacy Providers
If a PA is denied during adjudication, providers may submit a new request for the service using the P4 transaction; however, they are required to submit the original denied PA request, additional supporting clinical documentation, and medical justification via the Portal, fax, or mail following the submission guidelines. Topic #426 Modified Requests
Modification is a change in the services originally requested on a PA request. Modifications could include, but are not limited to, either of the following:
- The authorization of a procedure code different than the one originally requested.
- A change in the frequency or intensity of the service requested.
When a PA request is modified, both the provider and the member are notified. The provider will be sent a decision notice letter. The decision notice letter will clearly indicate what is approved or what correction or additional information is needed to continue adjudicating the PA request. The member receives a Notice of Appeal Rights letter that includes a brief statement of the reason PA was modified and information on their right to a fair hearing. Only the member, or authorized person acting on behalf of the member, can appeal the modification.
Providers are required to discuss with the member the reasons a PA request was modified.
Providers have the following options when a PA request is approved with modification:
- Provide the service as authorized.
- Submit a request to amend the modified PA request. Additional supporting clinical documentation and medical justification must be included.
- Not provide the service.
- Provide the service as originally requested as a noncovered service.
If the member does not appeal the decision to modify the PA request or appeals the decision but the decision is upheld and the member chooses to receive the originally requested service anyway, the member may choose to receive the service(s) as a noncovered service.
Providers may call Provider Services for clarification of why a PA request was modified.
Topic #1324 Response Time
For most drugs, ForwardHealth responds by fax or telephone to the provider's paper PA request within 24 hours of the receipt of the request. The response consists of an acknowledgment that the PA request was received by ForwardHealth.
Weekend and Holiday Processing
Paper PA requests received Monday through Friday (except holidays) are handled as follows:
- If the request is received before 1 p.m. Central time, ForwardHealth makes an attempt to notify the provider by telephone or fax within 24 hours.
- If the request is received after 1 p.m. Central time, ForwardHealth makes an attempt to notify the provider by telephone or fax on the next regular business day.
Exceptions to the 24-Hour Response
ForwardHealth responds within 24 hours except when:
- The PA request contains insufficient, incorrect, or illegible information so that ForwardHealth cannot identify the requesting provider or determine that the requested service requires a 24-hour response.
- The PA request does not have the provider's telephone or fax number.
ForwardHealth makes three attempts to contact the provider by telephone or fax within 24 hours of receiving the PA request. Topic #4737 Returned Provider Review Letter Response Time
Thirty Days to Respond to the Returned Provider Review Letter
ForwardHealth must receive the provider's response within 30 calendar days of the date on the returned provider review letter, whether the letter was sent to
the provider by mail or through the ForwardHealth Portal. If the provider's response is received within 30 calendar days, ForwardHealth still considers the original
receipt date on the PA request when authorizing a grant date for the PA.
If a provider needs more than 30 days to submit the requested information, providers can request an extension by submitting a letter that explains why more time is needed to gather and submit the additional information requested. The letter seeking an extension must be submitted within the initial 30 calendar days of receiving the returned provider review letter.
Instructions for how to submit the letter can be found in the ForwardHealth Provider Portal Prior Authorization User Guide. If a provider wants to submit the letter via mail or fax, the provider must ensure it is received within the 30 days. While mailed or faxed letters are accepted, providers are encouraged to submit the letter via electronic upload.
Providers will be notified in a manner similar to how they submitted their letter, and the new deadline will be included in that notification. Providers who mail their submissions will receive a notification in the mail. Providers who electronically upload their submission will receive a notification in the Portal, etc.
If ForwardHealth does not receive the provider's response within 30 calendar days of the date the returned provider review letter was sent, the PA status becomes inactive and the provider is required to submit a new PA request. This results in a later grant date if the PA request is approved. Providers will
not be notified when their PA request status changes to inactive, but this information will be available on the Portal and through WiCall.
If ForwardHealth receives additional information from the provider after the 30-day deadline has passed, a letter will be sent to the provider stating that the PA request is inactive and the provider is required to submit a new PA request. Topic #427 Returned Requests
A PA request may be returned to the provider when forms are incomplete, inaccurate, or additional clinical information or corrections are needed. When this occurs, the provider will be sent a provider review letter.
Returned Provider Review Letter
The returned provider review letter will indicate the PA number assigned to
the request and will specify corrections or additional information needed on the
PA request. Providers are required to make the corrections or supply the
requested information in the space provided on the letter or attach additional
information to the letter before mailing the letter to ForwardHealth. Providers
can also correct PAs that have been placed in returned provider review status in
the ForwardHealth Portal.
If providers require more than 30 days submit corrections or required additional information, they can request an extension by submitting a letter that explains why more time is needed. The letter requesting an extension must be submitted within the initial 30 calendar days of receiving the returned provider review letter.
Instructions for how to submit the letter can be found in the ForwardHealth Provider Portal Prior Authorization User Guide. If a provider wants to submit the letter via mail or fax, the provider must ensure it is received within the 30 days. While mailed or faxed letters are accepted, providers are encouraged to submit the letter via electronic upload.
Providers will be notified in a manner similar to how they submitted their letter, and the new deadline will be included in that notification. Providers who mail their submissions will receive a notification in the mail. Providers who electronically upload their submission will receive a notification in the Portal, etc.
The provider's paper documents submitted with the PA request will not
be returned to the provider when corrections or additional information are
needed; however, X-rays and dental models will be returned once the PA is finalized.
Photographs submitted to ForwardHealth as additional supporting clinical documentation for PA requests will not be returned to providers and will be disposed of securely.
Therefore, providers are required to make a copy of their PA requests
(including attachments and any supplemental information) before mailing the
requests to ForwardHealth. The provider is required to have a copy on file for
reference purposes if more information is required about the PA
request.
Note: When changing or correcting the PA request, providers are reminded to
revise or update the documentation retained in their records. Topic #4738 Amendment Decisions
ForwardHealth will make a decision regarding a provider's amendment request
within 20 working days from the receipt of all the necessary information. The method ForwardHealth will use to communicate decisions regarding PA amendment requests will depend on how the PA request was originally submitted (not how the amendment request was submitted) and whether the provider has a ForwardHealth Portal account. If the PA request was originally submitted via the Portal, the decision notice letter will be sent to the provider via the Portal. Topic #431 Amendments
Providers are required to use the Prior Authorization Amendment Request form to amend an approved or modified PA request.
ForwardHealth does not accept a paper amendment request submitted on anything
other than the Prior Authorization Amendment Request form. The Prior Authorization Amendment Request form may be submitted through the Portal, by mail or by fax. If ForwardHealth receives a PA amendment on a previous version of the Prior Authorization Amendment Request form, a letter will be sent to the provider stating that the provider is required to submit a new PA amendment request using the proper form.
Providers may request an amendment to an approved or modified PA request to:
- Temporarily modify a member's frequency of a service when there is a short-term change in their medical condition.
- Change the rendering provider information when the billing provider remains the same.
- Change the member's ForwardHealth identification number.
- Add or change a procedure code.
Note: ForwardHealth recommends that, under most circumstances, providers should enddate the current PA request and submit a new one if there is a significant, long-term change in services required. Topic #432 Appeals
If a PA request is denied or modified by ForwardHealth, only a member, or authorized person acting on behalf of the member, may file an appeal with the DHA. Decisions that may be appealed include the following:
- Denial or modification of a PA request
- Denial of a retroactive authorization for a service
The member is required to file an appeal within 45 days of the date of the Notice of Appeal Rights.
To file an appeal, members may complete and submit a Request for Fair Hearing form.
Though providers cannot file an appeal, they are encouraged to remain in contact with the member during the appeal process. Providers may offer the member information necessary to file an appeal and help present their case during a fair hearing.
Fair Hearing Upholds ForwardHealth's Decision
If the hearing decision upholds the decision to deny or modify a PA request, the DHA notifies the member and ForwardHealth in writing. The member may choose to receive the service (or in the case of a modified PA request, the originally requested service) as a noncovered service, not receive the service at all, or appeal the decision.
Fair Hearing Overturns ForwardHealth's Decision
If the hearing decision overturns the decision to deny or modify the PA request, the DHA notifies ForwardHealth and the member. The letter includes instructions for the provider and for ForwardHealth.
If the DHA letter instructs the provider to submit a claim for the service, the provider should submit the following to ForwardHealth after the service has been performed:
- A paper claim with "HEARING DECISION ATTACHED" written in red ink at the top of the claim
- A copy of the hearing decision
- A copy of the denied PA request
Providers are required to submit claims with hearing decisions to the following address:
ForwardHealth
Specialized Research
Ste 50
313 Blettner Blvd
Madison WI 53784
Claims with hearing decisions sent to any other address may not be processed appropriately.
If the DHA letter instructs the provider to submit a new PA request, the provider is required to submit the new PA request along with a copy of the hearing decision to the PA Unit at the following address:
ForwardHealth
Prior Authorization
Ste 88
313 Blettner Blvd
Madison WI 53784
ForwardHealth will then approve the PA request with the revised process date. The provider may then submit a claim following the usual claims submission procedures after providing the service(s).
Financial Responsibility
If the member asks to receive the service before the hearing decision is made, the provider is required to notify the member before rendering the service that the member will be responsible for payment if the decision to deny or modify the PA request is upheld.
If the member accepts responsibility for payment of the service before the hearing decision is made, and if the appeal decision upholds the decision to deny or modify the PA request, the provider may collect payment from the member if certain conditions are met.
If the member accepts responsibility for payment of the service before the hearing decision is made, and if the appeal decision overturns the decision to deny or modify a PA request, the provider may submit a claim to ForwardHealth. If the provider collects payment from the member for the service before the appeal decision is overturned, the provider is required to refund the member for the entire amount of payment received from the member after the provider receives Medicaid's reimbursement.
Wisconsin Medicaid does not directly reimburse members.
Topic #1106 Enddating
Providers are required to use the Prior Authorization Amendment Request to end date most PA requests. ForwardHealth does not accept requests to end date a PA request for any service, except drugs, on anything other than the Prior Authorization Amendment Request. PA for drugs may be end-dated by using STAT-PA, in addition to submitting a Prior Authorization Amendment Request.
Providers may submit a Prior Authorization Amendment Request on the ForwardHealth Portal, or by fax or mail.
If a request to end date a PA is not submitted on the Prior Authorization Amendment Request, a letter will be sent to the provider stating that the provider is required to submit the request using the proper forms.
Examples of when a PA request should be end-dated include the following:
- A member chooses to discontinue receiving prior authorized services.
- A provider chooses to discontinue delivering prior authorized services.
Examples of when a PA request should be end-dated and a new PA request should be submitted include the following:
- There is an interruption in a member's continual care services.
- There is a change in the member's condition that warrants a long-term change in services required.
- The service(s) is no longer medically necessary.
Topic #5039 Searching for Previously Submitted Prior Authorization Requests on the Portal
Providers will be able to search for all previously submitted PA requests, regardless of how the PA was initially submitted. If the provider knows the PA number, they can enter the number to retrieve the PA information. If the provider does not know the PA number, they can search for a PA by entering information in one or more of the following fields:
- Member identification number
- Requested start date
- Prior authorization status
- Amendment status
If the provider does not search by any of the information above, providers will retrieve all their PA requests submitted to ForwardHealth. Topic #454 Services Not Performed Before Expiration Date
Generally, a new PA request with a new requested start date must be submitted to ForwardHealth if the amount or quantity of prior authorized services is not used by the expiration date of the PA request and the service is still medically necessary. Topic #443 Loss of Enrollment During Treatment
Some covered services consist of sequential treatment steps, meaning more than one office visit or service is required to complete treatment.
In most cases, if a member loses enrollment midway through treatment, or at any time between the grant and end dates, Wisconsin Medicaid will not reimburse services (including prior authorized services) provided during an enrollment lapse. Providers should not assume Wisconsin Medicaid covers completion of services after the member's enrollment has been terminated.
To avoid potential reimbursement problems when a member loses enrollment during treatment, providers should follow these procedures:
- Ask to see the member's ForwardHealth identification card to verify the member's enrollment or consult Wisconsin's EVS before the services are provided at each visit.
- When the PA request is approved, verify that the member is still enrolled and eligible to receive the service before providing it. An approved PA request does not guarantee payment and is subject to the enrollment of the member.
Members are financially responsible for any services received after their enrollment has ended. If the member wishes to continue treatment, it is a decision between the provider and the member whether the service should be given and how payment will be made for the service.
To avoid misunderstandings, providers should remind members that they are financially responsible for any continued care after their enrollment ends. Topic #444 Retroactive Disenrollment From State-Contracted MCOs
Occasionally, a service requiring fee-for-service PA is performed during a member's enrollment period in a state-contracted MCO. After the service is provided, and it is determined that the member should be retroactively disenrolled from the MCO, the member's enrollment is changed to fee-for-service for the DOS. The member is continuously eligible for BadgerCare Plus or Wisconsin Medicaid but has moved from MCO enrollment to fee-for-service status.
In this situation, the state-contracted MCO would deny the claim because the member was not enrolled on the DOS. Fee-for-service would also deny the claim because PA was not obtained.
Providers may take the following steps to obtain reimbursement in this situation:
- For a service requiring PA for fee-for-service members, the provider is required to submit a retroactive PA request. For a PA request submitted on paper, indicate "RETROACTIVE FEE-FOR-SERVICE" along with a written description of the service requested/provided under "Description of Service." Also indicate the actual date(s) the service(s) was provided. For a PA request submitted via the ForwardHealth Portal, indicate "RETROACTIVE FEE-FOR-SERVICE" along with a description of the service requested/provided under the "Service Code Description" field or include additional supporting documentation. Also indicate the actual date(s) the service(s) was provided.
- If the PA request is approved, the provider is required to follow fee-for-service policies and procedures for claims submission.
- If the PA request is denied, Wisconsin Medicaid will not reimburse the provider for the services. A PA request would be denied for reasons such as lack of medical necessity. A PA request would not be denied due to the retroactive fee-for-service status of the member.
Topic #445 Retroactive Enrollment
If a service(s) that requires PA was performed during a member's retroactive enrollment period, the provider is required to submit a PA request and receive approval from ForwardHealth before submitting a claim. For a PA request submitted on paper, indicate the words "RETROACTIVE ENROLLMENT" at the top of the PA request along with a written description explaining that the service was provided at a time when the member was retroactively enrolled under "Description of Service." Also include the actual date(s) the service(s) was provided. For a PA request submitted via the ForwardHealth Portal, indicate the words "RETROACTIVE ENROLLMENT" along with a description explaining that the service was provided at a time when the member was retroactively eligible under the "Service Code Description" field or include additional supporting documentation. Also include the actual date(s) the service(s) was provided.
If the member was retroactively enrolled, and the PA request is approved, the service(s) may be reimbursable, and the earliest effective date of the PA request will be the date the member receives retroactive enrollment. If the PA request is denied, the provider will not be reimbursed for the service(s). Members have the right to appeal the decision to deny a PA request.
If a member requests a service that requires PA before his or her retroactive enrollment is determined, the provider should explain to the member that he or she may be liable for the full cost of the service if retroactive enrollment is not granted and the PA request is not approved. This should be documented in the member's record. Topic #429 Emergency Services
In emergency situations, the PA requirement may be waived for services that normally require PA. Emergency services are defined in Wis. Admin. Code DHS 101.03(52) as "those services which are necessary to prevent the death or serious impairment of the health of the individual."
Reimbursement is not guaranteed for services that normally require PA that are provided in emergency situations. As with all covered services, emergency services must meet all program requirements, including medical necessity, to be reimbursed by Wisconsin Medicaid. For example, reimbursement is contingent on, but not limited to, eligibility of the member, the circumstances of the emergency, and the medical necessity of the services provided.
Wisconsin Medicaid will not reimburse providers for noncovered services provided in any situation, including emergency situations. Topic #430 Urgent Situations
If a PA request is required for an urgent situation, providers are required to submit the PA request in the ForwardHealth Portal.
ForwardHealth defines a PA request for a medically urgent situation as any request for medical care or treatment with respect to which the application of the time periods for making non-urgent care determinations could have the following impact:
- Seriously jeopardize the life or health of the member or the member's ability to regain maximum function, based on a prudent layperson's judgment.
- In the opinion of a practitioner with knowledge of the member's medical condition, would subject the member to severe pain that cannot be adequately managed without the care or treatment that is the subject of the request.
Topic #4402 An Overview
The PA review process includes both a clerical review and a clinical review. The PA request will have one of the statuses detailed in the following table.
| Prior Authorization Status |
Description |
| Approved |
The PA request was approved. |
| Approved with Modifications |
The PA request was approved with modifications to what was requested. |
| Denied |
The PA request was denied. |
| Inactive—Void |
The PA request is either:
- Submitted but not required.
- A provider requests to rescind the PA request.
- Submitted in error.
- The request was sent to the incorrect payor. For example, the member is in an HMO that covers this service.
|
| Incomplete—PA Denied |
The PA request was denied because the request form was inaccurate or incomplete and ForwardHealth requires a complete and accurate PA request to determine if an item or service is covered. |
| Pending—Dental Follow-up |
The PA request is being reviewed by a Fiscal Agent dental specialist. |
| Pending—Fiscal Agent Review |
The PA request is being reviewed by the Fiscal Agent. |
| Pending—State Review |
The PA request is being reviewed by the State. |
| Suspend—Provider Sending Information |
The PA request was submitted via the ForwardHealth Portal, and the provider indicated they will be sending additional supporting information on paper. |
| For Pharmacy Providers Only |
| Inactive |
The PA request is inactive due to no response within 30 days to the returned provider review letter and cannot be used for PA or claims processing. |
| Returned—Provider Review |
The PA request was returned to the provider for correction or for additional information. |
Topic #434 Communication With Members
ForwardHealth recommends that providers inform members that PA is required for certain specified services before delivery of the services. Providers should also explain that, if required to obtain PA, they will be submitting member records and information to ForwardHealth on the member's behalf. Providers are required to keep members informed of the PA request status throughout the entire PA process.
Member Questions
A member may call Member Services to find out whether or not a PA request has been submitted and, if so, when it was received by ForwardHealth. The member will be advised to contact the provider if more information is needed about the status of an individual PA request. Topic #435 Definition
PA is the electronic or written authorization issued by ForwardHealth to a provider prior to the provision of a service. In most cases, providers are required to obtain PA before providing services that require PA. When granted, a PA request is approved for a specific period of time and specifies the type and quantity of service allowed. Topic #5098 Designating an Address for Prior Authorization Correspondence
Correspondence related to PA will be sent to the practice location address on file with ForwardHealth unless the provider designates a separate address for receipt of PA correspondence. This policy applies to all PA correspondence, including decision notice letters and returned supplemental documentation such as X-rays and dental models.
Photographs submitted to ForwardHealth as additional supporting clinical documentation for PA requests will not be returned to providers and will be disposed of securely.
Providers may designate a separate address for PA correspondence using the demographic maintenance tool. Topic #2334 Drugs
Wisconsin Medicaid has the authority to require PA for certain drug products under Wis. Admin. Code § DHS 107.10(2) and the federal Omnibus Budget Reconciliation Acts of 1990 and 1993 (OBRA '90 and '93).
Most drugs do not require PA. For drugs that require PA, pharmacy providers may submit PA requests through the STAT-PA system (when applicable), on the ForwardHealth Portal, using an NCPDP transaction, or on paper by fax or by mail.
Drugs That Require Prior Authorization
Most drug PAs are not pharmacy provider-specific. For most approved drug PA requests, the member may go to any Medicaid-enrolled pharmacy provider to obtain the prior authorized drug. For these drug PAs, the PA does not need to be enddated when the member changes pharmacies.
Non-preferred hepatitis C agents included in the hepatitis C agents drug class on the PDL are approved as pharmacy provider-specific.
Prescriber Responsibilities for Drugs That Require Prior Authorization
Prescribers must complete, sign, and date the appropriate PA form for drugs that require PA.
Prescribers must include all the required clinical information about the member's medical history on the PA form. The prescriber's signature on the PA form attests that the information provided is complete and accurate. When completing the PA form, prescribers are required to provide a handwritten signature on the form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Prescribers must retain a completed, signed, and dated copy of the PA form and any supporting documentation.
Per ForwardHealth policy, member use of manufacturer-provided samples or manufacturer patient assistance programs are not considered as previous medication history for any medication PA review. Members who are started on a medication outside ForwardHealth are not exempt from meeting PA criteria (unless specifically noted).
Pharmacy Provider Responsibilities for Drugs That Require Prior Authorization
Pharmacy providers are required to submit PA requests using the completed, signed, and dated PA form from the prescriber and a completed PA/RF.
Pharmacy providers may submit PA requests using the STAT-PA system (when applicable), on the Portal, by fax, or by mail.
Pharmacy providers must retain a completed, signed, and dated copy of the PA form and any supporting documentation received from the prescriber. Pharmacy providers may not reuse PA forms from previously approved PA requests for subsequent PA request submissions.
Note: If additional information needs to be addressed and can be provided by the pharmacy provider (for example, medication refill history and compliance), the pharmacy provider should add the information to the Prior Authorization Fax Cover Sheet or to the Additional Information section available on most PA forms. The pharmacy provider must sign and date the entry to clearly identify the information source.
SeniorCare
Regardless of the member's level of participation,
SeniorCare requires PA for certain drugs so that the pharmacy provider may receive reimbursement. Topic #4383 Prior Authorization Numbers
Upon receipt of the PA/RF, ForwardHealth will assign a PA number to each PA request.
The PA number consists of 10 digits, containing valuable information about the PA (for example, the date the PA request was received by ForwardHealth, the medium used to submit the PA request).
Each PA request is assigned a unique PA number. This number identifies valuable information about the PA. The following table provides detailed information about interpreting the PA number.
| Type of Number and Description |
Applicable Numbers and Description |
| Media—One digit indicates media type. |
Digits are identified as follows:
1 = paper; 2 = fax; 3 = STAT-PA; 4 = STAT-PA; 5 = Portal; 6 = Portal; 7 = NCPDP transaction or 278 transaction; 9 = eviCore healthcare |
| Year—Two digits indicate the year ForwardHealth received the PA request. |
For example, the year 2008 would appear as 08. |
| Julian date—Three digits indicate the day of the year, by Julian date, that ForwardHealth received the PA request. |
For example, February 3 would appear as 034. |
| Sequence number—Four digits indicate the sequence number. |
The sequence number is used internally by ForwardHealth. |
Topic #8578 Prior Authorization and Day Supply
Drug PAs are approved based on day supply. If a claim exceeds the day supply remaining on a PA, the claim will be denied. For example, a PA was granted for a 180-day supply and 160-days supply of the drug has already been dispensed. If a claim for 30-day supply is submitted it will be denied. However, a claim for 20-day supply will be reimbursed if all other billing requirements are met. Topic #436 Reasons for Prior Authorization
Only about 4% of all services covered by Wisconsin Medicaid require PA. PA requirements vary for different types of services. Refer to ForwardHealth publications and Wis. Admin. Code ch. DHS 107 for information regarding services that require PA. According to Wis. Admin. Code § DHS 107.02(3)(b), PA is designed to:
- Safeguard against unnecessary or inappropriate care and services.
- Safeguard against excess payments.
- Assess the quality and timeliness of services.
- Promote the most effective and appropriate use of available services and facilities.
- Determine if less expensive alternative care, services, or supplies are permissible.
- Curtail misutilization practices of providers and members.
PA requests are processed based on criteria established by Wisconsin DHS.
Providers should not request PA for services that do not require PA simply to determine coverage or establish a reimbursement rate for a manually priced procedure code. Also, new technologies or procedures do not necessarily require PA. Providers having difficulties determining whether or not a service requires PA may call Provider Services. Topic #437 Referrals to Out-of-State Providers
PA may be granted to out-of-state providers when nonemergency services are necessary to help a member attain or regain their health and ability to function independently. The PA request may be approved only when the services are not reasonably accessible to the member in Wisconsin.
Out-of-state providers are required to meet ForwardHealth's guidelines for PA approval. This includes sending PA requests, required attachments, and supporting documentation to ForwardHealth before the services are provided.
Note: Emergency services provided out-of-state do not require PA; however, claims for such services must include appropriate documentation (for example, anesthesia report, medical record) to be considered for reimbursement. Providers are required to submit claims with supporting documentation on paper.
When a Wisconsin Medicaid provider refers a member to an out-of-state provider, the referring provider should instruct the out-of-state provider to go to the Provider Enrollment Information home page on the ForwardHealth Portal to complete a Medicaid Out-of-State Provider Enrollment Application.
All out-of-state nursing homes, regardless of location, are required to obtain PA for all services. All other out-of-state nonborder-status providers are required to obtain PA for all nonemergency services except for home dialysis supplies and equipment. Topic #438 Reimbursement Not Guaranteed
Wisconsin Medicaid may decline to reimburse a provider for a service that has been prior authorized if one or more of these program requirements are not met:
- The service authorized on the approved PA request is the service provided.
- The service is provided within the grant and expiration dates on the approved PA request.
- The member is eligible for the service on the date the service is provided.
- The provider is enrolled in Wisconsin Medicaid on the date the service is provided.
- The service is billed according to service-specific claim instructions.
- The provider meets other program requirements.
Providers may not collect payment from a member for a service requiring PA under any of these circumstances:
- The provider failed to seek PA before the service was provided.
- The service was provided before the PA grant date or after the PA expiration date.
- The provider obtained PA but failed to meet other program requirements.
- The service was provided before a decision was made, the member did not accept responsibility for the payment of the service before the service was provided, and the PA was denied.
There are certain situations when a provider may collect payment for services in which PA was denied.
Other Health Insurance Sources
Providers are encouraged, but not required, to request PA from ForwardHealth for covered services that require PA when members have other health insurance coverage. This is to allow payment by Wisconsin Medicaid for the services provided in the event that the other health insurance source denies or recoups payment for the service. If a service is provided before PA is obtained, ForwardHealth will not consider backdating a PA request solely to enable the provider to be reimbursed. Topic #1268 Sources of Information
Providers should verify that they have the most current sources of information regarding PA. It is critical that providers and staff have access to these documents:
- Wisconsin Administrative Code: Chapters DHS 101–109 are the rules regarding Medicaid administration.
- Wisconsin Statutes: Sections 49.43–49.99 provide the legal framework for Wisconsin Medicaid.
- ForwardHealth Portal: The Portal gives the latest policy information for all providers, including information about Medicaid managed care enrollees.
Topic #812 Status Inquiries
Providers may inquire about the status of a PA request through one of the following methods:
Providers should have the 10-digit PA number available when making inquiries. Topic #13697 Third-Party Websites
The ForwardHealth Portal allows providers access to all policy and billing information for BadgerCare Plus, Medicaid, SeniorCare, HDAP, and WCDP in one centralized place. PA request forms and information about ForwardHealth's policies should be obtained from the Portal or Provider Services. Third-party websites are not affiliated with or endorsed by ForwardHealth. Topic #439 Backdating for Initial and Renewal Requests
Initial Requests
An initial PA request is the original approved PA that starts specific medically necessary services for a member.
ForwardHealth may allow a PA request to be backdated if it is received within 14 calendar days of the requested start date. ForwardHealth will modify or deny a PA request if it is received more than 14 calendar days after the requested start date and does not meet the extraordinary circumstances criteria.
Renewal Requests
A renewal request is a new PA request to continue medically necessary services beyond the initial PA request's end date.
Backdating is not allowed when submitting an amendment request for continuous treatment. All PA amendment requests to extend treatment must be received by ForwardHealth prior to the expiration date of the current PA request.
Backdating may be allowed for all benefits that utilize a PA request (PA/RF) to continue treatment if it is received within 14 calendar days of the requested start date. ForwardHealth will modify or deny a PA request if it is received more than 14 calendar days after the requested start date and does not meet the extraordinary circumstances criteria.
Extraordinary Circumstances Criteria
ForwardHealth may approve a request for backdating if all of these conditions are met:
- The provider specifically requests backdating in writing on the PA request.
- The request includes clinical justification for beginning the service before PA was granted.
- The request includes the reason why the request was submitted more than 14 days after the requested start date.
Examples of extraordinary circumstances include:
- A court order or hearing decision requiring Wisconsin Medicaid coverage is attached to the PA request.
- The member is retroactively enrolled. (Indicate in Element 21 of the PA/RF that the service was provided during a period of member retroactive enrollment. In Element 15, indicate the actual date the service was provided.)
- The provider is on a correction plan.
If the PA request is modified or denied and a service has already been rendered, the provider cannot require payment from the member. Topic #440 Expiration Date
The expiration (end) date of an approved or modified PA request is the date through which services are prior authorized. PA requests are granted for varying periods of time. Expiration dates may vary and do not automatically expire at the end of the month or calendar year. In addition, providers may request a specific expiration date. Providers should carefully review all approved and modified PA requests and make note of the expiration dates. Topic #441 Grant Date
The grant (start) date of an approved or modified PA request is the first date in which services are prior authorized and will be reimbursed under this PA number. On a PA request, providers may request a specific date that they intend services to begin. If no grant date is requested or the grant date is illegible, the grant date will typically be the date the PA request was reviewed by ForwardHealth. Topic #12597 278 Health Care Services Review — Request for Review and Response Transaction
Providers may request PA electronically using the 278 transaction, the standard electronic format for health care service PA requests.
Compliance Testing
Trading partners may conduct compliance testing for the 278 transaction.
After receiving an "accepted" 999 for a test 278 transaction, trading partners are required to call the EDI Helpdesk to request the production 278 transaction set be assigned to them.
Submitting Prior Authorization Requests
Submitting an initial PA request using the 278 transaction does not result in a real-time approval and cannot be used to request PA for drugs and diabetic supplies.
After submitting a PA request via a 278 transaction, providers will receive a real-time response indicating whether the transaction is valid or invalid. If the transaction is invalid, the response will indicate the reject reason(s), and providers can correct and submit a new PA request using the 278 transaction. A real-time response indicating a valid 278 transaction will include a PA number and a pending status. The PA request will be placed in a status of "Pending - Fiscal Agent Review."
The 278 transaction does not allow providers to submit supporting clinical information as required to adjudicate the PA request.
Trading partners cannot submit the 278 transaction through PES. In order to submit the 278 transaction, trading partners will need to use their own software or contract with a software vendor. Topic #7857 Drug Authorization and Policy Override Center
The DAPO Center is a specialized drug help desk for providers to submit PA requests for weight management agents and to request policy overrides for other drugs or diabetic supplies over the phone. After business hours, providers may leave a voicemail message for DAPO Center staff to return the next business day.
The DAPO Center is staffed by certified pharmacy technicians.
PA Requests and Policy Override Decisions
Providers who call the DAPO Center to request a PA for weight management agents or a policy override for other drugs or diabetic supplies are given an immediate decision about the PA or policy override, allowing members to receive drugs or diabetic supplies in a timely manner. The DAPO Center reviews PA requests and policy overrides for members enrolled in BadgerCare Plus, Wisconsin Medicaid, and SeniorCare.
PA Requests
Prescribers or their billing providers are required to be enrolled in Wisconsin Medicaid to submit PA requests to ForwardHealth. Prescribers who are enrolled in Wisconsin Medicaid should indicate their name and NPI as the billing provider on PA requests. Providers who are not enrolled in Wisconsin Medicaid should indicate the name and NPI of the Medicaid-enrolled billing provider (for example, clinic) with which they are affiliated on PA requests.
When a prescriber, or their designee, calls the DAPO Center, a pharmacy technician will ask them a series of questions based on the Prior Authorization Drug Attachment for Weight Management Agents form. The prescriber, or their designee, should have all PA information completed on the appropriate PA drug attachment form before calling the DAPO Center to obtain PA. DAPO Center staff will ask for the name of the caller and the caller's credentials. (Is the caller an RN, physician assistant, physician, certified medical assistant, or nurse practitioner?)
Generally by the end of the call, if the clinical PA criteria are met, DAPO Center staff will approve the PA request based on the information provided by the caller. If the PA request for a weight management agent is approved, a decision notice letter will be mailed to the provider. After a PA request for a weight management has been approved, the prescriber should send the prescription to the pharmacy, and the member can pick up the drug. The member does not need to wait for the prescriber to receive the decision notice to pick up the drug at the pharmacy.
Note: If the provider receives a decision notice letter for a drug for which they did not request PA, the provider should notify the DAPO Center within 14 days of receiving the letter to inactivate the PA.
If a prescriber or their designee calls the DAPO Center to request PA and the clinical criteria for the PA are not met, the caller will be informed that the PA request is not approved because it does not meet the clinical criteria. If the prescriber chooses to submit additional medical documentation for consideration, they may submit the PA request to ForwardHealth for review by a pharmacist. The prescriber is required to submit a PA/RF and the applicable PA drug attachment form with the additional medical documentation. Documentation may be submitted to ForwardHealth through the Portal or by fax or mail.
Providers with questions about pharmacy policies and procedures may continue to call Provider Services.
Policy Override Decisions
When calling the DAPO Center to request a policy override, the following information must be provided:
- Member information
- Provider information
- Prescription information
- The reason for the override request
Topic #455 Fax
Faxing of all PA requests to ForwardHealth may eliminate one to three days of mail time. The following are recommendations to avoid delays when faxing PA requests:
- Providers should follow the PA fax procedures.
- Providers should not fax the same PA request more than once.
- Providers should not fax and mail the same PA request. This causes delays in processing.
PA requests containing X-rays, dental molds, or photos as documentation must be mailed; they may not be faxed.
To help safeguard the confidentiality of member health care records, providers should include a fax transmittal form containing a confidentiality statement as a cover sheet to all faxed PA requests. The Prior Authorization Fax Cover Sheet includes a confidentiality statement and may be photocopied.
Providers are encouraged to retain copies of all PA requests and supporting documentation before submitting them to ForwardHealth.
Prior Authorization Fax Procedures
Providers may fax PA requests to ForwardHealth at 608-221-8616. PA requests sent to any fax number other than 608-221-8616 may result in processing delays.
When faxing PA requests to ForwardHealth, providers should follow the guidelines/procedures listed below.
Fax Transmittal Cover Sheet
The completed fax transmittal cover sheet must include the following:
- Date of the fax transmission
- Number of pages, including the cover sheet (The ForwardHealth fax clerk will contact the provider by fax or telephone if all the pages do not transmit.)
- Provider contact person and telephone number (The ForwardHealth fax clerk may contact the provider with any questions about the fax transmission.)
- Provider number
- Fax telephone number to which ForwardHealth may send its adjudication decision
- To: "ForwardHealth Prior Authorization"
- ForwardHealth's fax number at 608-221-8616 (PA requests sent to any other fax number may result in processing delays.)
- ForwardHealth's telephone numbers
For specific PA questions, providers should call Provider Services.
Incomplete Fax Transmissions
If the pages listed on the initial cover sheet do not all transmit (pages stuck together, the fax machine has jammed, or some other error has stopped the fax transmission), or if the PA request is missing information, providers will receive the following by fax from the ForwardHealth fax clerk:
- A cover sheet explaining why the PA request is being returned.
- Part or all of the original incomplete fax that ForwardHealth received.
If a PA request is returned to the provider due to faxing problems, providers should do the following:
- Attach a completed cover sheet with the number of pages of the fax.
- Resend the entire original fax transmission and the additional information requested by the fax clerk to 608-221-8616.
General Guidelines
When faxing information to ForwardHealth, providers should not reduce the size of the PA/RF or the PA/HIAS1 to fit on the bottom half of the cover page. This makes the PA request difficult to read and leaves no space for consultants to write a response if needed or to sign the request.
If a photocopy of the original PA request and attachments is faxed, the provider should make sure these copies are clear and legible. If the information is not clear, it will be returned to the provider.
If the provider does not indicate his or her fax number, ForwardHealth will mail the decision back to the provider.
ForwardHealth will attempt to fax a response to the PA request to a provider three times. If unsuccessful, the PA request will be mailed to the provider.
If providers are not sure if an entire fax was sent, they should call ForwardHealth's fax clerk at 608-224-6124, to inquire about the status of the fax.
Prior Authorization Request Deadlines
Faxing a PA request eliminates one to three days of mail time. However, the adjudication time of the PA request has not changed. All actions regarding PA requests are made within the predetermined time frames.
Faxed PA requests received after 1 p.m. will be considered as received the following business day. Faxed PA requests received on a Saturday, Sunday, or holiday will be processed on the next business day.
Avoid Duplicating Prior Authorization Requests
After faxing a PA request, providers should not send the original paperwork by mail. Mailing the original paperwork after faxing the PA request will create duplicate PA requests in the system and may result in a delay of several days to process the faxed PA request.
Refaxing a PA request before the previous PA request has been returned will also create duplicate PA requests and may result in delays.
Response Back from ForwardHealth
Once ForwardHealth reviews a PA request, ForwardHealth will fax one of three responses back to the provider:
- "Your approved, modified, or denied PA request(s) is attached."
- "Your PA request(s) requires additional information (see attached). Resubmit the entire PA request, including the attachments, with the requested additional information."
- "Your PA request(s) has missing pages and/or is illegible (see attached). Resubmit the entire PA request, including the attachments."
Resubmitting Prior Authorization Requests
When resubmitting a faxed PA request, providers are required to resubmit the faxed copy of the PA request, including attachments. This will allow the provider to obtain the earliest possible grant date for the PA request (apart from backdating for retroactive enrollment). If any attachments or additional information that was requested is received without the rest of the PA request, the information will be returned to the provider. Topic #458 ForwardHealth Portal Prior Authorization
All providers can use the PA features on the ForwardHealth Portal to do the following:
- Submit PA requests and amendments for all services that require PA.
- Save a partially completed PA request and return at a later time to finish completing it.
- Upload PA attachments and additional supporting clinical documentation for PA requests.
- Receive decision notice letters and returned provider review letters.
- Correct returned PA requests and PA amendment requests.
- Change the status of a PA request from "Suspended" to "Pending."
- Submit additional supporting documentation for a PA request that is in "Suspended" or "Pending" status.
- Search and view previously submitted PA requests or saved PA requests.
- Print a PA cover sheet.
For pharmacy providers only:
- Correct returned PA requests and PA amendment requests.
- Change the status of a PA request from "Suspended" to "Pending."
Submitting PA Requests and Amendment Requests
Providers can submit PA requests for all services that require PA to ForwardHealth via the secure Provider area of the Portal. To save time, providers can copy and paste information from plans of care and other medical documentation into the appropriate fields on the PA request. Except for those providers exempt from NPI requirements, NPI and related data are required on PA requests submitted via the Portal.
Note: If a PA request is urgent, providers must check the Urgent checkbox when submitting the request in the ForwardHealth Portal.
When completing PA attachments on the Portal, providers can take advantage of an Additional Information field at the end of the PA attachment that holds up to five pages of text that may be needed.
Providers may also submit amendment requests via the Portal for PA requests with a status of "Approved" or "Approved with Modifications."
Saving Partially Completed PA Requests
Providers do not have to complete PA requests in one session; they can save partially completed PA requests at any point after the Member Information page has been completed by clicking on the Save and Complete Later button, which is at the bottom of each page. There is no limit to how many times PA requests can be saved.
Providers can complete partially saved PA requests at a later time by logging in to the secure Provider area of the Portal, navigating to the Prior Authorization home page, and clicking on the Complete a Saved PA Request link. This link takes the provider to a Saved PA Requests page containing all of the provider's PA requests that have been saved.
Once on the Saved PA Requests page, providers can select a specific PA request and choose to either continue completing it or delete it.
Note: The ability to save partially completed PA requests is only applicable to new PA requests. Providers cannot save partially completed PA amendments or corrections to returned PA requests or amendments.
30 Calendar Days to Submit or Re-Save PA Requests
Providers must submit or re-save PA requests within 30 calendar days of the date the PA request was last saved. After 30 calendar days of inactivity, a PA request is automatically deleted, and the provider has to re-enter the entire PA request.
The Saved PA Requests page includes a list of deleted PA requests. This list is for information purposes only and includes saved PA requests that have been deleted due to inactivity (it does not include PA requests deleted by the provider). Neither providers nor ForwardHealth are able to retrieve PA requests that have been deleted.
Submitting Completed PA Requests
ForwardHealth's initial receipt of a PA request occurs when the PA request is submitted on the Portal. Normal backdating policy applies based on the date of initial receipt, not on the last saved date. Providers receive a confirmation of receipt along with a PA number once a PA request is submitted on the Portal.
PA Attachments on the Portal
Almost all PA request attachments can be completed and submitted on the Portal. When providers are completing PA requests, the Portal presents the necessary attachments needed for that PA request. For example, if a provider is completing a PA request for physician-administered drugs, the Portal will prompt a PA/PAD and display the form for the provider to complete. Certain PA attachments cannot be completed online or uploaded.
Providers may also upload an electronically completed version of the paper PA attachment form. However, when submitting a PA attachment electronically, ForwardHealth recommends completing the PA attachment online as opposed to uploading an electronically completed version of the paper attachment form to reduce the chances of the PA request being returned for clerical errors.
All PA request attachment forms are available on the Portal. Pharmacy providers may download and print to submit by fax or mail. If pharmacy PA attachment(s) are mailed or faxed, a system-generated Portal PA Cover Sheet must be printed and sent with the attachment to ForwardHealth for processing. When ForwardHealth receives the PA attachment(s) by mail or fax, they will be matched up with the PA/RF that was completed on the Portal.
Note: If the cover sheet could not be generated while submitting the PA request due to technical difficulties, providers can print the cover sheet from the main Portal PA page.
Before submitting any PA request documents, providers should save or print a copy for their records. Once the PA request is submitted, it cannot be retrieved for further editing.
As a reminder, ForwardHealth does not mail back any PA request documents submitted by providers.
Additional Supporting Clinical Documentation
ForwardHealth accepts additional supporting clinical documentation when the information cannot be indicated on the required PA request forms and is pertinent for processing the PA request or PA amendment request. Providers must submit additional supporting clinical information for PA requests or PA amendment requests electronically.
Providers can choose to upload electronic supporting information through the Portal in the following formats:
- JPEG (.jpg or .jpeg)
- PDF (.pdf)
- Rich Text Format (.rtf)
- Text File (.txt)
- OrthoCAD (.3dm) (for dental providers)
JPEG files must be stored with a ".jpg" or ".jpeg" extension; text files must be stored with a ".txt" extension; rich text format files must be stored with an ".rtf" extension; and PDF files must be stored with a ".pdf" extension. Dental OrthoCAD files are stored with a ".3dm" extension.
Microsoft Word files (.docx or .doc) cannot be uploaded but can be saved and uploaded in Rich Text Format or Text File formats.
In addition, providers can also upload additional supporting clinical documentation via the Portal when submitting a PA amendment request.
Pharmacy providers may correct a PA request or PA amendment that is in a "Returned ? Provider Review" status.
ForwardHealth will return pharmacy PA requests and PA amendments requests when the additional documentation could have been indicated on the PA/RF and PA attachments or when the pertinent information is difficult to find.
If pharmacy providers submit supporting clinical information via mail or fax, pharmacy providers are prompted to print a system-generated Portal PA Cover Sheet to be sent with the information to ForwardHealth for processing. Pharmacy providers must list the additional supporting information on the Portal PA Cover Sheet.
"Suspended" PA Requests for Pharmacy Providers
For pharmacy PA requests in a "Suspended" status, the provider has the option to:
- Change a PA request status from "Suspended" to "Pending."
- Submit additional documentation for a PA request that is in "Suspended" or "Pending" status.
Changing a PA Request From "Suspended" to "Pending" for Pharmacy Providers
Pharmacy providers have the option of changing a PA request status from "Suspended — Provider Sending Info" to "Pending" if the pharmacy provider determines that additional information will not be submitted. Changing the status from "Suspended — Provider Sending Info" to "Pending" will allow the PA request to be processed without waiting for additional information to be submitted. The pharmacy provider can change the status by searching for the suspended PA request, checking the box indicating that the PA request is ready for processing without additional documentation, and clicking the Submit button to allow the PA request to be processed by ForwardHealth. There is an optional free form text box, which allows pharmacy providers to explain or comment on why the PA request can be processed.
Submitting Additional Supporting Clinical Documentation for a PA Request in "Suspended" or "Pending" Status for Pharmacy Providers
There is an Upload Documents for a PA link on the PA home page in the provider secured Home Page. By selecting that link, pharmacy providers have the option of submitting additional supporting clinical documentation for a PA request that is in "Suspended" or "Pending" status. When submitting additional supporting clinical documentation for a PA request that is in "Suspended" status, pharmacy providers can choose to have ForwardHealth begin processing the PA request or to keep the PA request suspended. PA requests in a "Pending" status are processed regardless.
Note: When the PA request is in a "Pending" status and the pharmacy provider uploads additional supporting clinical documentation, there may be up to a four-hour delay before the documentation is available to ForwardHealth in the system. If the uploaded information was received after the PA request was processed and the PA request was returned for missing information, the pharmacy provider may resubmit the PA request stating that the missing information was already uploaded. Topic #456 Mail
Any type of PA request may be submitted on paper. Providers may mail completed PA requests, amendments to PA requests, and requests to enddate a PA request to ForwardHealth at the following address:
ForwardHealth
Prior Authorization
Ste 88
313 Blettner Blvd
Madison WI 53784
Providers are encouraged to retain copies of all PA requests and supporting documentation before submitting them to ForwardHealth. Topic #4618 NCPDP Transactions
ForwardHealth accepts the following NCPDP Telecommunication Standard Version D.0 PA transactions: P2 reversal, P3 inquiry, and the P4 request. These transactions enable providers to reverse or inactivate a PA, inquire about PA status, or submit a PA
request.
Providers should work closely with their software vendors or information
technology staff and software user guides to ensure that electronic PAs are
submitted accurately according to the ForwardHealth Payer Sheet: National Council for Prescription Drug Programs Version D.0.
The following are descriptions and/or requirements for each type of NCPDP PA
transaction:
P2 Reversal
To reverse a PA (for example, change the PA to an inactive status) using the P2 transaction, all of the following must be true:
- The provider is the original provider who submitted the PA.
- The PA is in one of the following statuses:
- Approved — The PA request was approved.
- Returned — Provider Review: The PA request was returned to the provider for correction or for additional information.
- Pending — Fiscal Agent Review: The PA request is being reviewed by the fiscal agent.
- Pending — State Review: The PA request is being reviewed by the state.
- Suspended — Provider Sending Information: The PA request was submitted via the ForwardHealth Portal and the provider indicated they will be sending additional supporting information on paper.
- None of the services on an approved PA have been used.
P3 Inquiry
Providers may inquire about PAs they have previously submitted and receive PA information from ForwardHealth by submitting a P3 inquiry transaction. ForwardHealth recommends indicating the PA number, if known, when submitting a P3 inquiry. If a PA number is not included on the P3 inquiry, the most recent matching PA number will be reported.
P4 Request
Providers may submit an initial PA request using the P4 request transaction; however, this will not result in a real-time approval. The P4 request transaction does not allow providers to submit the required clinical information needed to adjudicate the PA request.
After submitting a PA request via the P4 transaction, providers will receive a real-time response indicating whether the transaction is accepted or rejected. If the transaction is rejected, the response will indicate a reject reason(s), and providers can correct and submit a new PA request using the P4 transaction.
An accepted P4 transaction with a captured response status will include a PA number. The PA request will be placed in a status of "Pending — Fiscal Agent Review."
Uploading Additional Documentation
Once providers receive the PA number, they may upload additional documentation (for example, the PA attachment, supporting clinical information) for the pending PA through the Portal.
After receiving the additional documentation, ForwardHealth will adjudicate the PA request and send the provider either a decision notice or a returned provider review letter.
Returned Provider Review Letter
Once the PA request is in a Pending — Fiscal Agent Review status, ForwardHealth will review the request and, if the additional documentation has not been submitted, will send providers a returned provider review letter indicating the information required to adjudicate the request. PA requests cannot be adjudicated until ForwardHealth receives the additional information.
After receiving a returned provider review letter, providers should submit the additional information through the Portal, fax, or mail if they have not already done so. Providers have 30 calendar days from the date on the returned provider review letter to submit the additional information or the PA request will become inactive. After a PA request has become inactive, providers can submit a new request using the P4 transaction. Topic #1416 STAT-PA
Most drugs do not require PA. For drugs that require PA, pharmacy providers may submit PA requests through the STAT-PA system, the ForwardHealth Portal, an NCPDP transaction, or on paper.
A STAT-PA Quick Reference Guide includes information about STAT-PA inquiries.
The STAT-PA system allows enrolled pharmacy providers to request and receive PA electronically, rather than on paper, for certain drugs. Providers are allowed to submit up to 24 PA requests per connection for phone and help desk queries. The STAT-PA system can be accessed using the STAT-PA System Instructions. The system is available 24 hours a day, seven days a week via phone at 800-947-1197.
STAT-PA Request Follow-Up
A STAT-PA request will either be approved or returned.
For STAT-PA requests that are approved, providers receive verbal confirmation of the approval at the end of the transaction. The verbal confirmation includes the following information:
- A PA number
- The grant date and expiration date
- The allowable days' supply
Providers are encouraged to write this information in the applicable fields of the PA drug attachment.
(Note: When a STAT-PA request is approved, the claim may be submitted immediately.)
For STAT-PA requests that are returned, providers receive the following information at the end of the transaction:
- A PA number
- The reason for the return
- A statement to submit the PA request with complete clinical documentation
Providers also receive a returned provider review letter by mail.
Reconsideration of a STAT-PA Request
Submit the following on paper for reconsideration of a STAT-PA request:
- A PA/RF. List the PA number assigned to the returned STAT-PA on the front of the PA/RF in the description field.
- An appropriate PA form.
- A fax number, if available.
Amending Drug Prior Authorizations via STAT-PA
Providers may amend drug PAs that were initially approved through the STAT-PA system. Providers will be able to enddate, backdate, and change the quantity on an existing PA.
The following are requirements for each type of amendment.
Enddate a Prior Authorization via STAT-PA
Providers may enddate PAs using the STAT-PA system according to the following requirements:
- The PA must be for a drug.
- The provider must be the provider who obtained PA and must have the provider number used to obtain the PA.
- The PA must have been approved through STAT-PA initially.
- Prior authorization for the drug can be submitted through STAT-PA currently.
- The end date must be after the grant date and before the expiration date.
- The PA must not have been previously amended.
- The end date must be within 14 days of the current date.
- The end date must be within 29 days of the services (days' supply) that are already used on the PA.
Backdate a Prior Authorization via STAT‑PA
Providers can backdate up to 14 days prior to the date on which the PA was
initially submitted. To backdate a PA through STAT-PA, all of the following must
be true:
- The PA must be for a drug.
- The provider must be the provider who obtained PA and must have the provider number used to obtain the PA.
- The PA must have been approved through STAT-PA initially.
- PA for the drug can be submitted through STAT-PA currently.
- The backdate must be before the grant date.
- The PA must not have been previously amended.
- The backdated PA must not duplicate another PA.
Change the Days' Supply of a Prior Authorization via STAT-PA
To change the days' supply of a PA through STAT-PA, all of the following must
be true:
- The PA must be for a drug.
- The provider must be the provider who obtained PA and must have the provider number used to obtain the PA.
- The PA must have been approved through STAT-PA initially.
- PA for the drug can be submitted through STAT-PA currently.
- The PA must not have been previously amended.
- The change in days' supply must not duplicate another PA.
- The change in days' supply does not exceed the maximum allowed days' supply for the PA.
For STAT-PA amendment requests that are approved, providers receive verbal confirmation of the approval at the end of the transaction, as well as by mail.
If all of the criteria to amend a drug PA through STAT-PA cannot be met, providers may submit a PA amendment request on paper or via the Portal.
Dispensing STAT-PA Drugs When STAT-PA Is Unavailable
If the STAT-PA system is unavailable, a provider may still dispense a STAT-PA-approved drug. If a provider dispenses a new prescription for a STAT-PA-approved drug, the following steps must be taken:
- Obtain the member's ForwardHealth identification card, beige paper or white paper EE card, or SeniorCare identification card, and verify enrollment. Enrollment verification may be done by submitting a real-time claim for the drug or by using one of the other enrollment verification methods such as Wisconsin's EVS.
- Determine that the diagnosis is appropriate.
- Determine that the member is not taking any other drug in the same category. (The prospective DUR system may identify therapeutic duplications at other pharmacies.)
- Dispense up to a 14 days' supply of the drug.
- Request PA from the STAT-PA system when it is available. A PA request submitted using the STAT-PA system may be backdated up to 14 days using the STAT-PA system.
If a STAT-PA request is returned, submit a paper PA request within 14 days of dispensing along with documentation supporting what was done in steps 2 through 5 of this process.
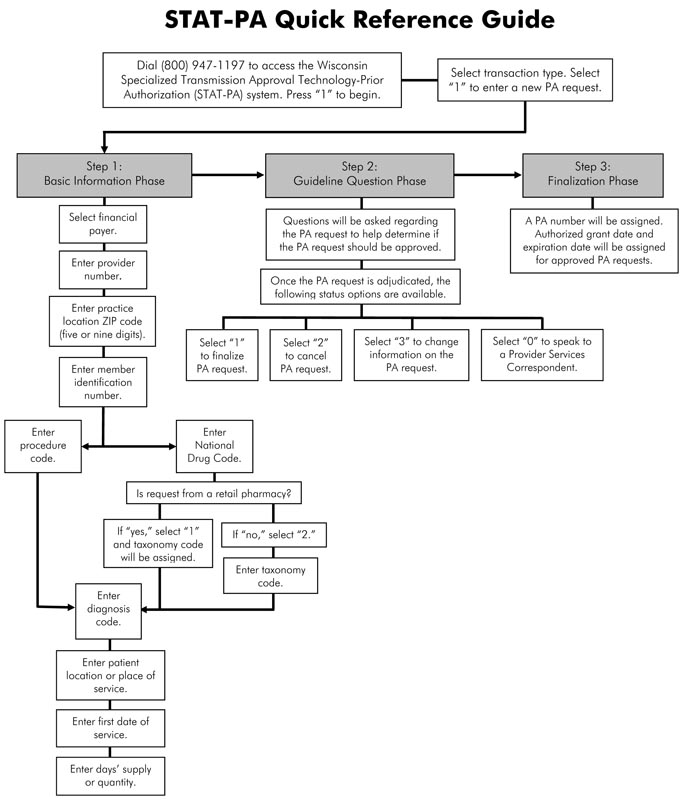
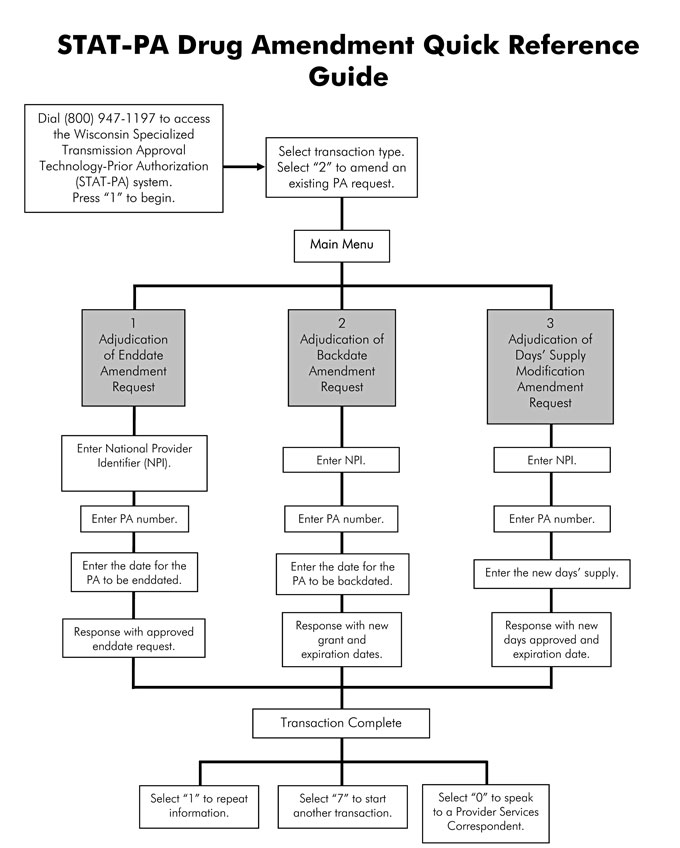 Topic #20078 An Introduction to Brand Medically Necessary Drugs and Brand Before Generic Drugs
Per Wis. Admin. Code § DHS 107.10(2), ForwardHealth requires PA for the coverage of certain drugs.
Providers should refer to the Brand Medically Necessary Drugs and Brand Before Generic Drugs data table for a list of drugs that have specific PA or policy requirements for BMN drugs or BBG drugs. The table is updated monthly. It is the prescriber's responsibility to regularly review the table for the most current information on which drugs require PA.
If a drug is listed on the Brand Medically Necessary Drugs and Brand Before Generic Drugs data table as requiring PA, the prescriber is required to complete the appropriate PA request form for that drug. The form must include accurate and complete answers to clinical information about the member's medical history. Topic #20077 Brand Before Generic Drugs
The Brand Medically Necessary Drugs and Brand Before Generic Drugs data table provides the most current list of BBG drugs that require PA.
Clinical Criteria for Brand Before Generic Drugs
Clinical criteria for approval of a BBG drug that requires PA are all of these:
- The drug has been defined by ForwardHealth as a generic drug that requires BBG PA.
- The member satisfies established coverage and PA policy for the brand equivalent drug.
- The prescriber submits detailed documentation of the member's relevant medication treatment history.
- The member has taken the requested generic drug for at least 30 consecutive days and had a measurable therapeutic response. (Note: Documentation of approximate dates taken may come from the pharmacy or the prescriber.)
- The member has experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction to the brand equivalent drug. (Note: Documentation of approximate dates taken may come from the pharmacy or the prescriber.)
- The prescriber includes a description of the unsatisfactory therapeutic response or clinically significant adverse drug reaction that can be directly attributed to the brand equivalent drug.
- The prescriber has indicated how the generic drug will prevent recurrence of an unsatisfactory therapeutic response or clinically significant adverse drug reaction.
Note: Member or prescriber preference for the use of a BBG drug will not be considered as criteria to support the need for a BBG drug.
Submitting Prior Authorization Requests for Brand Before Generic Drugs
PA requests for BBG drugs must be completed and signed by the prescriber and must be submitted using both of these forms:
Pharmacy providers may submit PA requests for BBG drugs on the Portal, by fax, or by mail (but not using the STAT-PA system).
Brand Before Generic Drugs on the Preferred Drug List
In addition to meeting the clinical criteria for BBG drugs, all existing PDL policies apply to BBG drugs on the PDL. This includes, but is not limited to, policy pertaining to drug classes that require step therapy, drugs that require clinical PA, and drugs that have non-preferred brand equivalents.
In addition to completing the PA/DGA form for BBG drugs, the prescriber is required to complete any other required drug- or drug-class-specific PA form and provide any medical records and/or documentation required for the brand drug or applicable drug class. Examples include, but are not limited to, the following:
- A BBG drug, where the non-preferred brand requires a specific PA form
- A drug or drug class that requires specific medical records and/or documentation to be submitted with the PA request
For example, if a prescriber requests BBG PA for a generic drug and the non-preferred brand drug's PDL PA criteria requires the use of at least two PDL preferred drugs in the same drug class with an unsatisfactory therapeutic response or clinically significant adverse drug reaction, this requirement must also be met before a PA request can be approved for the generic drug.
Submitting Prior Authorization Requests for Brand Before Generic Drugs on the Preferred Drug List
PA requests for BBG drugs on the PDL must be completed and signed by the prescriber and must be submitted using all of these forms:
- Section VI (Clinical Information for Drugs with Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form
- The PA/RF
- Any other drug- or drug class-specific PA request form that would be required for the brand equivalent drug or applicable drug class
Pharmacy providers may submit PA requests for BBG drugs on the PDL on the Portal, by fax, or by mail (but not using the STAT-PA system). Topic #2017 Brand Medically Necessary Drugs: A Pharmacy Provider's Responsibilities
Pharmacy providers are required to submit the completed PA/BMNA form received from the prescriber for BMN drugs requiring PA and a completed PA/RF to ForwardHealth. Pharmacy providers may submit PA requests for BMN drugs requiring PA on the Portal, by fax, or by mail (but not using the STAT-PA system.)
To obtain BMN PA, pharmacies are required to do the following:
- Obtain a prescription with "brand medically necessary" written in the prescriber's own handwriting either directly on the prescription or on a separate order attached to the original prescription.
- Receive the completed, signed, and dated PA/BMNA form from the prescriber.
- Complete a PA/RF to be submitted with the PA/BMNA form.
Documentation on the PA/BMNA form regarding the following may come from the pharmacy or the prescriber:
- The names of the manufacturers of the generic drugs that were taken
- The NDCs for the generic drugs that were taken
- The approximate dates the generic and brand drugs were taken
Note: For appropriate reimbursement, pharmacy providers are required to submit claims with a "1" in the DAW/Product Selection Code, as appropriate.
ForwardHealth does not require pharmacy providers to submit a copy of the BMN prescription or order attachment with the PA request. Pharmacy providers should retain the prescription, and if applicable, the order attachment, for all BMN drugs with the prescriber's handwritten certification of "brand medically necessary" in their pharmacy records. Pharmacy providers are required to ensure all necessary documentation is obtained before submission of the PA request. Pharmacy providers who receive BMN PA for brand name drugs requiring PA or for drugs subject to BMN policy may be subject to audits at any time. Pharmacy providers are also required to retain a completed, signed, and dated copy of the PA forms and any additional supporting documentation received from the prescriber and produce it for and/or submit it to ForwardHealth upon request. ForwardHealth may deny or recoup payment for claims submitted that do not meet BMN PA or policy requirements.
Pharmacy providers may submit an amendment request to ForwardHealth to amend an approved or modified BMN PA request. Topic #2016 Brand Medically Necessary Drugs: A Prescriber's Responsibilities
As required in Wis. Admin. Code § DHS 107.10(3)(c) when a prescription is for a BMN drug, the prescriber is required to handwrite "brand medically necessary" directly on the prescription. ForwardHealth also allows the required statement to be handwritten on a separate order attached to the original prescription. Typed certification, signature stamps, or certification handwritten by someone other than the prescriber does not satisfy this requirement. Blanket authorization for an individual member, drug, or prescriber is not acceptable documentation.
Prescribers are also required to complete a PA/BMNA form for BMN drugs that require PA. The PA/BMNA form must include accurate and complete answers and clinical information about the member's medical history and must include the prescriber's handwritten signature and date.
The PA/BMNA form may be faxed or mailed to the pharmacy, or the member may carry the form with the prescription to the pharmacy. The pharmacy provider will use the completed PA/BMNA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA/BMNA form to ForwardHealth.
Prescribers are required to retain a completed, signed, and dated copy of the PA form and any supporting documentation.
For drugs that are subject to BMN policy but do not require PA, prescribers are still required to handwrite "brand medically necessary" on the prescription either directly on the prescription or on a separate order attached to the original prescription, and pharmacy providers are required to submit a DAW/Product Selection Code 1 (Substitution not allowed by prescriber). The completion of the PA/BMNA form is not required.
The Brand Medically Necessary Drugs and Brand Before Generic Drugs data table provides the most current list of the BMN drugs that require PA.
Clinical Criteria for Brand Medically Necessary Drugs That Require Prior Authorization
Clinical criteria for approval of a BMN drug that requires PA are all of the following:
- The drug has been defined by ForwardHealth as a brand drug that requires BMN PA.
- The member satisfies established coverage and PA policy for the generic equivalent drug.
- The prescriber submits detailed documentation of the member's relevant medication treatment history.
- The member has taken the requested BMN drug for at least 30 consecutive days and had a measurable therapeutic response. (Note: Documentation of approximate dates taken may come from the pharmacy or the prescriber.)
- The prescriber has indicated how the BMN drug will prevent recurrence of an unsatisfactory therapeutic response or clinically significant adverse drug reaction.
- The member has experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction to the generic equivalent drug from at least two different manufacturers.
For each generic trial, the following must be documented:
- Generic drug manufacturer or NDC (Note: Documentation may come from the pharmacy or the prescriber.)
- Approximate dates taken (Note: Documentation may come from the pharmacy or the prescriber.)
- A description of the unsatisfactory therapeutic response or clinically significant adverse drug reaction that can be directly attributed to the generic equivalent drug
Note: Member or prescriber preference for the use of a BMN drug will not be considered as criteria to support the need for a BMN drug.
Brand Medically Necessary Drugs With Generic Equivalents on the Preferred Drug List
In addition to meeting the clinical criteria for BMN drugs that require PA, existing PDL policies will apply to BMN drugs with generic equivalents on the PDL. This includes, but is not limited to, policy pertaining to drug classes that require step therapy, drugs that require clinical PA, and drugs that have non-preferred generic equivalents.
In addition to completing the PA/BMNA form for BMN drugs requiring PA, the prescriber is required to complete any other required drug- or drug-class-specific PA form and provide any medical records and/or documentation required for the generic equivalent drug or applicable drug class. Examples include, but are not limited to, the following:
- A BMN drug, where its non-preferred generic equivalent requires a specific PA form
- A drug or drug class that requires specific medical records and/or documentation to be submitted with the PA request
For example, if a prescriber requests BMN PA for a brand drug and the non-preferred generic equivalent drug's PDL PA criteria requires the use of at least two PDL preferred drugs in the same drug class with an unsatisfactory therapeutic response or clinically significant adverse drug reaction, this requirement must also be met before a PA request can be approved for the brand name drug.
The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs. Topic #2012 Titration
A prescriber who titrates a BMN drug requiring PA for a member may request more than one strength of the drug on a PA/BMNA form. The prescriber should handwrite "brand medically necessary" on each prescription for each strength of the titrated BMN drug requiring PA directly on the prescription or on a separate order attached to the original prescription sent to the pharmacy with the PA/BMNA form. Pharmacy providers should include the NDCs of all requested strengths of the drug on the PA/RF. Topic #1999 A Brief Overview of the Preferred Drug List
ForwardHealth makes recommendations to the Wisconsin Medicaid Pharmacy PA Advisory Committee on whether certain PDL drugs should be preferred or non-preferred. These recommendations are based primarily on objective evaluations of a drug's relative safety, effectiveness, clinical outcomes, and relative cost (to Wisconsin Medicaid) in comparison with other therapeutically interchangeable, alternative agents in the same drug class.
New drugs are usually added to existing drug classes on the PDL as non-preferred drugs until their next scheduled class review by the Wisconsin Medicaid Pharmacy PA Advisory Committee.
The PDL is not a drug formulary and is not a comprehensive list of covered drugs.
Drugs and drug classes on the PDL are covered fee for service. Certain drugs may have restrictions (for example, diagnosis, quantity limits, age limits).
Prescribers are encouraged to write prescriptions for preferred drugs if medically appropriate. Non-preferred drugs may be covered with an approved PA request. Most preferred drugs do not require PA, except in designated classes identified on the Preferred Drug List Quick Reference data table. Topic #10937 A Pharmacy Provider's Responsibilities for Prior Authorization for Preferred Drug List Drugs
Pharmacy providers should review the Preferred Drug List Quick Reference for the most current list of preferred and non-preferred drugs.
When a pharmacy provider receives a prescription for a non-preferred drug, the pharmacy provider is encouraged to contact the prescriber to discuss preferred drug options. The prescriber may choose to change the prescription to a preferred drug, or if the non-preferred drug is medically necessary for the member, the prescriber must complete the appropriate PA form.
Pharmacy providers are required to submit PA requests using the completed, signed, and dated PA form from the prescriber and a completed PA/RF to ForwardHealth.
Pharmacy providers may submit PA requests using the STAT-PA system (when applicable), on the Portal, by fax, or by mail.
Pharmacy providers must retain a completed, signed, and dated copy of the PA form and any supporting documentation received from the prescriber. Pharmacy providers may not reuse PA forms from previously approved PA requests for subsequent PA request submissions.
Note: If additional information needs to be addressed and can be provided by the pharmacy provider (for example, medication refill history and compliance), the pharmacy provider should add the information to the Prior Authorization Fax Cover Sheet or to the Additional Information section available on most PA forms. The pharmacy provider must sign and date the entry to clearly identify the information source.
PA for Weight Management Agents
Pharmacy providers may not request PA for weight management agents; prescribers, or their designees, must request PA for weight management agents. Topic #1987 A Prescriber's Responsibilities for Prior Authorization for Preferred Drug List Drugs
Prescribers are encouraged to write prescriptions for preferred drugs.
Prescribers are encouraged to prescribe more than one preferred drug before a non-preferred drug is prescribed from the same drug class.
Prescribers must complete, sign, and date the appropriate PA form for drugs on the Preferred Drug List Quick Reference that require PA.
Prescribers must include all the required clinical information about the member's medical history on the PA form. The prescriber's signature on the PA form attests that the information provided is complete and accurate.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Completing a PA Form
If a non-preferred drug or a preferred drug that requires clinical PA is medically necessary for a member, the prescriber must complete, sign, and date the appropriate PA form for that drug. When completing the PA form, prescribers are required to provide a handwritten signature on the form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Prescribers are required to retain a completed, signed, and dated copy of the PA form and any supporting documentation. Pharmacy providers may not reuse PA forms from previously approved PA requests for subsequent PA request submissions.
Note: If additional information needs to be addressed and can be provided by the pharmacy provider (for example, medication refill history and compliance), the pharmacy provider should add the information to the Prior Authorization Fax Cover Sheet or to the Additional Information section available on most PA forms. The pharmacy provider must sign and date the entry to clearly identify the information source.
PA for Weight Management Agents
Prescribers, or their designees, must request PA for weight management agents; pharmacy providers may not request PA for weight management agents. Topic #15037 Alzheimer's Agents
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Leqembi IQLIK
Leqembi IQLIK requires clinical PA.
PA requests for Leqembi IQLIK must be completed, signed, and dated by the prescriber. PA requests for Leqembi IQLIK must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Leqembi IQLIK may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
PA requests will not be considered for Leqembi IQLIK that will be administered in a medical office or medical facility.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Leqembi IQLIK
The clinical criteria that must be documented for an initial approval of a PA request for Leqembi IQLIK includes both of the following:
- Leqembi IQLIK must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The member has been receiving IV infusions of Leqembi for at least the past 18 months.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Leqembi IQLIK. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Leqembi IQLIK are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Leqembi IQLIK may be approved for up to 365 days. Renewal PA requests must include supporting clinical information and copies of the member's current medical records demonstrating clinical improvement compared to the member's baseline prior to the initiation of Leqembi.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Memantine Products
Because the safety and effectiveness of all memantine products for pediatric patients has not been established, coverage will be restricted to adult members who are 18 years of age or older.
ForwardHealth will not cover memantine products for members 17 years of age or younger. PA requests submitted for memantine products for members 17 years of age or younger will be returned as a noncovered service. Members do not have appeal rights for noncovered services. Topic #23778 Analgesics, Miscellaneous
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Journavx
Clinical PA criteria is required for Journavx.
PA requests for Journavx must be completed, signed, and dated by the prescriber. PA requests for Journavx must be submitted using the PA/PDL for Journavx form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/PDL for Journavx form and a completed PA/RF to ForwardHealth.
PA requests for Journavx may be submitted using the STAT-PA system, on the Portal, by fax, or by mail.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Journavx
Clinical criteria for approval of a PA request for Journavx are all of the following:
- The member has moderate to severe acute pain.
- The prescriber has determined that treatment with acetaminophen is not appropriate for the member.
- The prescriber has determined that treatment with a non-steroidal inflammatory drug is not appropriate for the member.
If the clinical criteria for Journavx are met, PA requests may be approved for up to 14 days. Topic #9837 Antibiotics, Inhaled
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Non-preferred drugs in the antibiotics, inhaled drug class require PA.
Tobi Podhaler and Cayston require clinical PA.
PA requests for non-preferred drugs in the antibiotics, inhaled drug class must be completed, signed, and dated by the prescriber. PA requests for non-preferred drugs in the antibiotics, inhaled drug class must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of non-preferred drugs in the antibiotics, inhaled drug class must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred drugs in the antibiotics, inhaled drug class may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
The following indicate how PA requests for non-preferred drugs in the antibiotics, inhaled drug class will be approved when clinical criteria have been met:
- PA requests will be approved for up to a maximum 28-day supply per dispensing.
- PA requests will be approved with an alternating 28-day treatment schedule of 28 days of a non-preferred drug in the antibiotics, inhaled drug class with 28 days of no inhaled antibiotics or anti-infective agents.
Note: The alternating 28-day treatment schedule with 28 days of no inhaled antibiotics or anti-infective agents previously listed does not apply to approved PA requests for Cayston for CAT treatment. When PA is approved for Cayston for CAT, members may alternate between two inhaled antibiotics or anti-infective agents.
Clinical Criteria for Tobi Podhaler
Clinical criteria that must be documented for approval of a PA request for Tobi Podhaler are all of the following:
- The member has cystic fibrosis.
- The prescriber has confirmed that the member has a positive sputum culture for Pseudomonas aeruginosa. Prescribers are required to include a copy of the sputum culture report with all PA requests.
- The prescriber has confirmed that the member is not colonized with Burkholderia cepacia.
- The member is not receiving treatment with other inhaled antibiotics or anti-infective agents, including alternating treatment schedules. Prescribers are required to provide a history of all inhaled antibiotics or anti-infective agents within the most recent 90-day period.
- The prescriber has submitted detailed clinical justification for prescribing Tobi Podhaler instead of Bethkis, Kitabis Pak, or tobramycin solution (generic Tobi), including clinical information describing why the member cannot use Bethkis, Kitabis Pak, or tobramycin solution (generic Tobi), and why it is medically necessary that the member receive Tobi Podhaler instead of Bethkis, Kitabis Pak, or tobramycin solution (generic Tobi).
- The member has been adherent with their prescribed treatment regimen for inhaled medications.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Tobi Podhaler. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
Initial PA requests for Tobi Podhaler may be approved for up to 183 days.
Renewal PA requests for Tobi Podhaler may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Cayston
Clinical criteria that must be documented for approval of a PA request for Cayston are all of the following:
- The member has cystic fibrosis.
- The prescriber has confirmed that the member has a positive sputum culture for Pseudomonas aeruginosa. Prescribers are required to include a copy of the sputum culture report with all PA requests.
- The prescriber has confirmed that the member is not colonized with Burkholderia cepacia.
- The member is not receiving treatment with other inhaled antibiotics or anti-infective agents, including alternating treatment schedules. Prescribers are required to provide a history of all inhaled antibiotics or anti-infective agents within the most recent 90-day period.
- At least one of the following is true:
- The member has previously used inhaled tobramycin and experienced a clinically significant adverse drug reaction or an unsatisfactory therapeutic response.
- The member has a medical condition(s) that prevents the use of inhaled tobramycin.
- The member has been adherent with their prescribed treatment regimen for inhaled medications.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Cayston. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
Initial PA requests for Cayston may be approved for up to 183 days.
Renewal PA requests for Cayston may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Cayston for Continuous Alternating Therapy
Clinical criteria that must be documented for approval of a PA request for Cayston for CAT are all of the following:
- The member has cystic fibrosis.
- The prescriber has confirmed that the member has a positive sputum culture for Pseudomonas aeruginosa. Prescribers are required to include a copy of the sputum culture report with all PA requests.
- The prescriber has confirmed that the member is not colonized with Burkholderia cepacia.
- The member is experiencing persistent exacerbations or FEV1 decline with no significant improvement while using a single inhaled antibiotic drug or significant worsening of other markers that are being regularly tracked to monitor pulmonary disease progression.
- The prescriber has provided specific treatment goals for the member's CAT.
- The prescriber has provided a history of all inhaled antibiotics or anti-infective agents within the most recent 90-day period.
- The member has been adherent with their prescribed treatment regimen for inhaled medications.
Note: ForwardHealth will not consider CAT as an initial choice for inhaled antibiotic therapy.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Cayston for CAT. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
Initial PA requests for Cayston for CAT may be approved for up to 183 days.
Renewal PA requests for Cayston for CAT may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #24043 Antibiotics, Other
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Blujepa and Orlynvah
Blujepa and Orlynvah require clinical PA.
PA requests for Blujepa or Orlynvah must be completed, signed, and dated by the prescriber. PA requests for Blujepa or Orlynvah must be submitted using the PA/PDL for Blujepa and Orlynvah form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/PDL for Blujepa and Orlynvah form and a completed PA/RF to ForwardHealth.
PA requests for Blujepa or Orlynvah may be submitted using the STAT-PA system, on the Portal, by fax, or by mail.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Blujepa and Orlynvah
Clinical criteria for approval of a PA request for Blujepa or Orlynvah are all of the following:
- The member is female.
- The member's age and weight are consistent with the FDA-approved product labeling for the requested drug.
- The member is being treated for an uncomplicated urinary tract infection (Blujepa or Orlynvah) or uncomplicated urogenital gonorrhea (Blujepa only) that is caused by an organism that is susceptible to the requested drug.
- The prescriber has determined that treatment with an alternative oral antibiotic is not appropriate for the member.
If the clinical criteria for Blujepa or Orlynvah are met, PA requests may be approved for up to five days. Topic #21237 Anticonvulsants
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Expedited Emergency Supply for Anticonvulsants
ForwardHealth strongly encourages pharmacy providers to utilize the expedited emergency supply process for anticonvulsant drugs when it is determined that the member should begin taking the medication immediately, but the PA request submission and adjudication process would delay dispensing the medication to the member. This may occur if the member receives a prescription for a covered anticonvulsant drug and the prescriber has not completed the necessary PA form or the PA request is still in process.
Expedited emergency supply requests for anticonvulsant drugs will be approved for up to a 14-day supply. Members will be limited to receiving two 14-day expedited emergency supply approvals of the same drug from one pharmacy provider within a six-month time period. A PA is not required to be in process when the first expedited emergency supply request is submitted.
If a second expedited emergency supply is necessary for a member, there must be a PA request for the drug submitted to ForwardHealth, and it must be in the process of being adjudicated. The second expedited emergency supply request may be approved if a PA request is in process for the same drug and strength and the PA is submitted by the pharmacy that submitted the first expedited emergency supply request.
If a PA request for the drug has been approved, the second expedited emergency supply request will not be approved.
Requests for a second expedited emergency supply request may be submitted seven to 21 days after the initial request was submitted. Second expedited emergency supply requests will not be approved if they are submitted before day seven or after day 21.
For example, if an initial expedited emergency supply request was submitted on March 4 and a PA request for the drug was submitted on March 7 and a second expedited emergency supply is necessary for the member because the PA request had not yet been adjudicated, the second expedited emergency request may be submitted on March 10 or as late as March 24.
Vigadrone and Vigafyde
Clinical PA is required for Vigadrone and Vigafyde.
PA requests for Vigadrone or Vigafyde must be completed, signed, and dated by the prescriber. PA requests for Vigadrone or Vigafyde must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Vigadrone or Vigafyde may be submitted may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Vigadrone and Vigafyde
The clinical criteria that must be documented for approval of a PA request for Vigadrone or Vigafyde includes both of the following:
- The prescriber has submitted detailed clinical justification for prescribing Vigadrone or Vigafyde instead of Sabril or vigabatrin (generic Sabril).
- The clinical information must document why the member cannot use Sabril or vigabatrin (generic Sabril), including why it is medically necessary that the member receive Vigadrone or Vigafyde instead of Sabril or vigabatrin (generic Sabril).
Supporting clinical documentation and a copy of the member's current medical records must be submitted with the PA request to support the member's need for Vigadrone or Vigafyde. Initial PA requests for Vigadrone or Vigafyde may be approved for up to 183 days.
Renewal PA requests may be approved for up to 365 days. Medical records must be submitted demonstrating clinical improvement and must reflect member compliance with Vigadrone or Vigafyde.
Note: Vigadrone and Vigafyde are not available through expedited emergency supply. Topic #8377 Antiemetics, Cannabinoids
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
PA is required for all antiemetic, cannabinoid drugs. PA requests for antiemetics, cannabinoids drugs must be completed, signed, and dated by the prescriber. PA requests for antiemetics, cannabinoids drugs must be submitted using the Prior Authorization Drug Attachment for Antiemetics, Cannabinoids form. Clinical documentation supporting the use of antiemetics, cannabinoids drugs must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Antiemetics, Cannabinoids form and a completed PA/RF to ForwardHealth.
PA requests for antiemetics, cannabinoids drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
A copy of the member's current medical records must be submitted with all PA requests for antiemetics, cannabinoids drugs. Medical records must document the member's medical work-up for the condition being treated including complete problem and medication lists.
If the clinical criteria for antiemetics, cannabinoids drugs are met, PA requests may be approved for up to 183 days.
Clinical Criteria for Dronabinol for Anorexia Associated With Weight Loss With HIV
The clinical criteria for approval of a PA request for dronabinol for the treatment of anorexia associated with weight loss with HIV for members who are not currently receiving dronabinol are all of the following:
- The member has HIV.
- The member is experiencing anorexia associated with weight loss.
- One of the following is true:
- The member's current BMI is 18.5 or greater, and the member had a 10% or greater decrease in weight from baseline in the past six months.
- The member's current BMI is less than 18.5.
- The member's daily caloric intake has been optimized.
The clinical criteria for approval of a PA request for dronabinol for the treatment of anorexia associated with weight loss with HIV for members who are currently receiving dronabinol are one of the following:
- The member's current BMI is less than 18.5.
- The member's current BMI is in the normal range (18.5–24.9) and has been stabilized in this range for less than six months.
Note: Members whose BMI has been stabilized in the normal range or above (18.5 or greater) for at least six months will not be granted a dronabinol PA renewal.
Clinical Criteria for Dronabinol for Chemotherapy-Related Nausea and Vomiting
The clinical criteria for approval of a PA request for dronabinol for the treatment of chemotherapy-related nausea and vomiting are all of the following:
- The member is currently receiving chemotherapy.
- The member is experiencing chemotherapy-related nausea and vomiting.
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with ondansetron or granisetron.
- The member is unable to take both ondansetron and granisetron due to one of the following:
- There is a clinically significant drug interaction between another drug(s) the member is taking and both ondansetron and granisetron.
- The member has a medical condition(s) that prevents the use of both ondansetron and granisetron.
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with at least one of the following chemotherapy-related nausea and vomiting treatments: dexamethasone, haloperidol, lorazepam, metoclopramide, olanzapine, prochlorperazine, or promethazine.
Topic #18357 Antifungals, Topical
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Tavaborole
PA requests for tavaborole must be completed, signed, and dated by the prescriber. PA requests for tavaborole must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for tavaborole may be submitted on the Portal, by fax, or by mail. PA requests for tavaborole may not be submitted using the STAT-PA system.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Tavaborole
Clinical criteria that must be documented for approval of a PA request for tavaborole are both of the following:
- The member has onychomycosis of the toenails.
- The member has been treated with ciclopirox topical solution for 48 weeks and experienced an unsatisfactory therapeutic response.
In addition to meeting both of the above clinical criteria, one of the following must be true:
- The member has been treated with oral terbinafine and experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction.
- There is a clinically significant drug interaction between another drug the member is taking and oral terbinafine.
- The member has a medical condition(s) that prevents the use of oral terbinafine.
Prescribers should indicate the specific details about the unsatisfactory therapeutic response, clinically significant adverse drug reaction, clinically significant drug interaction or the medical condition(s) preventing the member from using oral terbinafine.
PA requests for tavaborole may be approved for up 365 days. Topic #18457 Antipsychotics
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Abilify MyCite
Abilify MyCite requires clinical PA.
PA requests for Abilify MyCite must be completed, signed, and dated by the prescriber. PA requests for Abilify MyCite must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form and the PA/RF.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
PA requests for Abilify MyCite may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Abilify MyCite
Clinical criteria that must be documented for approval of a PA request for Abilify MyCite are all of the following:
- The member has a mobile device with a data plan that is compatible with the MyCite monitoring application.
- The member has attempted standard measures to improve medication adherence. The prescriber must identify what adherence measures the member has previously attempted.
- The member has previously taken oral aripiprazole and had a measurable therapeutic response. The aripiprazole dose and approximate dates taken must be documented.
- The prescriber has agreed to track and document the member's adherence with Abilify MyCite using the MyCite software program.
Clinical documentation and medical records must be submitted with the PA request to support the need for Abilify MyCite. PA requests for Abilify MyCite may be approved for up to 90 days.
PA for Antipsychotic Drugs for Children 8 Years of Age and Younger
All antipsychotic drugs prescribed for oral use for all children 8 years of age and younger require PA.
PA requests must meet the criteria for children 8 years of age and younger to allow coverage of an antipsychotic drug.
PA requests for antipsychotic drugs for children 8 years of age and younger must be submitted on the Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form.
Claims submitted for an antipsychotic drug for children 8 years of age and younger without an approved Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form on file will be denied.
Prescribers are encouraged to write prescriptions for preferred antipsychotic drugs.
Background
ForwardHealth monitors the use of antipsychotic drugs in young children. The PA process is intended to scrutinize the prescribing of antipsychotic drugs for mood disorders and the monitoring of metabolic effects of this class of drugs. ForwardHealth strongly encourages prescribers to earnestly engage in clarifying the differentiation between DMDD and bipolar disorder, NOS.
The increased use of antipsychotic drugs in young children over the past decade has been associated with the frequent use of the diagnosis of bipolar disorder, NOS (F31.9) per the DSM-5 in many of these children. A discussion and review of the issues in differentiating bipolar disorder, NOS from DMDD can be found in the Journal of the American Academy of Child and Adolescent Psychiatry, Volume 52, Issue 5, May 5, 2013, pp. 466-481 (Towbin, K. MD, Axelson, D. MD, Leibenluft, E. MD, Birmaher, B. MD, "Differentiating Bipolar Disorder-Not Otherwise Specified and Severe Mood Dysregulation").
In recent years, there has been some progress in the research of these clinical issues. Specifically, the DSM-5 addresses the inclusion of DMDD (F34.8). This evolved out of the observation that many children with a diagnosis of bipolar disorder do not progress to having bipolar disorder, NOS as adults, thus bringing into question the use of antipsychotic drugs for these children. Many of the children with DMDD (or severe mood dysregulation as referenced in several research studies) respond to stimulants and/or SSRI antidepressants. Although SSRIs may cause mild activation when first administered, this is not necessarily mania. These antidepressants can be very effective for irritability associated with anxiety and depression in young children, and they have far fewer side effects than antipsychotic drugs. Clinicians need to be vigilant about target symptoms and strive to clarify persistent irritability as seen in DMDD versus the more classic episodic irritability typical of bipolar spectrum disorders. Clinicians who prescribe antipsychotic drugs to children with bipolar disorder, NOS diagnoses will need to become familiar with the details of the current research on differentiating DMDD from bipolar disorder, NOS.
Prescriber Responsibilities for Antipsychotic Drugs for Children 8 Years of Age and Younger
If a child is 8 years of age or younger and requires an oral antipsychotic drug, the prescriber is required to complete the Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form. PA request forms must be faxed, mailed, or sent with the member to the pharmacy provider.
The pharmacy provider will use the completed form to submit a PA request to ForwardHealth. Prescribers should not submit the Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form directly to ForwardHealth. Prescribers are required to retain a completed and signed copy of the PA form.
PA requests for covered antipsychotic drugs for children 8 years of age and younger are approved at the active ingredient level. Therefore, an approved PA request allows any covered NDC with the same active ingredient of the prior authorized drug to be covered with the same PA. For example, if a member has an approved PA request for risperidone 1 mg tablets and the prescriber orders a new prescription for risperidone 2 mg tablets, an amended PA request or new PA request is not required.
Clinical Documentation
If the PA request for antipsychotic drugs for children 8 years of age and younger is for a member who is being treated for autism or tics, the only documentation required is the diagnosis information described in the following list. Pharmacy providers are encouraged to submit all PA requests for autism and tics using the STAT-PA system. The following clinical documentation is required on PA requests for members who are being treated for a condition other than autism or tics and must be submitted on the Portal, by fax, or by mail:
- Information about the child's diagnoses—There are appropriate indications for the use of antipsychotic drugs in young children with certain diagnoses, including autism spectrum disorders, psychotic disorders, and tic disorders. Antipsychotic drugs may also be helpful for severe symptoms of irritability, aggression, anger, or defiance that may accompany severe mood disorders, developmental disorders, or ADHD.
- BMI measurements—Antipsychotic drugs can have profoundly adverse effects on weight, glucose, and lipids. Because of these well-documented side effects, the Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form requires the submission of a BMI percentile measurement with each PA request. The BMI percentile measurement is required because it is the standard for stratifying individuals as obese or at-risk for obesity and, therefore, requiring closer monitoring and active intervention. Children who have a BMI percentile measurement greater than or equal to 85% are at risk for diabetes and the metabolic syndrome associated with many antipsychotic drugs. If the child's BMI percentile is 85% or greater, the PA request must include a triglyceride level and a fasting glucose or HBA1c drawn within the past six months for the PA request to be approved.
- Target symptoms—The prescriber is required to be very familiar with the criteria for DMDD and to clarify persistent versus episodic irritability/anxiety/anger/temper outbursts as well as to identify the presence, or absence, of comorbid conditions.
- Polypharmacy information—The Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form requires documentation of the child's experience with any psychoactive drugs, concurrent drugs, as well as previous drug trials in the preceding 12 months.
- Specialty information—ForwardHealth is interested in tracking the prescriber's practice specialty information.
- Documentation for non-preferred antipsychotic drug requests—If the prescriber is requesting a non-preferred antipsychotic drug, clinical documentation must be provided to support the request and must include detailed reasons why preferred drugs were discontinued or not utilized.
Pharmacy Responsibilities for Antipsychotic Drugs for Children 8 Years of Age and Younger
Pharmacy providers should ensure that they have received the completed Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form from the prescriber.
For BadgerCare Plus and Medicaid members, pharmacy providers should review the Preferred Drug List Quick Reference for the most current list of preferred and non-preferred drugs.
If a BadgerCare Plus or Medicaid member presents a prescription for a non-preferred antipsychotic drug, the pharmacy provider is encouraged to contact the prescriber to discuss preferred drug options. The prescriber may choose to change the prescription to a preferred antipsychotic drug if medically appropriate for the member.
It is important that pharmacy providers work with prescribers to ensure that members are given appropriate assistance regarding coverage information and the PA request submission process for antipsychotic drugs. Pharmacy providers are responsible for the submission of the Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form to ForwardHealth. Pharmacy providers are required to retain a completed and signed copy of the PA form.
Brand name antipsychotic drugs prescribed to children 8 years of age and younger that are BMN require that a Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form be submitted on the Portal, by fax, or by mail with the PA/BMNA form and the PA/RF.
Two unique PA numbers will be assigned for a BMN antipsychotic drug. One PA number will be assigned to the Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form, and the other will be assigned to the PA/BMNA form.
PA Request Submission Methods
Pharmacy providers are encouraged to use the STAT-PA system to submit PA requests for antipsychotic drugs for children who have one of the following conditions:
If the prescriber indicates on the Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form that the child has autism or tics, no additional clinical information is required on the form, and the pharmacy may submit the request using the STAT-PA system.
PA requests cannot be submitted using the STAT-PA system if any of the following are true:
- The child has a condition other than autism or tics.
- The drug being requested is a non-preferred antipsychotic drug.
- The child is 2 years of age or younger.
- The PA request is for a BMN antipsychotic drug.
If the PA request is not approved through the STAT-PA system, pharmacy providers are required to submit the Prior Authorization Drug Attachment for Antipsychotic Drugs for Children 8 Years of Age and Younger form, a PA/RF, and any supporting documentation from the prescriber on the Portal, by fax, or by mail.
Approved PA Requests for Antipsychotic Drugs for Children 8 Years of Age and Younger
Neither a new PA request nor a PA amendment is needed if the antipsychotic drug the child is taking has changed and the new drug contains the same active ingredient as the original drug approved or if the child is taking multiple strengths of the same drug.
PA decision notice letters for antipsychotic drugs for children 8 years of age and younger will include a message stating: "The prior authorization for this drug has been approved at the active ingredient level instead of the drug strength and dosage form level. Additional PAs are not needed for a different strength of this same drug."
Expedited Emergency Supply for Antipsychotic Drugs for Children 8 Years of Age and Younger
ForwardHealth strongly encourages pharmacy providers to utilize the expedited emergency supply process for antipsychotic drugs for children 8 years of age and younger when it is determined that the member should begin taking the medication immediately, but the PA request submission and adjudication process would delay dispensing the medication to the member. This may occur if a child 8 years of age or younger receives a prescription for an antipsychotic covered drug and the prescriber has not completed the necessary PA form or the PA request is still in process.
Expedited emergency supply requests for antipsychotic drugs will be approved for up to a 14-day supply. Members will be limited to receiving two 14-day expedited emergency supply approvals of the same drug from one pharmacy provider within a six-month time period. A PA is not required to be in process when the first expedited emergency supply request is submitted.
If a second expedited emergency supply is necessary for a member, there must be a PA request for the drug submitted to ForwardHealth, and it must be in the process of being adjudicated. The second expedited emergency supply request may be approved if a PA request is in process for the same drug and strength and the PA is submitted by the pharmacy that submitted the first expedited emergency supply request.
If a PA request for the drug has been approved, the second expedited emergency supply request will not be approved.
Requests for a second expedited emergency supply request may be submitted seven to 21 days after the initial request was submitted. Second expedited emergency supply requests will not be approved if they are submitted before day seven or after day 21.
For example, if an initial expedited emergency supply request was submitted on March 4 and a PA request for the drug was submitted on March 7 and a second expedited emergency supply is necessary for the member because the PA request had not yet been adjudicated, the second expedited emergency request may be submitted on March 10 or as late as March 24. Topic #22338 Bile Salts Drugs
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Bylvay, Cholbam, and Livmarli
PA requests for Bylvay, Cholbam, or Livmarli must be completed, signed, and dated by the prescriber. PA requests for Bylvay, Cholbam, or Livmarli must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Bylvay, Cholbam, or Livmarli may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
For information about general ForwardHealth PA policy for drugs that require PA approval, prescribers and pharmacy providers may refer to the Standard Pharmacy Policy for Covered and Noncovered Drugs topic. Providers may also refer to this topic for information about what may not be considered criteria to support the need for a drug.
Clinical Criteria for Bylvay and Livmarli
The clinical criteria for approval of a PA request for Bylvay or Livmarli are all of the following:
- The member's age must be consistent with FDA-approved product labeling for the drug requested.
- One of the following is true:
- The member has pruritus associated with PFIC.
- The member has cholestatic pruritus associated with ALGS.
Supporting clinical information and a copy of the member's current medical records must be submitted with the PA request to support the member's condition and outline the member's current treatment plan.
If the clinical criteria for Bylvay or Livmarli are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Bylvay and Livmarli may be approved for up to 365 days. Renewal PA requests must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant reduction in pruritus symptoms compared to the member's baseline prior to the initiation of the drug requested.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Cholbam
The clinical criteria for approval of a PA request for Cholbam are all of the following:
- The member's age must be consistent with FDA-approved product labeling for Cholbam.
- One of the following is true:
- The member has a bile acid synthesis disorder due to single enzyme defects.
- The member has a peroxisomal disorder (including Zellweger spectrum disorders) and exhibits manifestations of liver disease, steatorrhea, or complications from decreased fat-soluble vitamin absorption.
Supporting clinical information and a copy of the member's current medical records must be submitted with the PA request to support the member's condition and outline the member's current treatment plan. The member's baseline AST, ALT, GGT, alkaline phosphatase, bilirubin, and INR, prior to starting Cholbam, must be submitted with the initial PA request.
If the clinical criteria for Cholbam are met, initial PA requests may be approved for up to 90 days.
Renewal PA requests for Cholbam may be approved for up to 365 days. Renewal PA requests for Cholbam must include supporting clinical information and copies of the member's current medical records and lab work, including updated AST, ALT, GGT, alkaline phosphatase, bilirubin, and INR values, which demonstrate that the member's liver function has improved, compared to the member's baseline prior to the initiation of Cholbam.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #23257 Bone Resorption Suppression Drugs
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Bonsity and Teriparatide
Bonsity and teriparatide require clinical PA.
PA requests for Bonsity or teriparatide must be completed, signed, and dated by the prescriber. PA requests for Bonsity or teriparatide must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Bonsity or teriparatide may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Bonsity and Teriparatide
The clinical criteria that must be documented for approval of a PA request for Bonsity or teriparatide includes both of the following:
- The prescriber has submitted detailed clinical justification for prescribing Bonsity or teriparatide instead of Forteo.
- The clinical information must document why the member cannot use Forteo including why it is medically necessary that the member receive Bonsity or teriparatide instead of Forteo.
Clinical documentation and medical records must be submitted with the PA request to support the need for teriparatide. PA requests for Bonsity or teriparatide may be approved for up to 365 days. Topic #22717 BPH Agents, Alpha Reductase Inhibitors
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Finasteride/Tadalafil
Finasteride/tadalafil requires clinical PA.
PA requests for finasteride/tadalafil must be completed, signed, and dated by the prescriber. PA requests for finasteride/tadalafil must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for finasteride/tadalafil may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Finasteride/Tadalafil
Clinical criteria that must be documented for approval of a PA request for finasteride/tadalafil are all of the following:
- The member has BPH with lower urinary tract symptoms.
- The member has taken dutasteride and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken finasteride for at least two consecutive months and experienced a partial response.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for finasteride/tadalafil. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for finasteride/tadalafil are met, PA requests may be approved for up to 182 days (26 weeks).
ForwardHealth allows only one finasteride/tadalafil PA approval during a member's lifetime. Additional PA requests will not be approved. Topic #16217 Cytokine and Cell Adhesion Molecule Antagonist Drugs
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Clinical PA is required for non-preferred cytokine and CAM antagonist drugs.
PA requests for non-preferred cytokine and CAM antagonist drugs will only be approved for use to treat these identified clinical conditions:
- Alopecia areata
- Ankylosing spondylitis
- Crohn's disease
- DIRA
- ERA
- Giant cell arteritis
- GPP
- Hidradenitis suppurativa
- JIA and systemic JIA
- NMOSD
- NOMID
- nr-axSpA
- Oral ulcers associated with Behcet's disease
- PMR
- Psoriasis
- Psoriatic arthritis
- RA
- SSc-ILD
- Ulcerative colitis
- Uveitis
PA requests for cytokine and CAM antagonist drugs will only be approved for one cytokine and CAM antagonist drug per member. ForwardHealth does not cover treatment with more than one cytokine and CAM antagonist drug.
PA requests will not be considered for subcutaneous dosage forms of cytokine and CAM antagonist drugs that will be administered in a medical office or medical facility.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for non-preferred cytokine and CAM antagonist drugs. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
Initial PA requests for non-preferred cytokine and CAM antagonist drugs may be approved for up to 183 days.
Renewal PA requests for non-preferred cytokine and CAM antagonist drugs may be approved for up to 365 days. Renewal PA requests for non-preferred cytokine and CAM antagonist drugs must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant reduction in symptoms compared to their baseline prior to the initiation of the non-preferred cytokine and CAM antagonist drug.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Cytokine and Cell Adhesion Molecule Antagonist Biosimilar Drugs
All cytokine and CAM antagonist biosimilar drugs will be added to the cytokine and CAM antagonist drug class as non-preferred drugs (unless specifically identified or noted) until the next scheduled drug class review by the Wisconsin Medicaid Pharmacy PA Committee. The cytokine and CAM antagonists drug class is typically reviewed at the November PDL review each year.
ForwardHealth will use a blanket "xxxx" placeholder after the biosimilar generic name when referring to non-preferred biosimilar drug products in the clinical PA criteria for the appropriate clinical condition. The Preferred Drug List Quick Reference data table will list the brand names with the complete generic names of the biosimilar drug products in the cytokine and CAM antagonists drug class.
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Alopecia Areata
Leqselvi, Litfulo, and Olumiant are non-preferred drugs used to treat alopecia areata.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat alopecia areata are both of the following:
- The member has severe alopecia areata with at least 50% scalp hair loss (SALT score of greater than or equal to 50). The member's SALT score must be documented.
- The prescription is written by a dermatologist or through a dermatology consultation.
Clinical documentation and medical records must be submitted with the PA request to support the member's condition of alopecia areata and outline the member's current treatment plan for alopecia areata.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Alopecia Areata
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat alopecia areata must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests used to treat alopecia areata may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Ankylosing Spondylitis
Cimzia, Enbrel, Hadlima, Humira, Simponi subQ, Taltz, Xeljanz, and Xeljanz XR are preferred drugs used to treat ankylosing spondylitis. Preferred drugs do not require PA.
Adalimumab-xxxx, Bimzelx, Cosentyx subQ, and Rinvoq are non-preferred drugs used to treat ankylosing spondylitis.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat ankylosing spondylitis are all of the following:
- The member has ankylosing spondylitis.
- The prescription is written by a rheumatologist or through a rheumatology cons
ultation.
- The member has taken two preferred cytokine and CAM antagonist drugs for at least three consecutive months each and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction. Note: ForwardHealth will only consider use of:
- Hadlima or Humira as one trial.
- Xeljanz or Xeljanz XR as one trial.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Non-Preferred Adalimumab-xxxx Drugs
The prescriber must submit detailed clinical justification for prescribing a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira. The clinical information must document why the member cannot use Hadlima and Humira, including why it is medically necessary that the member receive a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Ankylosing Spondylitis
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat ankylosing spondylitis must be submitted using the Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Ankylosing Spondylitis form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Ankylosing Spondylitis form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat ankylosing spondylitis may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Crohn's Disease
Cimzia, Hadlima, Humira, Selarsdi subQ, and Steqeyma subQ are preferred drugs used to treat Crohn's disease. Preferred drugs do not require PA.
Adalimumab-xxxx, Entyvio subQ, Omvoh subQ, Rinvoq, Skyrizi subQ, Stelara subQ, Tremfya subQ, ustekinumab-xxxx subQ, and Zymfentra are non-preferred drugs used to treat Crohn's disease.
Note: Omvoh and Skyrizi will require an IV induction prior to initiating treatment with the subQ. A PA request for the IV induction must be approved before ForwardHealth will consider PA for the subQ. PA for the IV induction may be obtained through the physician-administered drug PA process. An IV induction for Tremfya is optional prior to initiating treatment with the subQ.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat Crohn's disease are all of the following:
- The member has Crohn's disease.
- The prescription is written by a gastroenterologist or through a gastroenterology consultation.
- The member has taken two preferred cytokine and CAM antagonist drug for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction. Note: ForwardHealth will only consider use of:
- Hadlima or Humira as one trial.
- Selarsdi subQ or Steqeyma subQ as one trial.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Non-Preferred Adalimumab-xxxx Drugs
The prescriber must submit detailed clinical justification for prescribing a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira. The clinical information must document why the member cannot use Hadlima and Humira, including why it is medically necessary that the member receive a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira.
Stelara SubQ and Non-Preferred Ustekinumab-xxxx SubQ Drugs
The prescriber must submit detailed clinical justification for prescribing Stelara subQ or a non-preferred ustekinumab-xxxx subQ drug instead of Selarsdi subQ and Steqeyma subQ. The clinical information must document why the member cannot use Selarsdi subQ and Steqeyma subQ, including why it is medically necessary that the member receive Stelara subQ or a non-preferred ustekinumab-xxxx subQ drug instead of Selarsdi subQ and Steqeyma subQ.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Crohn's Disease
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat Crohn's disease must be submitted using the Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Crohn's Disease and Ulcerative Colitis form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Crohn's Disease and Ulcerative Colitis form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat Crohn's disease may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Deficiency of Interleukin-1 Receptor Antagonist
Kineret is a non-preferred drug used to treat DIRA.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat DIRA are both of the following:
- The member has DIRA.
- The prescription is written by or through consultation with a DIRA specialist (for example, an immunologist or a rheumatologist).
Clinical documentation and medical records must be submitted with the PA request to support the member's condition of DIRA and outline the member's current treatment plan for DIRA.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Deficiency of Interleukin-1 Receptor Antagonist
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat DIRA must be submitted using PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests used to treat DIRA may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Enthesitis-Related Arthritis
Cosentyx subQ is a non-preferred drug used to treat ERA.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat ERA are both of the following:
- The member has ERA.
- The prescription is written by a rheumatologist or through a rheumatology consultation.
Clinical documentation and medical records must be submitted with the PA request to support the member's condition of ERA and outline the member's current treatment plan for ERA.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Enthesitis-Related Arthritis
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat ERA must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat ERA may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system.)
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Giant Cell Arteritis
Tyenne subQ is a preferred drug used to treat giant cell arteritis. Preferred drugs do not require PA.
Actemra subQ, Rinvoq, and tocilizumab-xxxx subQ are non-preferred drugs used to treat giant cell arteritis.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat giant cell arteritis are all of the following:
- The member has giant cell arteritis.
- The prescription is written by a rheumatologist or through a rheumatology consultation.
- The member has taken Tyenne subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Giant Cell Arteritis
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat giant cell arteritis must be submitted using Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Giant Cell Arteritis and nr-axSpA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Giant Cell Arteritis and nr-axSpA form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat giant cell arteritis may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Non-Preferred Cytokine and Cell Adhesion Molecule Antagonist Drugs for Generalized Pustular Psoriasis
Spevigo subQ is a non-preferred drug used to treat GPP.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat GPP are all of the following:
- The member has GPP.
- The prescription is written by a dermatologist or through a dermatology consultation.
Clinical documentation and medical records must be submitted with the PA request to support the member's clinical condition of GPP and outline the member's current treatment plan for GPP.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Generalized Pustular Psoriasis
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat GPP must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat GPP may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Additional Dosage Form for Spevigo
The intravenous dosage form of Spevigo is a physician-administered drug, and it uses HCPCS procedure code J1747 (Injection, spesolimab-sbzo, 1 mg). HCPCS code J1747 will also have a diagnosis restriction of L40.1 for GPP.
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Hidradenitis Suppurativa
Hadlima and Humira are preferred drugs used to treat hidradenitis suppurativa. Preferred drugs do not require PA.
Adalimumab-xxxx, Bimzelx, and Cosentyx subQ are non-preferred drugs used to treat hidradenitis suppurativa.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat hidradenitis suppurativa are all of the following:
- The member has hidradenitis suppurativa.
- The prescription is written by a dermatologist or through a dermatology consultation.
- The member has taken one preferred cytokine and CAM antagonist drug for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Non-Preferred Adalimumab-xxxx Drugs
The prescriber must submit detailed clinical justification for prescribing a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira. The clinical information must document why the member cannot use Hadlima and Humira, including why it is medically necessary that the member receive a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Hidradenitis Suppurativa
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat hidradenitis suppurativa must be submitted using the Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Hidradenitis Suppurativa form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Hidradenitis Suppurativa form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat hidradenitis suppurativa may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Neuromyelitis Optica Spectrum Disorder
Enspryng is a non-preferred drug used to treat NMOSD.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat NMOSD are all of the following:
- The member has NMOSD.
- The prescription is written by a neurologist or through a neurology consultation.
- The member is anti-aquaporin-4 antibody positive.
Clinical documentation and medical records must be submitted with the PA request to support the member's clinical condition of NMOSD and outline the member's current treatment plan for NMOSD.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Neuromyelitis Optica Spectrum Disorder
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat NMOSD must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat NMOSD may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system.)
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Neonatal Onset Multisystem Inflammatory Disease
Kineret is a non-preferred drug used to treat NOMID.
Clinical criteria for approval of a PA request for Kineret used to treat NOMID are both of the following:
- The member has NOMID.
- The prescription is written by a rheumatologist or through a rheumatology consultation.
Clinical documentation and medical records must be submitted with the PA request to support the member's condition of NOMID and outline the member's current treatment plan for NOMID.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Neonatal Onset Multisystem Inflammatory Disease
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat NOMID must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Kineret used to treat NOMID may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Non-Radiographic Axial Spondyloarthritis
Cimzia and Taltz are preferred drugs used to treat nr-axSpA. Preferred drugs do not require PA.
Bimzelx, Cosentyx subQ, and Rinvoq are non-preferred drugs used to treat nr-axSpA.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat nr-axSpA are all of the following:
- The member has nr-axSpA.
- The prescription is written by a rheumatologist or through a rheumatology consultation.
- The member has taken two preferred cytokine and CAM antagonist drugs at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Non-Radiographic Axial Spondyloarthritis
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat nr-axSpA must be submitted using the Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Giant Cell Arteritis and nr-axSpA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Giant Cell Arteritis and nr-axSpA form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat nr-axSpA may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Oral Ulcers Associated With Behcet's Disease
Otezla is a preferred drug used to treat oral ulcers associated with Behcet's disease. Preferred drugs do not require PA.
Otezla XR is a non-preferred drug used to treat oral ulcers associated with Behcet's disease.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat oral ulcers associated with Behcet's disease are all of the following:
- The member has oral ulcers associated with Behcet's disease.
- The prescription is written by a rheumatologist or through a rheumatology consultation.
- The member has taken one preferred cytokine and CAM antagonist drug for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Otezla XR
The prescriber must submit detailed clinical justification for prescribing Otezla XR instead of Otezla. The clinical information must document why the member cannot use Otezla, including why it is medically necessary that the member receive Otezla XR instead of Otezla.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Oral Ulcers Associated With Behcet's Disease
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat oral ulcers associated with Behcet's disease must be submitted using the Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Oral Ulcers Associated With Behcet's Disease and Uveitis form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Oral Ulcers Associated With Behcet's Disease and Uveitis form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat oral ulcers associated with Behcet's disease may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Polymyalgia Rheumatica
Kevzara is a non-preferred drug used to treat PMR.
Clinical criteria for approval of a PA request for non-preferred drugs used to treat PMR are all of the following:
- The member has PMR.
- The prescription is written by or through consultation with a PMR specialist.
- The member has taken corticosteroids and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
Clinical documentation and medical records must be submitted with the PA request to support the member's condition of PMR and outline the member's current treatment plan for PMR.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Polymyalgia Rheumatica
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat PMR must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat PMR may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Psoriasis
Cimzia, Enbrel, Hadlima, Humira, Otezla, Selarsdi subQ, Steqeyma subQ, and Taltz are preferred drugs used to treat psoriasis. Preferred drugs do not require PA.
Adalimumab-xxxx, Bimzelx, Cosentyx subQ, Icotyde, Otezla XR, Skyrizi subQ, Sotyktu, Stelara subQ, Tremfya, and ustekinumab-xxxx subQ are non-preferred drugs used to treat psoriasis.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat psoriasis are all of the following:
- The member has psoriasis.
- The prescription is written by a dermatologist or through a dermatology consultation.
- The member has taken two preferred cytokine and CAM antagonist drugs for at least three consecutive months each and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction. Note: ForwardHealth will only consider use of
- Hadlima or Humira as one trial.
- Selarsdi subQ or Steqeyma subQ as one trial.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Non-Preferred Adalimumab-xxxx Drugs
The prescriber must submit detailed clinical justification for prescribing a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira. The clinical information must document why the member cannot use Hadlima and Humira, including why it is medically necessary that the member receive a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira.
Stelara SubQ and Non-Preferred Ustekinumab-xxxx SubQ Drugs
The prescriber must submit detailed clinical justification for prescribing Stelara subQ or a non-preferred ustekinumab-xxxx subQ drug instead of Selarsdi subQ and Steqeyma subQ. The clinical information must document why the member cannot use Selarsdi subQ and Steqeyma subQ, including why it is medically necessary that the member receive Stelara subQ or a non-preferred ustekinumab-xxxx subQ drug instead of Selarsdi subQ and Steqeyma subQ.
Otezla XR
The prescriber must submit detailed clinical justification for prescribing Otezla XR instead of Otezla. The clinical information must document why the member cannot use Otezla, including why it is medically necessary that the member receive Otezla XR instead of Otezla.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Psoriasis
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat psoriasis must be submitted using the Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Psoriasis form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Psoriasis form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat psoriasis may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Psoriatic Arthritis
Cimzia, Enbrel, Hadlima, Humira, Orencia subQ, Otezla, Selarsdi subQ, Simponi subQ, Steqeyma subQ, Taltz, Xeljanz and Xeljanz XR are preferred drugs used to treat psoriatic arthritis. Preferred drugs do not require PA.
Adalimumab-xxxx, Bimzelx, Cosentyx subQ, Otezla XR, Rinvoq, Rinvoq LQ, Skyrizi subQ, Sotyktu, Stelara subQ, Tremfya subQ, and ustekinumab-xxxx subQ are non-preferred drugs used to treat psoriatic arthritis.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat psoriatic arthritis are all of the following:
- The member has psoriatic arthritis.
- The prescription is written by a dermatologist or rheumatologist or through a dermatology or rheumatology consultation.
- The member has taken two preferred cytokine and CAM antagonist drugs for at least three consecutive months each and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction. Note: ForwardHealth will only consider use of
- Hadlima or Humira as one trial.
- Selarsdi subQ or Steqeyma subQ as one trial.
- Xeljanz or Xeljanz XR as one trial.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Non-Preferred Adalimumab-xxxx Drugs
The prescriber must submit detailed clinical justification for prescribing a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira. The clinical information must document why the member cannot use Hadlima and Humira, including why it is medically necessary that the member receive a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira.
Stelara SubQ and Non-Preferred Ustekinumab-xxxx SubQ Drugs
The prescriber must submit detailed clinical justification for prescribing Stelara subQ or a non-preferred ustekinumab-xxxx subQ drug instead of Selarsdi subQ and Steqeyma subQ. The clinical information must document why the member cannot use Selarsdi subQ and Steqeyma subQ, including why it is medically necessary that the member receive Stelara subQ or a non-preferred ustekinumab-xxxx subQ drug instead of Selarsdi subQ and Steqeyma subQ.
Otezla XR
The prescriber must submit detailed clinical justification for prescribing Otezla XR instead of Otezla. The clinical information must document why the member cannot use Otezla, including why it is medically necessary that the member receive Otezla XR instead of Otezla.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Psoriatic Arthritis
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat psoriatic arthritis must be submitted using the Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for RA, JIA, and Psoriatic Arthritis form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for RA, JIA, and Psoriatic Arthritis form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat psoriatic arthritis may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Rheumatoid Arthritis
Cimzia, Enbrel, Hadlima, Humira, Orencia subQ, Simponi subQ, Tyenne subQ, Xeljanz, and Xeljanz XR are preferred drugs used to treat RA. Preferred drugs do not require PA.
Actemra subQ, adalimumab-xxxx, Kevzara, Kineret, Olumiant, Rinvoq, and tocilizumab-xxxx subQ are non-preferred drugs used to treat RA.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat RA are all of the following:
- The member has RA.
- The prescription is written by a rheumatologist or through a rheumatology consultation.
- The member has taken two preferred cytokine and CAM antagonist drugs for at least three consecutive months each and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction. Note: ForwardHealth will only consider use of
- Hadlima or Humira as one trial.
- Xeljanz or Xeljanz XR as one trial.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Non-Preferred Adalimumab-xxxx Drugs
The prescriber must submit detailed clinical justification for prescribing a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira. The clinical information must document why the member cannot use Hadlima and Humira, including why it is medically necessary that the member receive a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Rheumatoid Arthritis
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat RA must be submitted using the Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for RA, JIA, and Psoriatic Arthritis form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for RA, JIA, and Psoriatic Arthritis form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat RA may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Juvenile Idiopathic Arthritis
Cimziz, Enbrel, Hadlima, Humira, Orencia subQ, Tyenne subQ, Xeljanz, and Xeljanz Oral Solution are preferred drugs used to treat JIA. Preferred drugs do not require PA.
Actemra subQ, adalimumab-xxxx, Kevzara, Rinvoq LQ, and tocilizumab-xxxx subQ are non-preferred drugs used to treat JIA.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat JIA are all of the following:
- The member has JIA.
- The prescription is written by a rheumatologist or through a rheumatology consultation.
- The member has taken two preferred cytokine and CAM antagonist drugs for at least three consecutive months each and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction. Note: ForwardHealth will only consider use of
- Hadlima or Humira as one trial.
- Xeljanz or Xeljanz Oral Solution as one trial.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Non-Preferred Adalimumab-xxxx Drugs
The prescriber must submit detailed clinical justification for prescribing a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira. The clinical information must document why the member cannot use Hadlima and Humira, including why it is medically necessary that the member receive a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira.
Clinical Criteria for Systemic Juvenile Idiopathic Arthritis
Tyenne subQ is a preferred drug used to treat systemic JIA. Preferred drugs do not require PA.
Actemra subQ and tocilizumab-xxxx subQ are non-preferred drugs used to treat systemic JIA.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat systemic JIA are all of the following:
- The member has systemic JIA.
- The prescription is written by a rheumatologist or through a rheumatology consultation.
- The member has taken Tyenne subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Juvenile Idiopathic Arthritis and Systemic Juvenile Idiopathic Arthritis
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat JIA and systemic JIA must be submitted using the Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for RA, JIA, and Psoriatic Arthritis form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for RA, JIA, and Psoriatic Arthritis form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat JIA and systemic JIA may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Systemic Sclerosis-Associated Interstitial Lung Disease
Actemra subQ is a non-preferred drug used to treat SSc-ILD.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat SSc-ILD are both of the following:
- The member has SSc-ILD.
- The prescription is written by or through consultation with an SSc-ILD specialist.
Clinical documentation and medical records must be submitted with the PA request to support the member's condition of SSc-ILD and outline the member's current treatment plan for SSc-ILD.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Systemic Sclerosis-Associated Interstitial Lung Disease
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat SSc-ILD must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat SSc-ILD may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system.)
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Ulcerative Colitis
Humira, Hadlima, Selarsdi subQ, Simponi subQ, Steqeyma subQ, Xeljanz, and Xeljanz XR are preferred drugs used to treat ulcerative colitis. Preferred drugs do not require PA.
Adalimumab-xxxx, Entyvio subQ, Omvoh subQ, Rinvoq, Skyrizi subQ, Stelara subQ, Tremfya subQ, ustekinumab-xxxx subQ, and Zymfentra are non-preferred drugs used to treat ulcerative colitis.
Note: Omvoh and Skyrizi will require an IV induction prior to initiating treatment with the subQ. A PA request for the IV induction must be approved before ForwardHealth will consider PA for the subQ. PA for the IV induction may be obtained through the physician-administered drug PA process. An IV induction for Tremfya is optional prior to initiating treatment with the subQ.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat ulcerative colitis are all of the following:
- The member has ulcerative colitis.
- The prescription is written by a gastroenterologist or through a gastroenterology consultation.
- The member has taken two preferred cytokine and CAM antagonist drugs for at least three consecutive months each and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction. Note: ForwardHealth will only consider use of
- Hadlima or Humira as one trial.
- Selarsdi subQ or Steqeyma subQ as one trial.
- Xeljanz or Xeljanz XR as one trial.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Non-Preferred Adalimumab-xxxx Drugs
The prescriber must submit detailed clinical justification for prescribing a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira. The clinical information must document why the member cannot use Hadlima and Humira, including why it is medically necessary that the member receive a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira.
Stelara SubQ and Non-Preferred Ustekinumab-xxxx SubQ Drugs
The prescriber must submit detailed clinical justification for prescribing Stelara subQ or a non-preferred ustekinumab-xxxx subQ drug instead of Selarsdi subQ and Steqeyma subQ. The clinical information must document why the member cannot use Selarsdi subQ and Steqeyma subQ, including why it is medically necessary that the member receive Stelara subQ or a non-preferred ustekinumab-xxxx subQ drug instead of Selarsdi subQ and Steqeyma subQ.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Ulcerative Colitis
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat ulcerative colitis must be submitted using the Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Crohn's Disease and Ulcerative Colitis form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Crohn's Disease and Ulcerative Colitis form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat ulcerative colitis may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Uveitis
Hadlima and Humira are preferred drugs used to treat uveitis. Preferred drugs do not require PA.
Adalimumab-xxxx is a non-preferred drug used to treat uveitis.
Clinical criteria for approval of a PA request for non-preferred cytokine and CAM antagonist drugs used to treat uveitis are all of the following:
- The member has uveitis.
- The prescription is written by an ophthalmologist or through an ophthalmology consultation.
- The member has taken one preferred cytokine and CAM antagonist drug for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why a non-preferred cytokine and CAM antagonist drug is being requested.
Non-Preferred Adalimumab-xxxx Drugs
The prescriber must submit detailed clinical justification for prescribing a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira. The clinical information must document why the member cannot use Hadlima and Humira, including why it is medically necessary that the member receive a non-preferred adalimumab-xxxx drug instead of Hadlima and Humira.
Submitting PA Requests for Cytokine and Cell Adhesion Molecule Antagonist Drugs for Uveitis
PA requests for non-preferred cytokine and CAM antagonist drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred cytokine and CAM antagonist drugs used to treat uveitis must be submitted using the Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Oral Ulcers Associated With Behcet's Disease and Uveitis form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Cytokine and CAM Antagonist Drugs for Oral Ulcers Associated With Behcet's Disease and Uveitis form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred cytokine and CAM antagonist drugs used to treat uveitis may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system). Topic #23099 Erythropoiesis Stimulating Proteins
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Jesduvroq and Vafseo
Jesduvroq and Vafseo require clinical PA.
PA requests for Jesduvroq or Vafseo must be completed, signed, and dated by the prescriber. PA requests for Jesduvroq or Vafseo must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Jesduvroq or Vafseo may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Jesduvroq and Vafseo
The clinical criteria for approval of a PA request for Jesduvroq or Vafseo are all of the following:
- The member has anemia due to chronic kidney disease.
- One of the following is true:
- The member has been receiving dialysis for at least the previous four months and will continue to receive dialysis during treatment with Jesduvroq.
- The member has been receiving dialysis for at least the previous three months and will continue to receive dialysis during treatment with Vafseo.
- The member does not have uncontrolled hypertension.
- The member has taken two preferred erythropoiesis stimulating proteins and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why Jesduvroq or Vafseo is being requested.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Jesduvroq or Vafseo. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
Initial and Renewal PA Requests for Jesduvroq and Vafseo
If the clinical criteria for Jesduvroq and Vafseo are met, initial PA requests may be approved for up to 183 days. Renewal PA requests may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #20617 Glucocorticoids, Oral
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Agamree, Emflaza, Jaythari, Kymbee, and Pyquvi
Clinical PA is required for Agamree, Emflaza, Jaythari, Kymbee, and Pyquvi.
PA requests for Agamree, Emflaza, Jaythari, Kymbee, or Pyquvi must be completed, signed, and dated by the prescriber. PA requests for Agamree, Emflaza, Jaythari, Kymbee, or Pyquvi must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Agamree, Emflaza, Jaythari, Kymbee, or Pyquvi may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Agamree, Emflaza, Jaythari, Kymbee, and Pyquvi
Clinical criteria that must be documented for approval of a PA request for Agamree, Emflaza, Jaythari, Kymbee, or Pyquvi are all of the following:
- The member has a diagnosis of DMD.
- The member's age must be consistent with FDA-approved product labeling.
- The prescription is written by or through consultation with a neurologist.
- The member has experienced a clinically significant glucocorticoid adverse drug reaction with an adequate trial of prednisone that has required a dose reduction or discontinuation of prednisone.
Additional Clinical Criteria for Jaythari, Kymbee, and Pyquvi
The prescriber must submit detailed clinical justification for prescribing Jaythari, Kymbee, or Pyquvi instead of Emflaza. The clinical information must document why the member cannot use Emflaza, including why it is medically necessary that the member receives Jaythari, Kymbee, or Pyquvi instead of Emflaza.
Supporting Clinical Information for Agamree, Emflaza, Jaythari, Kymbee, and Pyquvi
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Agamree, Emflaza, Jaythari, Kymbee, or Pyquvi. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If clinical criteria for Agamree, Emflaza, Jaythari, Kymbee, or Pyquvi are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Agamree, Emflaza, Jaythari, Kymbee, or Pyquvi may be approved for up to 365 days. Renewal PA requests for members who have DMD must include supporting clinical information and copies of the member's current medical records demonstrating that the member has experienced an improvement or resolution of the initial glucocorticoid adverse effects experienced with prednisone.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #1988 Growth Hormone Drugs
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
All growth hormone prescriptions must be written by an endocrinologist or through an endocrinology consultation, except prescriptions written for Serostim.
Note: ForwardHealth will consider the entire clinical record for the PA request determination decision.
Non-Preferred Growth Hormone Drugs
The following will not be considered as clinical criteria to support the need for a non-preferred growth hormone drug:
- Nonadherence to previous growth hormone treatment
- The member's fear of needles
- The member's or prescriber's preference for the use of a non-preferred growth hormone drug
- The member's or prescriber's preference for a less frequent dosing schedule
PA requests for the following growth hormone drugs must be submitted on the PA/PDL for Growth Hormone Drugs form:
- Serostim
- Growth hormone drugs for children and adolescents
- Growth hormone drugs for adults
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/PDL for Growth Hormone Drugs form and a completed PA/RF to ForwardHealth.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Serostim
ForwardHealth covers Serostim for members with AIDS wasting disease or cachexia.
If clinical criteria for Serostim are met, initial PA requests for Serostim may be approved for up to 365 days. PA requests for Serostim must be submitted on the PA/PDL for Growth Hormone Drugs form and may be submitted to ForwardHealth using the STAT-PA system, on the Portal, by fax, or by mail.
Clinical Criteria for Growth Hormone Drug Coverage for Children and Adolescents
ForwardHealth covers growth hormone drugs for children and adolescents when prescribed in a manner consistent with FDA-approved product labeling for the following indications:
- The member has a history of panhypopituitarism involving at least two pituitary hormone deficiencies, not including growth hormone, and a history of hypothalamic-pituitary structural lesion(s).
- The member has a history of cranial irradiation, tumor, or other structural midline lesion, in addition to a decreasing growth velocity and a low IGF-1 measurement below the age- and gender-specific lower limit of normal with normal thyroid function and adequate nutrition.
- The member has growth failure or short stature associated with one of the following congenital conditions that have an FDA-approved indication for growth hormone use:
- Noonan syndrome
- Prader-Willi syndrome
- SHOX gene deficiency disorder
- Turner syndrome
- The member has growth failure or short stature associated with chronic renal insufficiency in pre-kidney transplant members.
- The member is born SGA in addition to being at least 24 months-old with a height that remains more than two standard deviations below the mean for chronological age and gender on a clinically appropriate growth chart. SGA is defined as infants with a birth weight and/or height below the 10th percentile for gestational age. Other causes for short stature must have been excluded, such as growth inhibiting medication, chronic disease, thyroid disease, or under-nutrition. ForwardHealth will consider the entire clinical record for the PA request determination decision.
- The member has growth failure or short stature for children and adolescents with growth hormone deficiency including all of the following:
- The member's height is more than two standard deviations below the mean for chronological age and gender on a clinically appropriate growth chart.
- Other causes for short stature must have been excluded, such as growth inhibiting medication, chronic disease, other congenital conditions, thyroid disease, or under-nutrition. If IGF-1 levels are low, IGFBP-3 testing should be considered, and under-nutrition should be evaluated and addressed before proceeding with growth hormone stimulation testing. If the results of the IGF-1/IGFBP-3 and bone age are normal, best clinical practice would indicate growth hormone stimulation testing is not necessary since growth hormone deficiency can effectively be excluded without the need for further testing due to recognized limitations of growth hormone stimulation testing and risk of false positive results.
- The member has failed to respond to at least two validated growth hormone stimulation tests performed using a well-standardized protocol, demonstrating a growth hormone peak response of less than 10 ng/mL after stimulation with a pharmacologic agent such as insulin, arginine, clonidine, or glucagon.
Growth Hormone Stimulation Testing Requirements for Children and Adolescents
Growth hormone stimulation testing should be conducted after an overnight fast, using a well-standardized protocol, and should be conducted for the appropriate duration of time specific to the agents used to ensure the peak growth hormone level is captured. Both stimulation tests can be administered the same day.
When growth hormone stimulation testing has been performed, complete testing results must be submitted with the PA request, including the following:
- Confirmation that the member was fasting
- The type of stimulation test and the dose of stimulating agent
- A copy of the medical notes taken during the entire testing procedure, including vital signs and blood glucose levels
- The time and results from each blood sample taken
- The provider interpretation of the testing results
For members with thyroid deficiency, ForwardHealth only accepts results of the growth hormone stimulation tests that are performed after thyroid deficiency is adequately treated because growth hormone secretion may be subnormal merely as a result of hypothyroidism.
Growth hormone stimulation testing performed in a non-validated or sub-standard manner will not be considered by ForwardHealth to be an acceptable growth hormone stimulation test.
Growth hormone testing can provide useful information, but due to the recognized limitations of growth hormone stimulation testing and the risk of false positive results, ForwardHealth will consider the results of the growth hormone stimulation testing in the context of the entire clinical record for the PA request determination decision.
Documentation Requirements for PA Requests for Growth Hormone for Children and Adolescents
Detailed documentation of the medical work-up and testing used to determine the need for growth hormone treatment must be submitted with the PA request, including the following:
- Detailed endocrinology and medical work-up, including medical problem list, current medication list, and medication history
- Height and weight measurements over time plotted on the most clinically appropriate growth chart(s) for age and gender, including growth velocity, growth percentiles, and Z-scores
- Copies of the member's gestational age, weight at birth, and length at birth (if required)
- Copies of the most recent IGF-1 and IGFBP-3 lab reports
- Bone age results
- TSH level
- Nutritional assessment
- Any other relevant testing, such as advanced imaging of the hypothalamic-pituitary region, if performed
PA requests for growth hormone drugs for children and adolescents must be submitted on the PA/PDL for Growth Hormone Drugs form. PA requests for growth hormone drugs for children and adolescents may be submitted using the STAT-PA system when the member meets both of the following:
- The member has growth failure or short stature associated with one of the following congenital conditions:
- Noonan syndrome
- Prader-Willi syndrome
- SHOX gene deficiency disorder
- Turner syndrome
- The member is younger than 14 years of age.
All other PA requests for preferred or non-preferred growth hormone drugs for children and adolescents may be submitted on the Portal, by fax, or by mail, but not using the STAT-PA system.
If the clinical criteria for growth hormone drugs for children and adolescents are met, initial PA requests may be approved for up to 183 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. A copy of the current endocrinology clinic notes, including clinically appropriate height and weight growth charts for age and gender, the most current IGF-1 and/or IGFBP-3 lab testing results, growth velocity, and the most current bone age report, must be included with the PA request. Renewal PA requests may be approved for up to 365 days.
Conditions Not Covered for Growth Hormone Treatment for Children and Adolescents
ForwardHealth does not cover growth hormone treatment for the following conditions or circumstances:
- The member has closed epiphyses.
- Growth velocity is less than 2 cm/year while on growth hormone treatment, or growth velocity does not demonstrate a significant increase while on growth hormone treatment.
- Mid-parental height is achieved using the following equation.
Mid-parental height = (father's height + mother's height) ÷ 2, + 2.5 inches (male) or - 2.5 inches (female)
- The member is not compliant with the prescribed growth hormone therapy.
- The member has idiopathic short stature, which is a growth failure or short stature not associated with growth hormone deficiency or disease state.
- The member is post kidney transplant.
Clinical Criteria for Growth Hormone Drug Coverage for Adults
ForwardHealth covers growth hormone drugs for adults when prescribed in a manner consistent with FDA-approved product labeling for the following indications:
- The member has a history of panhypopituitarism during childhood involving at least two other pituitary hormone deficiencies, not including growth hormone, and treatment with a growth hormone drug during childhood.
- The member has a history of hypopituitarism during childhood involving at least one other pituitary hormone deficiency, not including growth hormone, and treatment with a growth hormone drug during childhood. The diagnosis of growth hormone deficiency must be confirmed with an IGF-1 measurement below the age- and gender-specific lower limit of normal after stopping growth hormone for at least three months and at least one standard appropriate growth hormone stimulation test demonstrating a growth hormone peak response of less than the established adult reference values of the specific stimulation tests performed.
- The member has a history of treatment with a growth hormone drug during childhood without evidence of other pituitary hormone deficiencies. The diagnosis of growth hormone deficiency must be confirmed with an IGF-1 measurement below the age- and gender-specific lower limit of normal after stopping growth hormone treatment for at least three months and at least two standard appropriate growth hormone stimulation tests demonstrating a growth hormone peak response of less than the established adult reference values of the specific stimulation tests performed.
- The member has a history of a head injury, hypothalamic-pituitary structural lesion(s), or cranial irradiation and evidence of panhypopituitarism involving at least three other pituitary hormone deficiencies, not including growth hormone.
- The member has a history of a head injury, hypothalamic-pituitary structural lesion(s), or cranial irradiation and evidence of hypopituitarism with at least one other pituitary hormone deficiency, not including growth hormone. Growth hormone deficiency must be confirmed with an IGF-1 measurement below the age- and gender-specific lower limit of normal and at least one standard appropriate growth hormone stimulation test demonstrating a growth hormone peak response of less than the established adult reference values of the specific stimulation tests performed.
- The member has a history of a head injury, hypothalamic-pituitary structural lesion(s), or cranial irradiation without evidence of other pituitary hormone deficiencies. Growth hormone deficiency must be confirmed with an IGF-1 measurement below the age- and gender-specific lower limit of normal and at least two standard appropriate growth hormone stimulation tests demonstrating a growth hormone peak response of less than the established adult reference values of the specific stimulation tests performed.
Note: For individuals being treated for growth hormone deficiency due to trauma or subarachnoid hemorrhage, growth hormone deficiency must be reconfirmed at one year after the event for therapy to continue. If retesting does not confirm growth hormone deficiency, continued treatment will not be approved.
ForwardHealth does not cover growth hormone drugs for members who do not comply with their prescribed growth hormone therapy.
Growth Hormone Stimulation Testing Requirements for Adults
Growth hormone stimulation testing should not be considered in adults without suggestive history of growth hormone deficiency such as a history of growth hormone deficiency diagnosed in childhood, hypothalamic pituitary disease, or cranial irradiation. In cases where there is suggestive history of growth hormone deficiency and a serum IGF-1 concentration below the age- and gender-specific lower limit of normal, growth hormone stimulation testing may be considered.
Growth hormone stimulation testing should be conducted after an overnight fast, using a well-standardized protocol, and should be conducted for the appropriate duration of time specific to the agents used to ensure the peak growth hormone level is captured. When two growth hormone stimulation tests are required, both stimulation tests can be administered the same day.
When growth hormone stimulation testing has been performed, complete testing results must be submitted with the PA request, including the following:
- Confirmation that the member was fasting
- The type of stimulation test and the dose of the stimulating agent
- A copy of the medical notes taken during the entire testing procedure, including vital signs and blood glucose levels
- The time and results from each blood sample taken
- The provider interpretation of the testing results
For members with thyroid deficiency, ForwardHealth only accepts results of the growth hormone stimulation tests that are performed after thyroid deficiency is adequately treated because growth hormone secretion may be subnormal merely as a result of hypothyroidism.
Growth hormone stimulation testing performed in a non-validated or sub-standard manner will not be considered by ForwardHealth to be an acceptable growth hormone stimulation test.
Growth hormone deficiency in an adult could be considered if the member has failed to respond to validated growth hormone stimulation testing performed using a well-standardized protocol, demonstrating a growth hormone peak response of less than the established level of the agent(s) given. Examples of agents commonly used in adult growth hormone stimulation testing include insulin, glucagon, and macimorelin. The peak response determining growth hormone deficiency for an adult differs based on the agent used, including the following:
- Insulin tolerance test: A growth hormone peak response of less than 5 mcg/L at every time point during the hypoglycemic phase of the test (If adequate hypoglycemia is not achieved [<40 mg/dL], then growth hormone deficiency cannot be diagnosed.)
- Glucagon test: A growth hormone peak response of less than 3 mcg/L at every time point during testing for members with a BMI less than 25 kg/m2 or a growth hormone peak response of less than 1 mcg/L at every time point during testing in patients with a BMI greater than or equal to 25 kg/m2
- Macimorelin-stimulation test: A growth hormone peak response of less than 2.8 ng/mlμg/L for members with a BMI of 40 kg/m2 or less. Strong CYP3A4 inducers should be discontinued with sufficient washout time prior to testing with macimorelin. Strong CYP3A4 inducers may reduce the plasma macimorelin concentrations and may lead to false positive test results. (Note: The safety and diagnostic performance of macimorelin have not been established with a BMI greater than 40 kg/m2.)
Growth hormone testing can provide useful information, but due to the recognized limitations of growth hormone stimulation testing and the risk of false positive results, ForwardHealth will consider the results of the growth hormone stimulation testing in the context of the entire clinical record for the PA request determination decision.
Note: Following the recommendation of the 2019 "American Association of Clinical Endocrinologists and American College of Endocrinology Guidelines for Management of Growth Hormone Deficiency in Adults and Patients Transitioning From Pediatric to Adult Care," ForwardHealth will not accept arginine stimulation testing for adults. The arginine stimulation tests have shown to exhibit a low sensitivity and specificity for adults and have not been systematically evaluated and validated.
Documentation Requirements for PA Requests for Growth Hormone for Adults
Detailed documentation of the medical work-up and testing used to determine the need for growth hormone treatment must be submitted with the PA request, including the following:
- Detailed endocrinology and medical work-up, including medical problem list, current medication list, and medication history
- Copies of the most recent IGF-1 lab reports
- TSH level
- Nutrition assessment
- Any other relevant testing, such as advanced imaging of the hypothalamic-pituitary region, if performed
PA requests for growth hormone drugs for adults must be submitted on the PA/PDL for Growth Hormone Drugs form. PA requests for growth hormone drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
If the clinical criteria for growth hormone drugs are met, initial PA requests may be approved for up to 183 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. A copy of the current endocrinology clinic notes, including the most current IGF-1 lab testing results, must be included with the PA request. Renewal PA requests may be approved for up to 365 days. Topic #23258 H. Pylori Drugs
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Voquezna Tablets
Voquezna tablets require clinical PA.
PA requests for Voquezna tablets must be completed, signed, and dated by the prescriber. PA requests for Voquezna tablets must be submitted using the Prior Authorization Drug Attachment for Voquezna Tablets form. Clinical documentation supporting the use of Voquezna tablets must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Voquezna Tablets form and a completed PA/RF to ForwardHealth.
PA requests for Voquezna tablets may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Voquezna Tablets
The clinical criteria for approval of a PA request for Voquezna tablets are all of the following:
- The member's age must be consistent with FDA-approved product labeling for Voquezna tablets.
- One of the following is true:
- The member has erosive esophagitis.
- The member has healed erosive esophagitis.
- The member has non-erosive gastroesophageal reflux disease.
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with at least two PPIs.
Supporting clinical information and a copy of the member's current medical records must be submitted with the PA request to support the member's condition and outline the member's current treatment plan.
If the clinical criteria for Voquezna tablets are met, PA requests may be approved for 183 days. Topic #21637 Headache Agents, Acute Treatment
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in the headache agents, acute treatment drug class.
Clinical PA is required for non-preferred headache agents, acute treatment drugs.
PA requests for non-preferred headache agents, acute treatment drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred headache agents, acute treatment drugs must be submitted on the Prior Authorization Drug Attachment for Headache Agents, Acute Treatment form. Clinical documentation supporting the use of the non-preferred headache agents, acute treatment drug must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Headache Agents, Acute Treatment form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred headache agents, acute treatment drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Non-Preferred Headache Agents, Acute Treatment Drugs
Clinical criteria for approval of a PA request for non-preferred headache agents, acute treatment drugs are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the drug requested.
- The prescriber has evaluated and diagnosed the member as having a history of migraines, with or without aura, according to ICHD-3 diagnostic criteria.
- One of the following is true:
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with at least two preferred drugs from the headache agents, triptans non-injectable drug class.
- The member has a clinically significant drug interaction with triptans and another medication the member is taking, or the member has a medical condition(s) that prevents the use of triptans.
- The member has taken two preferred headache agents, acute treatment drugs and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for non-preferred headache agents, acute treatment drugs. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
The medical records must demonstrate that the member meets the clinical criteria and document the member's medical work-up for migraines including complete problem and medication lists.
If the clinical criteria for non-preferred headache agents, acute treatment drugs are met, PA requests may be approved for up to 365 days. Topic #21117 Headache Agents, Preventative Treatment
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Clinical PA is required for non-preferred headache agents, preventative treatment drugs.
PA requests for non-preferred headache agents, preventative treatment drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred headache agents, preventative treatment drugs must be submitted using the Prior Authorization Drug Attachment for Headache Agents, Preventative Treatment form. Clinical documentation supporting the use of non-preferred headache agents, preventative treatment drugs must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Headache Agents, Preventative Treatment form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred headache agents, preventative treatment drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Non-Preferred Headache Agents, Preventative Treatment Drugs
Clinical criteria for approval of an initial PA request for non-preferred headache agents, preventative treatment drugs are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the drug requested.
- The prescriber has evaluated and diagnosed the member as having a history of migraines, with or without aura, according to ICHD-3 diagnostic criteria.
- The member is compliant with the prescribed headache medication treatment regimen and continues to experience four or more migraine headache days per month.
- The member's current prescribed migraine medication treatment regimen must be documented. The prescriber is required to indicate the member's current migraine preventative and rescue medications (drug name[s], dose, and dosing frequency) including Botox (if applicable).
- The member has taken two preferred headache agents, preventative treatment drugs for the preventative treatment of migraines for at least three consecutive months each and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests (initial, initial renewal, and subsequent renewal) for non-preferred headache agents, preventative treatment drugs. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
The medical records must demonstrate that the member meets the clinical criteria and document the member's medical work-up for migraines, including the current number of headache days per month, the number of migraine days per month, and the average migraine duration (in hours), as well as complete problem and medication lists.
If clinical criteria for non-preferred headache agents, preventative treatment drugs are met, initial PA requests may be approved for up to 183 days.
Initial Renewal PA Requests for Non-Preferred Headache Agents, Preventative Treatment Drugs
Clinical criteria that must be documented for approval of initial renewal PA requests for non-preferred headache agents, preventative treatment drugs are all of the following:
- The member experienced a clinically significant decrease in the number of migraine days per month and/or a decrease in migraine duration compared to their baseline prior to initiation of treatment with a non-preferred headache agent, preventative treatment drug.
- The member's current prescribed migraine medication treatment regimen has been documented. The prescriber is required to indicate the member's current migraine preventative and rescue medications (drug name[s], dose, and dosing frequency) including Botox (if applicable).
- The member has been compliant with their prescribed migraine medication treatment regimen.
Initial renewal PA requests for non-preferred headache agents, preventative treatment drugs may be approved for up to 365 days.
Subsequent Renewal PA Requests for Non-Preferred Headache Agents, Preventative Treatment Drugs
Clinical criteria that must be documented for approval of subsequent renewal PA requests for non-preferred headache agents, preventative treatment drugs are all of the following:
- The member has sustained a clinically significant decrease in the number of migraine days per month and/or a decrease in migraine duration compared to their baseline prior to initiation of treatment with a non-preferred headache agent, preventative treatment drug.
- The current number of headache days per month, the number of migraine days per month, and the average migraine duration (in hours) must be documented.
- The member's current prescribed migraine headache medication treatment regimen has been documented. The prescriber is required to indicate the member's current migraine preventative and rescue medications (drug name[s], dose, and dosing frequency) including Botox (if applicable).
- The member has been compliant with their prescribed migraine medication treatment regimen.
Subsequent renewal PA requests for non-preferred headache agents, preventative treatment drugs may be approved for up to 365 days. Topic #9878 Headache Agents, Triptans Non-Injectable
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Non-preferred drugs in the headache agents, triptans non-injectable drug class require PA. Preferred drugs do not require PA.
PA requests for non-preferred headache agents, triptans non-injectable drugs must be submitted on the PA/PDL for Headache Agents, Triptans Non-Injectable form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/PDL for Headache Agents, Triptans Non-Injectable form and a completed PA/RF to ForwardHealth.
PA requests for headache agents, triptans non-injectable drugs may be submitted using the STAT-PA system, on the Portal, by fax, or by mail.
Clinical Criterion for Non-Preferred Headache Agents, Triptans Non-Injectable Drugs
The sole clinical criterion for approval of a PA request for non-preferred headache agents, triptans non-injectable drugs is that the member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with at least three preferred drugs from the headache agents, triptans non-injectable drug class.
If the clinical criterion for non-preferred headache agents, triptans non-injectable drugs is met, PA requests may be approved for up to 365 days. Topic #8858 Hypoglycemics, Glucagon-Like Peptide Agents
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
All drugs in the hypoglycemics, GLP-1 drug class are diagnosis restricted. A ForwardHealth-allowed diagnosis code must be indicated on claims (and PA requests when applicable) for all drugs in the hypoglycemics, GLP-1 drug class.
Both preferred and non-preferred hypoglycemics, GLP-1 agents require a ForwardHealth-allowed diagnosis code on claims submitted to ForwardHealth. All preferred hypoglycemics GLP-1 drug claims must be submitted with a ForwardHealth-allowed diagnosis code, or PA is required.
Prescribers are required to indicate a diagnosis on prescriptions for all drugs that are identified by ForwardHealth as diagnosis restricted. If a diagnosis is not indicated on the prescription, pharmacy providers should contact the prescriber to obtain the diagnosis and document the diagnosis on the prescription or pharmacy health care record. It is not acceptable for pharmacy providers to obtain the diagnosis from the member.
PA requests for non-preferred hypoglycemics, GLP-1 agents must be completed, signed, and dated by the prescriber. PA requests for non-preferred hypoglycemics, GLP-1 agents must be submitted using the Prior Authorization Drug Attachment for Hypoglycemics, GLP-1 Agents form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Hypoglycemics, GLP-1 Agents form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred hypoglycemics, GLP-1 agents may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Non-Preferred Hypoglycemics, Glucagon-Like Peptide Agents
Clinical criteria for approval of a PA request for a non-preferred hypoglycemics, GLP-1 agent are all of the following:
- The non-preferred drug is being prescribed in a manner consistent with the FDA-approved product labeling.
- The member has type 2 diabetes mellitus.
- The member's HbA1c was measured within the past six months.
- If the member is not currently using a hypoglycemics, GLP-1 agent, their most recent HbA1c is 6.5% or greater.
One of the following must be documented for at least two of the preferred hypoglycemics, GLP-1 agents:
- The member has taken the maximum dose of a preferred hypoglycemics, GLP-1 agent for at least three consecutive months and experienced an unsatisfactory therapeutic response in glycemic control. (Note: Initial PA requests require an HbA1c measurement after the member has been taking the maximum dose of a preferred agent for at least three consecutive months.)
- The member experienced a clinically significant adverse drug reaction with a preferred hypoglycemics, GLP-1 agent.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for non-preferred hypoglycemics, GLP-1 agents. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
- The member's current HbA1c lab report
The following will not be considered as criteria to support the need for a non-preferred hypoglycemics, GLP-1 agent:
- Nonadherence to previous hypoglycemics, GLP-1 treatment
- The member's fear of needles
- The member's or prescriber's preference for the use of an oral agent
- The member's or prescriber's preference for the use of a non-preferred hypoglycemics, GLP-1 agent
- The member's or prescriber's preference for a less frequent dosing schedule
PA requests for non-preferred hypoglycemics, GLP-1 agents may be initially approved for up to 183 days.
Renewal PA requests may be approved for up to 365 days if the member has been adherent with the prescribed treatment regimen and had a reduction in their HbA1c compared to their baseline prior to the initiation of the non-preferred hypoglycemics, GLP-1 agent. Topic #19357 Hypoglycemics, Insulins Long-Acting
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
PA requests for non-preferred hypoglycemics, insulins long-acting drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred hypoglycemics, insulins long-acting drugs must be submitted using the Prior Authorization Drug Attachment for Hypoglycemics, Insulins Long-Acting form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Hypoglycemics, Insulins Long-Acting form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred hypoglycemics, insulins long-acting drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval, including what may not be considered criteria to support the need for a drug.
Clinical Criteria for Non-Preferred Hypoglycemics, Insulins Long-Acting Drugs
Clinical criteria that must be documented for approval of a PA request for a non-preferred hypoglycemics, insulins long-acting drug are all of the following:
- The member has diabetes.
- The member is unable to use insulin glargine U-100 due to one of the following:
- The member has used insulin glargine U-100 for at least six consecutive months and was unable to obtain adequate fasting glucose control.
- The member has used insulin glargine U-100 and experienced continued hypoglycemic episodes.
- The member's insulin treatment regimen was adjusted to optimize glycemic control or reduce hypoglycemia, and the member was compliant with their insulin treatment regimen and blood glucose monitoring schedule. (Insulin regimen adjustment options should include basal dose escalation, splitting the daily basal dose, adjusting the basal dosing time, and the addition or dose escalation of meal-time insulin.)
In addition to meeting the above clinical criteria, the following must be documented:
- The member's current insulin treatment regimen
- The member's previous insulin treatment regimen(s)
- The member's proposed insulin treatment regimen to include the non-preferred hypoglycemics, insulins long-acting drug (initial PA request only)
- The glycemic treatment goals the prescriber has established for the member, such as HbA1c and FBG
The following will not be considered as criteria to support the need for a non-preferred hypoglycemics, insulins long-acting drug:
- Nonadherence to previous insulin treatment regimen
- The member's or prescriber's preference for the use of a non-preferred hypoglycemics, insulins long-acting drug
- The member's or prescriber's preference for a smaller injection volume
If clinical criteria for a non-preferred hypoglycemics, insulins long-acting drug are met, initial PA requests may be approved for up to 183 days. Medical records must be submitted to support the need for a non-preferred hypoglycemics, insulins long-acting drug.
Renewal PA requests may be approved for up to 365 days. A copy of the member's current medical records must be submitted demonstrating an improvement in the member's glycemic control. Examples include a decrease in HbA1c, improved FBG, and decreased hypoglycemia. Topic #18297 Hepatitis C Agents
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Preferred drugs in the hepatitis C agents drug class do not require PA.
PA requests for non-preferred hepatitis C agents must be completed, signed, and dated by the prescriber. PA requests for hepatitis C agents should be submitted using the Prior Authorization Drug Attachment for Hepatitis C Agents form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Hepatitis C Agents form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred hepatitis C agents may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Pharmacy Provider-Specific PA Requests for Hepatitis C Agents
PA requests for non-preferred hepatitis C agents are approved as pharmacy provider-specific. This approach is used to ensure continuity of care for members approved for treatment with these complex drug therapies. When a PA request is approved for drugs in this class, the pharmacy provider will be notified of the pharmacy provider-specific PA status via the decision notice letter. ForwardHealth recommends that the pharmacy provider inform the member of the pharmacy provider-specific PA requirement. The pharmacy provider should explain to the member that the drug therapy authorized must be dispensed by the pharmacy provider approved under the PA request.
Pharmacy providers should not submit PA requests for non-preferred hepatitis C agents if they do not intend to also dispense the entire drug therapy approved under the PA request to the member. If the member needs to discontinue receiving the drug from the approved pharmacy provider once the approved treatment has begun, the pharmacy provider is required to contact Provider Services. Provider Services will work with the pharmacy provider on the approved PA request to ensure the member does not experience a disruption of therapy, and if necessary, will facilitate the transfer of the PA to a new pharmacy provider.
Clinical Information That Must Be Documented on PA Requests for Hepatitis C Agents
A copy of the member's medical records that document the following must be submitted with the PA request:
- HCV assessment and treatment plan
- Current history and physical, including complete problem and medication list
- Lab tests (performed within the last six months) for:
- Albumin
- CBC
- INR
- Liver function panel
- Serum creatinine
- HCV-RNA level
- HCV genotype and subtype
- HCV clinical data and medication treatment history, including the following:
- Likely source of the HCV infection and date diagnosed
- Liver biopsy, imaging studies, or blood assay tests to determine hepatic fibrosis
- History of previous hepatitis C drug therapy including medication name(s), dates taken, and treatment results (for example, null response, partial response, or relapse)
- If the member has cirrhosis, documentation of the following clinical assessments:
- CTP class and score
- HCC status based on an imaging study performed within the last six months
- Presence or treatment of any of the following:
- Ascites
- Hepatic encephalopathy
- Portal hypertension
- HCC
If the required documentation is not submitted with the PA request, the PA request will be considered incomplete and will be returned to the provider, or it may be denied.
Clinical Criteria for Hepatitis C Agents
The requested non-preferred hepatitis C agent is being prescribed in a manner consistent with the FDA-approved product labeling.
Note: Only eight weeks of Harvoni treatment will be approved for treatment-naive members who have HCV genotype 1 infection without cirrhosis, have an HCV-RNA level less than 6 million IU/mL, and are HIV uninfected.
The clinical criteria for approval of a PA request for non-preferred hepatitis C drugs are all of the following:
- The member is unable to take the preferred hepatitis C agent drugs due to one of the following:
- There is a clinically significant drug interaction with another drug the member is taking and the preferred drugs.
- The member has a medical condition(s) that prevents the use of the preferred drugs.
- The member does not have a significant or uncontrolled concurrent disease that would significantly reduce their life expectancy or limit adherence (for example, cardiovascular disease, cancer, pulmonary disease).
- For PA requests for Sovaldi, Vosevi, or Zepatier, the member does not have cirrhosis with moderate liver functional compromise (that is, CTP class B).
- The member does not have cirrhosis with severe liver functional compromise (that is, CTP class C). Currently, there is no evidence to support that HCV treatment of members with end-stage liver disease impacts morbidity or mortality. The severity of liver damage present in decompensated liver disease makes it unlikely that treating the underlying infection would lead to meaningful liver function improvement. The only definitive treatment for end-stage liver disease is a liver transplant.
In addition to meeting all of the above clinical criteria and HCV treatment program requirements, Zepatier requests for members with HCV genotype 1a infection must be tested for the presence of NS5A resistance-associated polymorphisms.
For members who have received a liver transplant, ForwardHealth will consider the requested HCV treatment regimen based on the member's entire medical record. The level of clinical evidence for the requested HCV treatment regimen will be considered. If there is low clinical evidence of the treatment's effectiveness, the PA request will be denied.
For members who have received prior HCV treatment, ForwardHealth will consider the requested HCV treatment regimen based on the member's entire medical record in addition to the HCV treatment history and response (for example, null response, partial response, or relapse). The level of clinical evidence for the requested HCV treatment regimen will be considered. If there is low clinical evidence of the treatment's effectiveness, the PA request will be denied. Topic #8857 Immunomodulators, Atopic Dermatitis
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Clinical PA is required for non-preferred immunomodulators, atopic dermatitis drugs.
PA requests for non-preferred immunomodulators, atopic dermatitis drugs will only be approved for use to treat the identified clinical conditions:
- AFRS
- Atopic dermatitis
- BP
- COPD
- CRSwNP
- CSU
- EoE
- Eosinophilic asthma
- Oral corticosteroid dependent asthma
- Prurigo nodularis
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for non-preferred immunomodulators, atopic dermatitis drugs. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
Note: If a member has more than one clinical condition for which ForwardHealth will approve a non-preferred immunomodulators, atopic dermatitis drug, and the provider would like to bypass the required trial of a ForwardHealth-preferred biologic drug, the provider must submit complete medical records for the clinical conditions. Additionally, the provider must clearly identify on the PA/DGA form that the member has more than one clinical condition for which the non-preferred drug is approved and provide justification for bypassing the required ForwardHealth-preferred biologic drug. ForwardHealth will use the member's complete clinical picture to evaluate the PA request.
PA requests for non-preferred immunomodulators, atopic dermatitis drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred immunomodulators, atopic dermatitis drugs must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of non-preferred immunomodulators, atopic dermatitis drugs must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred immunomodulators, atopic dermatitis drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
PA requests will not be considered for subcutaneous dosage forms of immunomodulators, atopic dermatitis drugs that will be administered in a medical office or medical facility.
Clinical Criteria for Immunomodulators, Atopic Dermatitis Drugs for Allergic Fungal Rhinosinusitis
Dupixent is a non-preferred drug used to treat AFRS.
Clinical criteria that must be documented for approval of a PA request for non-preferred drugs used to treat AFRS are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the requested drug.
- The prescription is written by or through consultation with an allergist or an ear, nose, and throat specialist.
- The member has AFRS with a history of sino-nasal surgery.
- The member was appropriately treated with post-surgical glucocorticoids and has been compliant with therapy.
- The results of a sinus CT study showing nasal polyposis with opacification of one or more sinuses must be submitted.
- The member will not use the requested drug in combination with any biologic immunomodulator.
If the clinical criteria for non-preferred immunomodulators, atopic dermatitis drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for non-preferred immunomodulators, atopic dermatitis drugs may be approved for up to 365 days. Renewal PA requests for members who have AFRS must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant reduction in AFRS symptoms.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Immunomodulators, Atopic Dermatitis Drugs for Atopic Dermatitis
Adbry and Ebglyss are preferred drugs used to treat atopic dermatitis. Preferred drugs do not require PA.
Cibinqo, Dupixent, Nemluvio, and Rinvoq are non-preferred drugs used to treat atopic dermatitis.
Clinical criteria that must be documented for approval of a PA request for non-preferred drugs for members with atopic dermatitis are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the drug requested.
- The member has moderate to severe atopic dermatitis. Documentation must include the approximate BSA involved and the area(s) affected.
- The prescription is written by or through consultation with a dermatologist, an allergist, or an immunologist.
- Exacerbating factors that may contribute to the member's atopic dermatitis, such as member non-compliance with therapy, environmental factors, dietary factors, and other similar dermatologic conditions, have been ruled out.
- The member will not use the requested drug in combination with any biologic immunomodulator.
- At least one of the following is true:
- The member has a recent history (within a year of the clinical visit when the requested drug was first prescribed) of use of at least a medium-potency topical corticosteroid for at least two months and experienced an unsatisfactory therapeutic response.
- The member has used at least a medium-potency corticosteroid and experienced a clinically significant adverse drug reaction.
- One of the following is true:
- The member is 6 months–11 years old (Dupixent PA requests).
- The member is 12–20 years of age and has taken Adbry or Ebglyss for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member is 21 years of age or older and has taken both Adbry and Ebglyss at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
If the clinical criteria for non-preferred immunomodulators, atopic dermatitis drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for non-preferred immunomodulators, atopic dermatitis drugs may be approved for up to 365 days. Renewal PA requests for members who have moderate to severe atopic dermatitis must include supporting clinical information and copies of the member's current medical records demonstrating that the member has had a significant reduction in the area(s) affected and/or severity of atopic dermatitis.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Immunomodulators, Atopic Dermatitis Drugs for Bullous Pemphigoid
Dupixent is a non-preferred drug used to treat BP.
Clinical criteria that must be documented for approval of a PA request for non-preferred drugs used to treat BP are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the requested drug.
- The member has moderate to severe BP.
- The prescription is written by or through consultation with a dermatologist.
- Exacerbating factors that may contribute to the member's BP, such as member non-compliance with therapy and other similar dermatologic conditions, have been ruled out.
- At least one of the following is true:
- The member has taken a high-potency topical corticosteroid and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken doxycycline and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken oral corticosteroids and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member will not use the requested drug in combination with any biologic immunomodulator.
If the clinical criteria for non-preferred immunomodulators, atopic dermatitis drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for non-preferred immunomodulators, atopic dermatitis drugs may be approved for up to 365 days. Renewal PA requests for members who have BP must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant reduction in BP symptoms.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Immunomodulators, Atopic Dermatitis Drugs for Chronic Obstructive Pulmonary Disease
Dupixent is a non-preferred drug used to treat COPD.
Clinical criteria that must be documented for the approval of non-preferred drugs used to treat COPD are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the drug requested.
- The member has COPD with an eosinophilic phenotype. A baseline blood eosinophil count of greater than 300 cells/mcL within the previous three months must be documented.
- The prescription is written by or through consultation with a COPD specialist (for example, an allergist, an immunologist, or a pulmonologist).
- The member has a history of two or more COPD exacerbations that required treatment with systemic corticosteroids and/or antibiotics, or an emergency department visit or hospitalization for the treatment of COPD in the past year. Documentation should include the approximate dates and what interventions took place for each exacerbation.
- The member's baseline FEV1 is 30–70% predicted. A baseline FEV1 percent predicted from the previous three months must be documented.
- The member has been adherent to and maintained on a maximized COPD treatment regimen, including triple therapy with a LAMA, LABA, and ICS for at least three months prior to requesting Dupixent. Documentation should include the LAMA, LABA, and ICS names, doses, and start dates.
- Exacerbating factors that may contribute to the member's COPD, such as member non-compliance with therapy, environmental factors, dietary factors, and other similar respiratory conditions, have been ruled out.
- The member will not use the requested drug in combination with any biologic immunomodulator.
If the clinical criteria for non-preferred immunomodulators, atopic dermatitis drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for non-preferred immunomodulators, atopic dermatitis drugs may be approved for up to 365 days. Renewal PA requests for members who have COPD must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a decrease in the number of COPD exacerbations or an increase in FEV1 percent predicted. Members must also continue to take their maximized COPD treatment regimen, including a LAMA, LABA, and ICS.
All renewal PA requests require the member to be adherent to the prescribed treatment regimen.
Clinical Criteria for Immunomodulators, Atopic Dermatitis Drugs for Chronic Rhinosinusitis With Nasal Polyposis
Dupixent is a non-preferred drug used to treat CRSwNP.
Clinical criteria that must be documented for approval of a PA request for non-preferred drugs used to treat CRSwNP are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the requested drug.
- The member has CRSwNP.
- The prescription is written by or through consultation with an allergist or an ear, nose, and throat specialist.
- The member has been adherent to and maintained on a maximized CRSwNP treatment regimen, including an INCS for at least three months prior to requesting Dupixent. Documentation should include the CRSwNP drug treatment names, doses, and start dates.
- At least one of the following is true:
- The member is 12–17 years old.
- The member is 18 years of age or older and has taken Xolair for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member is 18 years of age or older and has a serum IgE level less than 30 IU/mL. A current serum IgE level completed within the past 90 days must be submitted.
- The member will not use the requested drug in combination with any biologic immunomodulator.
If clinical criteria for non-preferred immunomodulators, atopic dermatitis drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for non-preferred immunomodulators, atopic dermatitis drugs may be approved for up to 365 days. Renewal PA requests for members who have CRSwNP must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant reduction in CRSwNP symptoms. Members must also continue to take their maximized CRSwNP treatment regimen, including the INCS.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Immunomodulators, Atopic Dermatitis Drugs for Chronic Spontaneous Urticaria
Dupixent and Rhapsido are non-preferred drugs used to treat CSU.
Clinical criteria that must be documented for approval of a PA request for non-preferred drugs used to treat CSU are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the requested drug.
- The member has CSU.
- The prescription is written by or through consultation with an allergist or a dermatologist.
- The member has taken the maximum dose of an H1 antihistamine for at least two consecutive weeks and remains symptomatic. The H1 antihistamine name, dose, and dates taken must be documented.
- The member has taken Xolair for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member will not use the requested drug in combination with any biologic immunomodulator.
If clinical criteria for non-preferred immunomodulators, atopic dermatitis drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for non-preferred immunomodulators, atopic dermatitis drugs may be approved for up to 365 days. Renewal PA requests for members who have CSU must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant reduction in CSU symptoms.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Immunomodulators, Atopic Dermatitis Drugs for Eosinophilic Asthma
Dupixent is a non-preferred drug used to treat eosinophilic asthma.
Clinical criteria that must be documented for approval of a PA request for non-preferred drugs used to treat eosinophilic asthma are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the requested drug.
- The member has eosinophilic asthma. A baseline blood eosinophil count of greater than 150 cells/mcL within the previous three months must be documented.
- The prescription is written by or through consultation with an asthma specialist (for example, an allergist, an immunologist, or a pulmonologist).
- At least one of the following is true:
- The member has a history of two or more asthma exacerbations that required treatment with systemic corticosteroids or an emergency department visit or hospitalization for the treatment of asthma in the past year. Documentation should include the approximate dates and what interventions took place for each exacerbation.
- The member's baseline FEV1 is less than 80% predicted. A baseline FEV1 percent predicted from the previous three months must be documented.
- The member has been adherent to and maintained on a maximized asthma treatment regimen, including a high-dose ICS in combination with a LABA for at least three months prior to requesting Dupixent. Documentation should include the ICS and LABA names, doses, and start dates.
- The member has taken Fasenra for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- Exacerbating factors that may contribute to the member's asthma, such as member non-compliance with therapy, environmental factors, dietary factors, and other similar respiratory conditions, have been ruled out.
- The member will not use the requested drug in combination with any biologic immunomodulator.
If the clinical criteria for non-preferred immunomodulators, atopic dermatitis drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for non-preferred immunomodulators, atopic dermatitis drugs may be approved for up to 365 days. Renewal PA requests for members who have eosinophilic asthma must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a decrease in the number of asthma exacerbations or an increase in FEV1 percent predicted compared to their baseline prior to initiation of the requested drug. Members must also continue to take their maximized asthma treatment regimen, including an ICS and a LABA.
All renewal PA requests require the member to be adherent to the prescribed treatment regimen.
Clinical Criteria for Immunomodulators, Atopic Dermatitis Drugs for Eosinophilic Esophagitis
Dupixent is a non-preferred drug used to treat EoE.
Clinical criteria that must be documented for approval of a PA request for a non-preferred drug used to treat EoE are all of the following:
- The member's age and weight are consistent with the FDA-approved product labeling for the requested drug.
- The member has EoE. A baseline intraepithelial eos/hpf, of greater than or equal to 15 must be documented.
- The prescription is written by or through consultation with an allergist or a gastroenterologist.
- Exacerbating factors that may contribute to the member's EoE, such as member non-compliance with therapy, environmental allergies, food allergies, acid reflux, and other allergic/immune conditions of the esophagus, have been ruled out.
- At least one of the following is true:
- The member has a recent history (within a year of the clinical visit when the requested drug was first prescribed) of PPI use for at least two months and experienced an unsatisfactory therapeutic response.
- The member has used a PPI and experienced a clinically significant adverse drug reaction.
- The member will not use the requested drug in combination with any biologic immunomodulator.
If the clinical criteria for non-preferred immunomodulators, atopic dermatitis drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for non-preferred immunomodulators, atopic dermatitis drugs may be approved for up to 365 days. Renewal PA requests for members who have EoE must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant reduction in eos/hpf or EoE symptoms (abdominal pain, chest pain, dysphagia, difficulty feeding, impaction, regurgitation, vomiting).
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Immunomodulators, Atopic Dermatitis Drugs for Oral Corticosteroid Dependent Asthma
Dupixent is a non-preferred drug used to treat oral corticosteroid dependent asthma.
Clinical criteria that must be documented for approval of a PA request for a non-preferred drug used to treat oral corticosteroid dependent asthma are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the requested drug.
- The member has oral corticosteroid dependent asthma.
- The prescription is written by or through consultation with an asthma specialist (for example, an allergist, an immunologist, or a pulmonologist).
- The member has been adherent and maintained on a maximized asthma treatment regimen, including a high-dose ICS in combination with a LABA for at least three months prior to requesting Dupixent. Documentation should include the ICS and LABA names, doses, and start dates.
- The member has required daily oral corticosteroid treatment for at least three months prior to requesting Dupixent. Documentation should include the oral corticosteroid name, daily dose, and start date.
- Exacerbating factors that may contribute to the member's asthma, such as member non-compliance with therapy, environmental factors, dietary factors, and other similar respiratory conditions, have been ruled out.
- The member will not use the requested drug in combination with any biologic immunomodulator.
If the clinical criteria for non-preferred immunomodulators, atopic dermatitis drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for non-preferred immunomodulators, atopic dermatitis drugs may be approved for up to 365 days. Renewal PA requests for members who have oral corticosteroid dependent asthma must include supporting clinical information and copies of the member's current medical records demonstrating that the member's daily oral corticosteroid dose has decreased, while maintaining asthma control. Members must also continue to take their maximized asthma treatment regimen, including an ICS and a LABA.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Immunomodulators, Atopic Dermatitis Drugs for Prurigo Nodularis
Dupixent and Nemluvio are non-preferred drugs used to treat prurigo nodularis.
Clinical criteria that must be documented for approval of a PA request for non-preferred drugs used to treat prurigo nodularis are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the requested drug.
- The member has moderate to severe prurigo nodularis.
- The prescription is written by or through consultation with a dermatologist.
- Exacerbating factors that may contribute to the member's prurigo nodularis, such as member non-compliance with therapy and other similar dermatologic conditions, have been ruled out.
- At least one of the following is true:
- The member has a recent history (within a year of the clinical visit when the requested drug was first prescribed) of a topical treatment(s) to reduce itching and inflammation for at least two months and experienced an unsatisfactory therapeutic response.
- The member has used a topical treatment(s) to reduce itching and inflammation and experienced a clinically significant adverse drug reaction.
- The member will not use the requested drug in combination with any biologic immunomodulator.
If the clinical criteria for non-preferred immunomodulators, atopic dermatitis drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for non-preferred immunomodulators, atopic dermatitis drugs may be approved for up to 365 days. Renewal PA requests for members who have prurigo nodularis must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant reduction in prurigo nodularis symptoms.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #23497 Immunomodulators, Atopic Dermatitis—Topical Drugs
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Non-preferred immunomodulators, atopic dermatitis—topical drugs require clinical PA.
PA requests for non-preferred immunomodulators, atopic dermatitis—topical drugs must be completed, signed, and dated by the prescriber. PA requests for non-preferred immunomodulators, atopic dermatitis—topical drugs must be submitted using the PA/PDL for Immunomodulators Atopic Dermatitis—Topical form. Clinical documentation supporting the use of non-preferred immunomodulators, atopic dermatitis—topical drugs must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/PDL for Immunomodulators, Atopic Dermatitis—Topical form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred immunomodulators, atopic dermatitis—topical drugs may be submitted using the STAT-PA system, on the Portal, by fax, or by mail.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Non-Preferred Immunomodulators, Atopic Dermatitis—Topical Drugs
Clinical criteria that must be documented for approval of a PA request for non-preferred immunomodulators, atopic dermatitis—topical drugs are all of the following:
- The member has atopic dermatitis.
- At least one of the following is true:
- The member used Eucrisa for at least two consecutive months and experienced an unsatisfactory therapeutic response.
- The member used Eucrisa and experienced a clinically significant adverse drug reaction.
- At least one of the following is true:
- The member used a topical calcineurin inhibitor for at least two consecutive months and experienced an unsatisfactory therapeutic response.
- The member used a topical calcineurin inhibitor and experienced a clinically significant adverse drug reaction.
If the clinical criteria for non-preferred immunomodulators, atopic dermatitis—topical drugs are met, initial PA requests may be approved for up to 365 days.
Opzelura for Members With Vitiligo
In addition to atopic dermatitis, PA requests for Opzelura will only be approved for use to treat vitiligo.
PA requests for Opzelura for members with vitiligo must be completed, signed, and dated by the prescriber. PA requests for Opzelura for members with vitiligo must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred Opzelura for members with vitiligo may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Opzelura for Members With Vitiligo
Clinical criteria that must be documented for approval of a PA request for Opzelura for members with vitiligo are all of the following:
- The member's age is consistent with the FDA-approved product labeling for Opzelura.
- The member has nonsegmental vitiligo. The member's total BSA affected must be documented.
- The BSA of the area to be treated must be 10% or less. The prescriber must document the specific areas to be treated.
- The prescription is written by a dermatologist or through a dermatology consultation.
- The member will not use Opzelura in combination with therapeutic biologics, other JAK inhibitors or potent immunosuppressants such as azathioprine or cyclosporine.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Opzelura for members with vitiligo. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If clinical criteria for Opzelura for members with vitiligo are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Opzelura for members with vitiligo may be approved for up to 365 days. Renewal PA requests for members who have vitiligo must include supporting clinical information and copies of the member's current medical records demonstrating that the member had meaningful repigmentation compared to the member's baseline prior to starting Opzelura.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #22357 Immunomodulators, Asthma
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Clinical PA is required for non-preferred immunomodulator, asthma drugs.
Nucala and Tezspire
Nucala and Tezspire require clinical PA.
PA requests for Nucala or Tezspire must be completed, signed, and dated by the prescriber. PA requests for Nucala or Tezspire must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Nucala or Tezspire must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Nucala or Tezspire may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Notes:
- Fasenra, Nucala, Tezspire, and Xolair in the immunomodulators, asthma drug class are available as physician-administered drugs, as well as through the pharmacy benefit. The PDL and clinical PA criteria apply only to drugs billed through the pharmacy benefit.
- If a member has more than one clinical condition for which ForwardHealth will approve a non-preferred immunomodulators, asthma drug and the provider would like to bypass the required trial of a ForwardHealth-preferred biologic drug, the provider must submit complete medical records for the clinical conditions. Additionally, the provider must clearly identify on the PA/DGA form that the member has more than one clinical condition for which the non-preferred drug is approved, and they must provide justification for bypassing the required ForwardHealth-preferred biologic drug. ForwardHealth will use the member's complete clinical picture to evaluate the PA request.
Conditions for Which PA Requests for Use of Nucala Will Be Considered for Review
PA requests for Nucala will only be approved for use to treat the identified clinical conditions:
- Asthma with an eosinophilic phenotype
- COPD
- CRSwNP
- EGPA
- HES
Clinical Criteria for Nucala for Members With Asthma With an Eosinophilic Phenotype
Clinical criteria that must be documented for approval of a PA request for Nucala for members with asthma with an eosinophilic phenotype are all of the following:
- The member's age is consistent with the FDA-approved product labeling for Nucala.
- The member has asthma with an eosinophilic phenotype. A baseline blood eosinophil count of greater than 150 cells/mcL within the previous three months must be documented.
- The prescription is written by or through consultation with an asthma specialist (for example, an allergist, an immunologist, or a pulmonologist).
- At least one of the following is true:
- The member has a history of two or more asthma exacerbations that required treatment with systemic corticosteroids or an emergency department visit or hospitalization for the treatment of asthma in the past year. Documentation should include the approximate dates and what interventions took place for each exacerbation.
- The member's baseline FEV1 is less than 80% predicted. A baseline FEV1 percent predicted from the previous three months must be documented.
- The member has been adherent to and maintained on a maximized asthma treatment regimen, including a high-dose ICS in combination with a LABA for at least three months prior to requesting Nucala. Documentation should include the ICS and LABA names, doses, and start dates.
- The member has taken Fasenra for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- Exacerbating factors that may contribute to the member's asthma, such as member non-compliance with therapy, environmental factors, dietary factors, and other similar respiratory conditions, have been ruled out.
- The member will not use Nucala in combination with any biologic immunomodulator.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Nucala for members with asthma with an eosinophilic phenotype. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Nucala are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Nucala may be approved for up to 365 days. Renewal PA requests for members who have asthma with an eosinophilic phenotype must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a decrease in the number of asthma exacerbations or an increase in FEV1 percent predicted compared to their baseline prior to the initiation of Nucala. Members must also continue to take their maximized asthma treatment regimen, including an ICS and a LABA, during treatment with Nucala.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Nucala for Members With Chronic Obstructive Pulmonary Disease
Clinical criteria that must be documented for approval of a PA request for Nucala for members with COPD are all of the following:
- The member's age is consistent with the FDA-approved product labeling for Nucala.
- The member has COPD with an eosinophilic phenotype. A baseline blood eosinophil count of greater than 150 cells/mcL within the previous three months must be documented.
- The prescription is written by or through consultation with a COPD specialist (for example, an allergist, an immunologist, or a pulmonologist).
- The member has a history of two or more COPD exacerbations that required treatment with systemic corticosteroids and/or antibiotics, or an emergency department visit or hospitalization for the treatment of COPD in the past year. Documentation should include the approximate dates and what interventions took place for each exacerbation.
- The member's baseline FEV1 is 20–80% predicted. A baseline FEV1 percent predicted from the previous three months must be documented.
- The member has been adherent to and maintained on a maximized COPD treatment regimen, including triple therapy with a LAMA, LABA, and ICS for at least three months prior to requesting Nucala. Documentation should include the LAMA, LABA, and ICS names, doses, and start dates.
- Exacerbating factors that may contribute to the member's COPD, such as member non-compliance with therapy, environmental factors, dietary factors, and other similar respiratory conditions, have been ruled out.
- The member will not use the requested drug in combination with any biologic immunomodulator.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Nucala for members with COPD. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Nucala are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Nucala may be approved for up to 365 days. Renewal PA requests for members who have COPD must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a decrease in the number of COPD exacerbations or an increase in FEV1 percent predicted. Members must also continue to take their maximized COPD treatment regimen, including a LAMA, LABA, and ICS.
All renewal PA requests require the member to be adherent to the prescribed treatment regimen.
Clinical Criteria for Nucala for Members With Chronic Rhinosinusitis With Nasal Polyposis
Clinical criteria that must be documented for approval of a PA request for Nucala for members with CRSwNP are all of the following:
- The member's age is consistent with the FDA-approved product labeling for Nucala.
- The member has CRSwNP.
- The prescription is written by or through consultation with an allergist or an ear, nose, and throat specialist.
- The member has been adherent to and maintained on a maximized CRSwNP treatment regimen, including an INCS for at least three months prior to requesting Nucala. Documentation should include the CRSwNP drug treatment names, doses, and start dates.
- At least one of the following is true:
- The member has taken Xolair for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has a serum IgE level less than 30 IU/mL. A current serum IgE level completed within the past 90 days must be submitted.
- The member will not use Nucala in combination with any biologic immunomodulator.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Nucala for members with CRSwNP. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If clinical criteria for Nucala are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Nucala may be approved for up to 365 days. Renewal PA requests for members who have CRSwNP must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant reduction in CRSwNP symptoms compared to the member's baseline prior to the initiation of Nucala. Members must also continue to take their maximized CRSwNP treatment regimen, including the INCS, during treatment with Nucala.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Nucala for Members With Eosinophilic Granulomatosis With Polyangiitis
Clinical criteria that must be documented for approval of a PA request for Nucala for members with EGPA are all of the following:
- The member's age must be consistent with FDA-approved product labeling for Nucala.
- The member has EGPA.
- The prescription is written by or through consultation with an EGPA specialist.
- The member has taken Fasenra for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member will not use Nucala in combination with any biologic immunomodulator.
Supporting clinical information and a copy of the member's current medical records must be submitted with the PA request to support the member's condition of EGPA and outline the member's current treatment plan for EGPA.
If clinical criteria for Nucala are met, initial PA requests may be approved for up to 183 days. Renewal PA requests for Nucala may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Nucala for Members With Hypereosinophilic Syndrome
Clinical criteria that must be documented for approval of a PA request for Nucala for members with HES are all of the following:
- The member's age must be consistent with FDA-approved product labeling for Nucala.
- The member has had HES for six or more months without an identifiable non-hematologic secondary cause.
- The prescription is written by or through consultation with an HES specialist.
- The member will not use Nucala in combination with any biologic immunomodulator.
Supporting clinical information and a copy of the member's current medical records must be submitted with the PA request to support the member's condition of HES and outline the member's current treatment plan for HES.
If clinical criteria for Nucala are met, initial PA requests may be approved for up to 183 days. Renewal PA requests for Nucala may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Conditions for Which PA Requests for Use of Tezspire Will Be Considered for Review
PA requests for Tezspire will only be approved for use to treat the identified clinical conditions:
Clinical Criteria for Tezspire for Members With Chronic Rhinosinusitis With Nasal Polyposis
Clinical criteria that must be documented for approval of a PA request for Tezspire for members with CRSwNP are all of the following:
- The member's age is consistent with the FDA-approved product labeling for Tezspire.
- The member has CRSwNP.
- The prescription is written by or through consultation with an allergist or an ear, nose, and throat specialist.
- The member has been adherent to and maintained on a maximized CRSwNP treatment regimen, including an INCS for at least three months prior to requesting Tezspire. Documentation should include the CRSwNP drug treatment names, doses, and start dates.
- At least one of the following is true:
- The member is 12–17 years old.
- The member is 18 years of age or older and has taken Xolair for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member is 18 years of age or older and has a serum IgE level less than 30 IU/mL. A current serum IgE level completed within the past 90 days must be submitted.
- The member will not use Tezspire in combination with any biologic immunomodulator.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Tezspire for members with CRSwNP. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If clinical criteria for Tezspire for members with CRSwNP are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Tezspire for members with CRSwNP may be approved for up to 365 days. Renewal PA requests for members who have CRSwNP must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant reduction in CRSwNP symptoms compared to the member's baseline prior to the initiation of Tezspire. Members must also continue to take their maximized CRSwNP treatment regimen, including the INCS, during treatment with Tezspire.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Tezspire for Members With Severe Asthma
Clinical criteria that must be documented for approval of a PA request for Tezspire for members with severe asthma are all of the following:
- The member's age is consistent with the FDA-approved product labeling for Tezspire.
- The member has severe asthma.
- The prescription is written by or through consultation with an asthma specialist (for example, an allergist, an immunologist, or a pulmonologist).
- The member has a history of two or more asthma exacerbations that required treatment with systemic corticosteroids or an emergency department visit or hospitalization for the treatment of asthma in the past year. Documentation should include the approximate dates and what interventions took place for each exacerbation.
- The member has been adherent to and maintained on a maximized asthma treatment regimen, including a high-dose ICS in combination with a LABA for at least three months prior to requesting Tezspire. Documentation should include the ICS and LABA names, doses, and start dates.
- Exacerbating factors that may contribute to the member's asthma, such as member non-compliance with therapy, environmental factors, dietary factors, and other similar respiratory conditions, have been ruled out.
- The member will not use Tezspire in combination with any biologic immunomodulator.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Tezspire for members with severe asthma. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If clinical criteria for Tezspire for members with severe asthma are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Tezspire for members with severe asthma may be approved for up to 365 days. Renewal PA requests for members who have severe asthma must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a decrease in the number of asthma exacerbations compared to the member's baseline prior to the initiation of Tezspire. Members must also continue to take their maximized asthma treatment regimen, including an ICS and a LABA, during treatment with Tezspire.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #12897 Legacy Exemptions for Alzheimer's Agents
BadgerCare Plus, Medicaid, and SeniorCare members who were eligible for the legacy exemption for galantamine tablets or galantamine ER for DOS on and after January 1, 2012, and remained eligible throughout 2025, will no longer be allowed to receive the legacy exemption for galantamine tablets or galantamine ER for DOS on and after January 1, 2026, if one of the following is true:
- Members without other primary insurance on file with ForwardHealth have had no claim activity for galantamine tablets or galantamine ER for DOS in the last six months of 2025.
- Members with other primary insurance on file with ForwardHealth have had no claim activity for galantamine tablets or galantamine ER for DOS in calendar year 2025.
PA is required for galantamine tablets and galantamine ER for members who do not have a legacy exemption for either one of the drugs. Topic #10659 Legacy Exemptions for Antipsychotic Drugs
BadgerCare Plus, Medicaid, and SeniorCare members who were granted a legacy exemption for thioridazine for DOS on and after October 1, 2010, and remained eligible throughout 2025, will no longer be allowed to receive the legacy exemption for thioridazine for DOS on and after January 1, 2026, if one of the following is true:
- Members without other primary insurance on file with ForwardHealth have had no claim activity for thioridazine for DOS in the last six months of 2025.
- Members with other primary insurance on file with ForwardHealth have had no claim activity for thioridazine for DOS in calendar year 2025.
PA is required for thioridazine for members who do not have a legacy exemption for the drug. Topic #10662 Legacy Exemptions for Stimulant Drugs
BadgerCare Plus, Medicaid, and SeniorCare members who were granted a legacy exemption for designated amphetamine drugs for DOS on and after January 1, 2018, and remained eligible throughout 2025, will no longer be allowed to receive the legacy exemption for amphetamine drugs for DOS on and after January 1, 2026, if one of the following is true:
- Members without other primary insurance on file with ForwardHealth have had no claim activity for amphetamine drugs for DOS in the last six months of 2025.
- Members with other primary insurance on file with ForwardHealth have had no claim activity for amphetamine drugs for DOS in calendar year 2025.
PA is required for designated amphetamine drugs for members who do not have a legacy exemption for the drug.
The table below lists the allowed legacy exemptions for amphetamine drugs and their applicable legacy exemption details.
Drugs in the stimulants drug class are diagnosis restricted. A ForwardHealth-allowed diagnosis code must be indicated on claims for all stimulant drugs.
| Designated Legacy Exemptions for Stimulant Drugs | Details |
|
dextroamphetamine
dextroamphetamine ER |
Eligible members identified to be taking any one of these two drugs are allowed to receive any of the following as a legacy exemption stimulant drug:
- Generic dextroamphetamine
- Generic dextroamphetamine ER
Note: An approved PA request is not required for any child 6 years of age or younger for generic dextroamphetamine.
|
| Adderall
Adderall XR
dextroamphetamine-amphetamine
dextroamphetamine-amphetamine ER |
Eligible members identified to be taking any one of these four drugs are allowed to receive any of the following as a legacy exemption stimulant drug:
- Adderall
- Adderall XR
- Generic dextroamphetamine-amphetamine
- Generic dextroamphetamine-amphetamine ER
Note: An approved PA request is not required for any child 6 years of age or younger for brand name Adderall or generic dextroamphetamine-amphetamine.
|
Topic #21617 Lipotropics, Adenosine Triphosphate—Citrate Lyase Inhibitors
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
All drugs in the lipotropics, ACL inhibitor drug class are non-preferred and require PA.
PA requests for lipotropics, ACL inhibitor drugs must be completed and signed by the prescriber. PA requests for lipotropics, ACL inhibitor drugs should be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of a lipotropics, ACL inhibitor drug also must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. The prescriber should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for lipotropics, ACL inhibitor drugs may be submitted on the on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval, including what may not be considered criteria to support the need for a drug.
Conditions for Which PA Requests for Use of Lipotropics, Adenosine Triphosphate—Citrate Lyase Inhibitor Drugs Will Be Considered for Review
ForwardHealth will only consider PA requests for lipotropics, ACL inhibitor drugs to treat the following identified clinical conditions:
- Clinical ASCVD
- High risk for a cardiovascular disease event
- HeFH
ForwardHealth will approve up to one ACL inhibitor or one PCSK9 inhibitor at a time per member. ForwardHealth does not cover treatment with more than one ACL inhibitor and/or PCSK9 inhibitor.
Clinical Criteria for Lipotropics, Adenosine Triphosphate—Citrate Lyase Inhibitor Drugs for Members With Clinical Atherosclerotic Cardiovascular Disease
Clinical criteria that must be documented for approval of a PA request for lipotropics, ACL inhibitor drugs for members with clinical ASCVD are all of the following:
- The member has clinical ASCVD, as evidenced by one of the following:
- The member has CAD, which is supported by a history of myocardial infarction (heart attack), coronary revascularization, or angina pectoris.
- The member has a history of stroke.
- The member has symptomatic peripheral arterial disease as evidenced by one of the following:
- Intermittent claudication with an ABI of less than or equal to 0.9
- Peripheral arterial revascularization procedure or amputation due to atherosclerotic disease
- One of the following is true
- The member is currently taking a statin.
- The member is unable to take a statin, as evidenced by experiencing an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with at least three statins.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for lipotropics, ACL inhibitor drugs for members with clinical ASCVD. The supporting clinical information and medical records must document the following:
- Evidence that the member has clinical ASCVD
- A current lipid panel lab report
- Documentation of the member's current and previous lipid-lowering drug therapies, including the following for each trial:
- Drug name(s) and dosage
- Dates taken
- Lipid panel report prior to and during drug therapy (including dates taken)
Initial and Renewal PA Requests for Lipotropics, Adenosine Triphosphate—Citrate Lyase Inhibitor Drugs for Members With Clinical Atherosclerotic Cardiovascular Disease
If the clinical criteria for lipotropics, ACL inhibitor drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for lipotropics, ACL inhibitor drugs may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Lipotropics, Adenosine Triphosphate—Citrate Lyase Inhibitor Drugs for Members Who Are High Risk for a Cardiovascular Disease Event
Clinical criteria that must be documented for approval of a PA request for lipotropics, ACL inhibitor drugs for members who are high risk for a cardiovascular disease event are all of the following:
- The member is high risk for a cardiovascular disease event, as evidenced by one of the following:
- The member has diabetes mellitus (type I or II) and is a female over 65 years of age or is a male over 60 years of age.
- The member is high risk for ASCVD as determined by an ASCVD risk calculator. The name of the risk calculator used and the member's score must be documented.
- The member has a coronary artery calcium score greater than 400 Agatston units.
- One of the following is true:
- The member is currently taking a statin.
- The member is unable to take a statin, as evidenced by experiencing an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with at least three statins.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for lipotropics, ACL inhibitor drugs for members who are high risk for a cardiovascular event. The supporting clinical information and medical records must document the following:
- Evidence that the member is high risk for a cardiovascular disease event
- Documentation of the member's current and previous lipid-lowering drug therapies, including the following for each trial:
- Drug name(s) and dosage
- Dates taken
- Reasons for for discontinuation if drug therapy was discontinued
Initial and Renewal PA Requests for Lipotropics, Adenosine Triphosphate—Citrate Lyase Inhibitor Drugs for Members Who Are High Risk for a Cardiovascular Disease Event
If the clinical criteria for lipotropics, ACL inhibitor drugs for members who are high risk for a cardiovascular event are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for lipotropics, ACL inhibitor drugs for members who are high risk for a cardiovascular event may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Lipotropics, Adenosine Triphosphate—Citrate Lyase Inhibitor Drugs for Members With Heterozygous Familial Hypercholesterolemia
Clinical criteria that must be documented for approval of a PA request for lipotropics, ACL inhibitor drugs for members with HeFH are all of the following:
- The member has been diagnosed by a specialist in cardiology or lipid management.
- The member has HeFH, as evidenced by clinical documentation that supports a definitive diagnosis of HeFH using either WHO criteria (Dutch Lipid Clinic Network clinical criteria with a score greater than eight) or Simon Broome diagnostic criteria.
- The member attempted to maximize treatment with statins prior to requesting a lipotropics, ACL inhibitor drug. The member must have taken a maximized statin regimen for at least three continuous months with failure to reach an LDL less than or equal to 100 mg/dL. (Note: Members who are not taking a maximized statin regimen, which includes atorvastatin, rosuvastatin, or simvastatin, are required to attempt a second statin in order to establish a maximum treatment regimen.)
- The member must continue to take the maximized statin regimen during treatment with the lipotropics, ACL inhibitor drug unless the member is statin intolerant. Statin intolerance must be established through trials with at least three different statins (with one regimen containing pravastatin, fluvastatin, or rosuvastatin).
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for lipotropics, ACL inhibitor drugs for members with HeFH. The supporting clinical information and medical records must document the following:
- Evidence that the member has HeFH
- A current lipid panel lab report
- Documentation of the member's current and previous lipid-lowering drug therapies, including the following for each trial:
- Drug name(s) and dosage
- Dates taken
- Lipid panel report prior to and during drug therapy (including dates taken)
Initial and Renewal PA Requests for Lipotropics, Adenosine Triphosphate—Citrate Lyase Inhibitor Drugs for Members With Heterozygous Familial Hypercholesterolemia
If the clinical criteria for lipotropics, ACL inhibitor drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for lipotropics, ACL inhibitor drugs may be approved for up to 365 days. Renewal PA requests for members who have HeFH must include supporting clinical information and copies of the member's current medical records demonstrating evidence of LDL reduction of at least 30 percent from the pre-treatment baseline or a decrease to 130 mg/dL or less. Members also must continue to take a statin during treatment with a lipotropics, ACL inhibitor drug.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. A copy of the current lipid panel report (within the past 30 days) must be included with the PA request. Topic #19317 Lipotropics, Apo-B Inhibitors
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
PA is required for all lipotropics, apo-B inhibitor drugs.
PA requests for lipotropics, apo-B inhibitor drugs must be completed, signed, and dated by the prescriber. PA requests for lipotropics, apo-B inhibitor drugs must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of a lipotropics, apo-B inhibitor drug also must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for lipotropics, apo-B inhibitor drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
For information about general ForwardHealth PA policy for drugs that require PA approval, prescribers and pharmacy providers may refer to the Standard Pharmacy Policy for Covered and Noncovered Drugs topic. Providers may also refer to this topic for information about what may not be considered criteria to support the need for a drug.
Clinical Criteria for Lipotropics, Apolipoprotein B Inhibitor Drugs
Clinical criteria that must be documented for approval of a PA request for lipotropics, apo-B inhibitor drugs are all of the following:
- The member has HoFH, as evidenced by one of the following:
- The member has genetic confirmation of two of the following mutant alleles at the LDL receptor:
- Apo-B
- PCSK9
- ARH adaptor protein gene locus
- The member has an untreated LDL-C greater than 500 mg/dL or a total treated LDL-C greater than or equal to 300 mg/dL and one of the following:
- Cutaneous tendinous xanthoma(s) before 10 years of age
- Untreated LDL-C levels of greater than or equal to 190 mg/dL in both parents
- The member must have attempted to maximize treatment with LDL-lowering therapies prior to requesting a lipotropics, apo-B inhibitor drug. The member must have taken a PCSK9 inhibitor combined with a statin for at least three continuous months with failure to reach an LDL level of 130 mg/dL or less, or the member has had a clinically significant adverse drug reaction, clinically significant drug interaction, or medical condition preventing the member from using these drugs. Members also must continue to take the maximized LDL-lowering treatment regimen during treatment with the lipotropics, apo-B inhibitor drug.
Note: The member's inability to use one or more of the previously described drug therapies does not preclude the requirement for the member to use all of the above drug therapies for which the member does not have a clinically significant adverse drug reaction, clinically significant drug interaction, or medical condition preventing the member from using a specific drug.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for lipotropics, apo-B inhibitor drugs. The supporting clinical information and medical records must document the following:
- Evidence that the member has HoFH
- A current lipid panel lab report
- Documentation of the member's current and previous PCSK9 inhibitor and statin drug therapies, including the following for each trial:
- Drug name(s) and dosage
- Dates taken
- Lipid panel report prior to and during drug therapy (including dates taken)
- Reasons for discontinuation if drug therapy was discontinued
If the clinical criteria for lipotropics, apo-B inhibitor drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for lipotropics, apo-B inhibitor drugs may be approved for up to 365 days. Renewal PA requests for members who have HoFH must include supporting clinical information and copies of the member's current medical records demonstrating evidence of LDL reduction of at least 30 percent from pre-treatment baseline or a decrease to 160 mg/dL or less. Members also must continue to take the maximized LDL-lowering treatment regimen during treatment with the lipotropics, apo-B inhibitor drug.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. A copy of the current lipid panel report (within the past 30 days) must be included with the PA request. Topic #7817 Lipotropics, Omega-3 Acids
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
PA is required for non-preferred lipotropics, omega-3 acids.
PA requests for non-preferred lipotropics, omega-3 acids must be completed, signed, and dated by the prescriber. PA requests for non-preferred lipotropics, omega-3 acids must be submitted using the Prior Authorization Drug Attachment for Lipotropics, Omega-3 Acids form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. The prescriber should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Lipotropics, Omega-3 Acids form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred lipotropics, omega-3 acids may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval, including what may not be considered criteria to support the need for a drug.
Conditions for Which PA Requests for Use of Non-Preferred Lipotropics, Omega-3 Acids Will Be Considered for Review
ForwardHealth will only consider PA requests for non-preferred lipotropics, omega-3 acids to treat the following identified clinical conditions:
- Severe hypertriglyceridemia
- ASCVD risk reduction
Clinical Criteria for Non-Preferred Lipotropics, Omega-3 Acids for Severe Hypertriglyceridemia
Clinical criteria for approval of a PA request for non-preferred lipotropics, omega-3 acids for severe hypertriglyceridemia are all of the following:
- The member has a current or prior triglyceride level of 500mg/dL or greater.
- The member has taken the maximum dose of a preferred lipotropic, omega-3 acid for at least three consecutive months and experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction.
A current lipid panel report completed within the past 30 days must be submitted with all PA requests.
If the clinical criteria for non-preferred lipotropics, omega-3 acids for severe hypertriglyceridemia are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests may be approved for up to 365 days if the member has been adherent with the prescribed treatment regimen and had a reduction in their triglyceride level compared to their baseline prior to the initiation of a non-preferred lipotropics, omega-3 acid.
Clinical Criteria for Non-Preferred Lipotropics, Omega-3 Acids for Atherosclerotic Cardiovascular Disease Risk Reduction
Clinical criteria for approval of a PA request for non-preferred lipotropics, omega-3 acids for ASCVD risk reduction are all of the following:
- The member must have taken a maximized statin regimen for at least three consecutive months with failure to reach a triglyceride level of less than 150 mg/dL. The member must continue to take the maximized statin regimen along with the non-preferred lipotropic, omega-3 acid.
- One of the following is true:
- The member has clinical ASCVD, as evidenced by one of the following:
- The member has CAD, which is supported by a history of myocardial infarction (heart attack), coronary revascularization, or angina pectoris.
- The member has a history of stroke.
- The member has symptomatic peripheral arterial disease as evidenced by one of the following:
- Intermittent claudication with an ABI of less than or equal to 0.9
- Peripheral arterial revascularization procedure or amputation due to atherosclerotic disease.
- The member has diabetes mellitus and two or more of the following ASCVD risk factors:
- Congestive heart failure
- Current smoker
- eGFR less than 60 mL/min/1.73 m2
- Hypertension
- Obesity
A current lipid panel report completed within the past 30 days must be submitted with all PA requests.
If the clinical criteria for non-preferred lipotropics, omega-3 acids for ASCVD risk reduction are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for non-preferred lipotropics, omega-3 acids for ASCVD risk reduction may be approved for up to 365 days. Members must also continue to take the maximized statin treatment regimen during treatment with the non-preferred lipotropics, omega-3 acid. Topic #23717 Lipotropics, Other
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Redemplo and Tryngolza
Redemplo and Tryngolza require clinical PA.
PA requests for Redemplo or Tryngolza must be completed, signed, and dated by the prescriber. PA requests for Redemplo or Tryngolza must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Redemplo or Tryngolza may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Redemplo and Tryngolza
Clinical criteria that must be documented for approval of a PA request for Redemplo or Tryngolza are all of the following:
- The requested drug must be prescribed in a dose and manner consistent with FDA-approved product labeling.
- The member has FCS as confirmed by genetic testing. A copy of the genetic testing results must be submitted with the PA request.
- The member will use the requested drug in conjunction with a low-fat diet.
- The prescription is written by a specialist in lipid management.
- The member has a current triglyceride level of 880 mg/dL or greater.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Redemplo or Tryngolza. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- The member's current treatment plan
- A current lipid panel report completed within the past 30 days
If the clinical criteria for Redemplo or Tryngolza are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Redemplo or Tryngolza may be approved for up to 365 days. Renewal PA requests must include supporting clinical information and copies of the member's current medical records demonstrating a reduction in the member's triglyceride level compared to their baseline prior to the initiation of Redemplo or Tryngolza. All renewal PA requests require the member to be adherent with the prescribed treatment regimen. A copy of the current lipid panel report (within the past 30 days) must be included with the PA request. Topic #18737 Lipotropics, PCSK9 Inhibitors
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
PA is required for all lipotropics, PCSK9 inhibitor drugs, including preferred lipotropics, PCSK9 inhibitor drugs.
PA requests for lipotropics, PCSK9 inhibitor drugs must be completed, signed, and dated by the prescriber. PA requests for lipotropics, PCSK9 inhibitor drugs must be submitted using the Prior Authorization Drug Attachment for Lipotropics, PCSK9 Inhibitors form. Clinical documentation supporting the use of a lipotropics, PCSK9 inhibitor drug must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for Lipotropics, PCSK9 Inhibitors form and a completed PA/RF to ForwardHealth.
PA requests for lipotropics, PCSK9 inhibitor drugs may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval, including what may not be considered criteria to support the need for a drug.
Conditions for Which PA Requests for Use of Lipotropics, PCSK9 Inhibitor Drugs Will Be Considered for Review
ForwardHealth will only consider PA requests for PCSK9 inhibitor drugs to treat the following identified clinical conditions:
ForwardHealth will approve up to one ACL inhibitor or one PCSK9 inhibitor at a time per member. ForwardHealth does not cover treatment with more than one ACL inhibitor and/or PCSK9 inhibitor.
Clinical Criteria for Lipotropics, PCSK9 Inhibitor Drugs for Members With Clinical Atherosclerotic Cardiovascular Disease
Clinical criteria that must be documented for approval of a PA request for lipotropics, PCSK9 inhibitor drugs for members with clinical ASCVD are all of the following:
- The member has clinical ASCVD, as evidenced by one of the following:
- The member has CAD, which is supported by a history of myocardial infarction (heart attack), coronary revascularization, or angina pectoris.
- The member has a history of stroke.
- The member has symptomatic peripheral arterial disease as evidenced by one of the following:
- Intermittent claudication with an ABI of less than or equal to 0.9
- Peripheral arterial revascularization procedure or amputation due to atherosclerotic disease
- One of the following is true:
- The member is currently taking a statin.
- The member is unable to take a statin, as evidenced by experiencing an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with at least three statins.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for lipotropics, PCSK9 inhibitor drugs. The supporting clinical information and medical records must document the following:
- Evidence that the member has clinical ASCVD
- Documentation of the member's current and previous lipid-lowering drug therapies, including the following for each trial:
- Drug name(s) and dosage
- Dates taken
- Reasons for discontinuation if drug therapy was discontinued
Note: For PA requests for non-preferred lipotropics, PCSK9 inhibitor drugs, the member must have taken a preferred lipotropics, PCSK9 inhibitor drug and experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction.
Initial and Renewal PA Requests for Lipotropics, PCSK9 Inhibitor Drugs for Members With Clinical Atherosclerotic Cardiovascular Disease
If the clinical criteria for lipotropics, PCSK9 inhibitor drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for lipotropics, PCSK9 inhibitor drugs may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
Clinical Criteria for Lipotropics, PCSK9 Inhibitor Drugs for Members With Heterozygous Familial Hypercholesterolemia
Clinical criteria that must be documented for approval of a PA request for lipotropics, PCSK9 inhibitor drugs for members with HeFH are all of the following:
- The member has been diagnosed by a specialist in cardiology or lipid management.
- The member has HeFH, as evidenced by clinical documentation that supports a definitive diagnosis of HeFH using either WHO criteria (Dutch Lipid Clinic Network clinical criteria with a score greater than eight) or Simon Broome diagnostic criteria.
- The member attempted to maximize treatment with statins prior to requesting a lipotropics, PCSK9 inhibitor drug. The member must have taken a maximized statin regimen for at least three continuous months with failure to reach an LDL less than or equal to 100 mg/dL. (Note: Members who are not taking a maximized statin regimen, which includes atorvastatin, rosuvastatin, or simvastatin, are required to attempt a second statin in order to establish a maximum treatment regimen.)
- The member must continue to take the maximized statin regimen during treatment with the lipotropics, PCSK9 inhibitor drug unless the member is statin intolerant. Statin intolerance must be established through trials with at least three different statins (with one regimen containing pravastatin, fluvastatin, or rosuvastatin).
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for lipotropics, PCSK9 inhibitor drugs. The supporting clinical information and medical records must document the following:
- Evidence that the member has HeFH
- A current lipid panel lab report
- Documentation of the member's current and previous lipid-lowering drug therapies, including the following for each trial:
- Drug name(s) and dosage
- Dates taken
- Lipid panel report prior to and during drug therapy (including dates taken)
- Reasons for discontinuation if drug therapy was discontinued
Note: For PA requests for non-preferred lipotropics, PCSK9 inhibitor drugs, the member must have taken a preferred lipotropics, PCSK9 inhibitor drug concurrently with a maximized statin regimen (if tolerant) for at least three continuous months with failure to reach an LDL less than or equal to 100 mg/dL.
Initial and Renewal PA Requests for Lipotropics, PCSK9 Inhibitor Drugs for Members With Heterozygous Familial Hypercholesterolemia
If the clinical criteria for lipotropics, PCSK9 inhibitor drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for lipotropics, PCSK9 inhibitor drugs may be approved for up to 365 days. Renewal PA requests for members who have HeFH must include supporting clinical information and copies of the member's current medical records demonstrating evidence of LDL reduction of at least 30 percent from pre-treatment baseline or a decrease to 130 mg/dL or less. Members also must continue to take the maximized statin treatment regimen (if tolerant) during treatment with the lipotropics, PCSK9 inhibitor drug.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. A copy of the current lipid panel report (within the past 30 days) must be included with the PA request.
Clinical Criteria for Lipotropics, PCSK9 Inhibitor Drugs for Members With Homozygous Familial Hypercholesterolemia
Clinical criteria that must be documented for approval of a PA request for lipotropics, PCSK9 inhibitor drugs for members with HoFH are all of the following:
- One of the following is true:
- The member has genetic confirmation of two of the following mutant alleles at the LDL receptor:
- Apo-B
- PCSK9
- Autosomal recessive hypercholesterolemia adaptor protein gene locus
- The member has an untreated LDL-C greater than 500 mg/dL or a total treated LDL-C greater than or equal to 300 mg/dL and one of the following:
- Cutaneous tendinous xanthoma(s) before 10 years of age
- Untreated LDL-C levels of greater than or equal to 190 mg/dL in both parents
- The member must have attempted to maximize treatment with LDL-lowering therapies prior to requesting a lipotropics, PCSK9 inhibitor drug. The member must have received maximized LDL-lowering therapies for at least three continuous months with failure to reach an LDL level of 130 mg/dL or less.
- The member must continue to take the maximized LDL-lowering therapies during treatment with the lipotropics, PCSK9 inhibitor drug.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for lipotropics, PCSK9 inhibitor drugs. The supporting clinical information and medical records must document the following:
- Evidence that the member has HoFH
- A current lipid panel lab report
- Documentation of the member's current and previous lipid-lowering drug therapies, including the following for each trial:
- Drug name(s) and dosage
- Dates taken
- Lipid panel report prior to and during drug therapy (including dates taken)
- Reasons for discontinuation if drug therapy was discontinued
Note: For PA requests for non-preferred lipotropics, PCSK9 inhibitor drugs, the member must have taken a preferred lipotropics, PCSK9 inhibitor drug concurrently with maximized LDL-lowering therapies for at least three continuous months with failure to reach an LDL less than or equal to 130 mg/dL.
Initial and Renewal PA Requests for Lipotropics, PCSK9 Inhibitor Drugs for Members With Homozygous Familial Hypercholesterolemia
If the clinical criteria for lipotropics, PCSK9 inhibitor drugs are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for lipotropics, PCSK9 inhibitor drugs may be approved for up to 365 days. Renewal PA requests for members who have HoFH must include supporting clinical information and copies of the member's current medical records demonstrating evidence of LDL reduction of at least 30 percent from pre-treatment baseline or a decrease to 160 mg/dL or less. Members also must continue to take the maximized LDL-lowering therapies during treatment with the lipotropics, PCSK9 inhibitor drug.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #10997 Multiple Sclerosis Agents
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Clinical PA is required for non-preferred MS agents.
PA requests for non-preferred MS agents must be completed, signed, and dated by the prescriber. PA requests for non-preferred MS agents must be submitted on the Prior Authorization Drug Attachment for MS Agents form. Clinical documentation supporting the use of non-preferred MS agents must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for MS Agents form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred MS agents may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
For information about general ForwardHealth PA policy for drugs that require PA approval, prescribers and pharmacy providers may refer to the Standard Pharmacy Policy for Covered and Noncovered Drugs topic. Providers may also refer to this topic for information about what may not be considered criteria to support the need for a drug.
Clinical Criteria for Non-Preferred Multiple Sclerosis Agents
Preferred MS agents do not require PA.
Clinical criteria for approval of an initial PA request for a non-preferred MS agent are all of the following:
- The member has taken two preferred MS agents and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why a non-preferred MS agent is being requested.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for non-preferred MS agents. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
Initial and Renewal PA Requests for Non-Preferred MS Agents
If the clinical criteria for non-preferred MS agents are met, initial PA requests may be approved for up to 183 days. Renewal PA requests may be approved for up to 365 days.
Renewal PA requests for non-preferred MS agents must include copies of the member's current medical records demonstrating that the member's MS is stable and well-controlled without having disease-progressing symptoms.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #22900 Multiple Sclerosis Agents, Interferons
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Non-preferred MS
agents, interferons require PA.
PA requests for non-preferred MS agents, interferons must be completed, signed, and dated by the prescriber. PA requests for non-preferred MS agents, interferons must be submitted on the
Prior Authorization Drug Attachment for MS Agents, Interferons form. Clinical documentation supporting the use of non-preferred MS agents, interferons must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed Prior Authorization Drug Attachment for MS Agents, Interferons form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred MS agents, interferons may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Multiple Sclerosis Agents, Interferons
Clinical criteria for approval of an initial PA request for non-preferred MS agents, interferons are all of the following:
- The member has taken two preferred MS agents, interferons and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The prescriber has indicated the clinical reason(s) why a non-preferred MS agents, interferon is being requested.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for non-preferred MS agents, interferons. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
Initial and Renewal PA Requests for Non-Preferred Multiple Sclerosis Agents, Interferons
If the clinical criteria for non-preferred MS agents, interferons are met, initial PA requests may be approved for up to 183 days. Renewal PA requests may be approved for up to 365 days.
Renewal PA requests for non-preferred MS agents, interferons must include copies of the member's current medical records demonstrating that the member's MS is stable and well-controlled without having disease-progressing symptoms.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #22897 Multiple Sclerosis Agents, Other
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Glatopa
PA requests for Glatopa must be completed, signed, and dated by the prescriber. PA requests for Glatopa must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Glatopa may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Glatopa
The prescriber must submit detailed clinical justification for prescribing Glatopa instead of glatiramer. This clinical information must document why the member cannot use glatiramer, including why it is medically necessary that the member receive Glatopa instead of glatiramer.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Glatopa. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
Initial and Renewal PA Requests for Glatopa
If the clinical criteria for Glatopa are met, initial PA requests may be approved for up to 183 days. Renewal PA requests may be approved for up to 365 days.
Renewal PA requests for Glatopa must include copies of the member's current medical records demonstrating that the member's MS is stable and well-controlled without having disease-progressing symptoms.
All renewal PA requests for Glatopa require the member to be adherent with the prescribed treatment regimen. Topic #22218 Non-Preferred Drugs That Use the Prior Authorization/Preferred Drug List Exemption Request Form
PA requests for non-preferred drugs submitted with the PA/PDL Exemption Request form must be completed, signed, and dated by the prescriber. PA requests for non-preferred drugs designated to use the PA/PDL Exemption Request form must be submitted using the PA/PDL Exemption Request form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/PDL Exemption Request form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred drugs submitted with the PA/PDL Exemption Request form may be submitted using the STAT-PA system, on the Portal, by fax, or by mail.
For information about general ForwardHealth PA policy for drugs that require PA approval, prescribers and pharmacy providers may refer to the Standard Pharmacy Policy for Covered and Noncovered Drugs topic. Providers may also refer to this topic for information about what may not be considered criteria to support the need for a drug.
Clinical Criteria for Non-Preferred Drugs Submitted With the Prior Authorization/Preferred Drug List Exemption Request Form
Clinical criteria for approval of a PA request for a non-preferred drug submitted with the PA/PDL Exemption Request form are at least one of the following:
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with at least one of the preferred drugs from the same PDL drug class as the drug being requested.
- There is a clinically significant drug interaction between another drug the member is taking and at least one of the preferred drugs from the same PDL drug class as the drug being requested.
- The member has a medical condition(s) that prevents the use of at least one of the preferred drugs from the same PDL drug class as the drug being requested.
Alternate Clinical Criteria for Non-Preferred Drugs in Eligible Drug Classes Only
The following drug classes have alternate clinical criteria that may be considered if the member does not meet the previously listed clinical criteria for non-preferred drugs submitted with the PA/PDL Exemption Request form:
- Alzheimer's agents drug class
- Anticonvulsants drug class
- Antidepressants, other drug class
- Antidepressants, SSRI drug class
- Antiparkinson's agents drug class
- Antipsychotics drug class
- HIV/AIDS drug class
- Pulmonary arterial hypertension drug class
Alternate clinical criteria may be considered if a member does not meet the previously listed clinical criteria for non-preferred drugs. Alternate clinical criteria are one of the following:
- The member is new to ForwardHealth (the member has been granted eligibility for ForwardHealth within the past month) and has taken the requested non-preferred drug continuously for the last 30 days or longer with a measurable therapeutic response.
- The member had an approved PA request for the non-preferred drug issued by ForwardHealth that recently expired, and the member has taken the requested non-preferred drug continuously for the last 30 days or longer and had a measurable therapeutic response.
- The member was recently discharged from an inpatient stay in which the member was stabilized on the non-preferred drug being requested.
Topic #2328 Non-Steroidal Anti-Inflammatory Drugs
PA requests for non-preferred NSAIDs must be completed and signed by the prescriber and submitted using the PA/PDL for NSAIDs form.
PA requests for non-preferred NSAIDs may be submitted using the STAT-PA system, on the Portal, by fax, or by mail.
Clinical Criterion for NSAIDs
The clinical criterion for approval of a PA request for a non-preferred NSAID requires that the member has experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction with at least two preferred NSAIDs. (The two preferred NSAIDs cannot be ibuprofen or naproxen.)
If the clinical criterion for a non-preferred NSAID is met, PA requests may be approved for up to 365 days. Topic #3509 Overview of Drug Legacy Exemptions
When applicable, ForwardHealth will designate either a generic or brand name drug with a legacy exemption for specific, affected BadgerCare Plus, Medicaid, or SeniorCare members. Affected BadgerCare Plus, Medicaid, or SeniorCare members are allowed to receive a legacy exemption for a drug as long as the drug remains non-preferred. A legacy exemption will not be applied to a drug that requires BBG or BMN PA. If BBG is applied to a generic drug with a legacy exemption, then the brand name drug will have the legacy exemption. If BMN is applied to a brand name drug with a legacy exemption, then the generic drug will have the legacy exemption.
When the generic equivalent for a drug with a legacy exemption becomes available, ForwardHealth will evaluate the relative cost of the generic and brand name drugs and determine whether the brand name or generic drug are designated with a legacy exemption. If the corresponding generic drug or brand name drug become preferred, the legacy exemption will be discontinued.
Members will no longer be allowed to receive a drug with a legacy exemption if one of the following is true:
- Members without other primary insurance on file with ForwardHealth who have had no claim activity for the legacy exemption drug during the last six months
- Members with other primary insurance on file with ForwardHealth who have had no claim activity for the legacy exemption drug during the last 12 months
When a pharmacy claim is submitted in real-time for a member who is not eligible to receive a drug with a legacy exemption, the pharmacy will receive an EOB code and an NCPDP reject code indicating a denial in the claim response informing the pharmacy that the drug requires PA.
Note: A member's legacy exemption for those designated drugs overrides the PDL PA policy only. Other policies continue to apply, such as member enrollment eligibility, diagnosis restriction, quantity limits, and noncovered service policies. Topic #8877 Proton Pump Inhibitors
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Clinical PA is required for non-preferred PPIs.
PA requests for non-preferred PPIs must be completed, signed, and dated by the prescriber. PA requests for non-preferred PPIs must be submitted on the PA/PDL for PPIs form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the PA/PDL for PPIs form and a completed PA/RF to ForwardHealth.
PA requests for non-preferred PPIs may be submitted using the STAT-PA system, on the Portal, by fax, or by mail.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Non-Preferred Proton Pump Inhibitors
Clinical criteria for approval of a PA request for a non-preferred PPI requires one of the following to be true:
- The member has experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with at least two preferred PPIs.
- The member has a medical condition(s) that prevents the use of the preferred PPIs.
If the clinical criteria for non-preferred PPIs are met, PA requests may be approved for up to 365 days.Topic #23337 Pulmonary Arterial Hypertension
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Opsynvi requires clinical PA.
PA requests for Opsynvi must be completed, signed, and dated by the prescriber. PA requests for Opsynvi must be submitted using using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Opsynvi may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval, including what may not be considered criteria to support the need for a drug.
Clinical Criteria for Opsynvi
The clinical criteria that must be documented for approval of a PA request for Opsynvi includes both of the following:
- The prescriber has submitted detailed clinical justification for prescribing Opsynvi instead of the combination of tadalafil (Adcirca) and macitentan (Opsumit).
- The clinical information must document why the member cannot use the combination of tadalafil (Adcirca) and macitentan (Opsumit), including why it is medically necessary that the member receive Opsynvi instead of the combination of tadalafil (Adcirca) and macitentan (Opsumit).
Clinical documentation and medical records must be submitted with the PA request to support the need for Opsynvi. Initial PA requests for Opsynvi may be approved for up to 183 days.
Renewal PA requests may be approved for up to 365 days. Medical records must be submitted demonstrating clinical improvement and must reflect member compliance with Opsynvi. Topic #18817 Sedative Hypnotics
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
All orexin receptor antagonists in the sedative hypnotics drug class are non-preferred drugs that require PA.
PA requests for orexin receptor antagonists must be completed, signed, and dated by the prescriber. PA requests for orexin receptor antagonists must be submitted using the PA/PDL for Orexin Receptor Antagonists form.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/PDL for Orexin Receptor Antagonists form and a completed PA/RF to ForwardHealth.
PA requests for orexin receptor antagonists may be submitted using the STAT-PA system, on the Portal, by fax, or by mail.
For information about general ForwardHealth PA policy for drugs that require PA approval, prescribers and pharmacy providers may refer to the Standard Pharmacy Policy for Covered and Noncovered Drugs topic. Providers may also refer to this topic for information about what may not be considered criteria to support the need for a drug.
Clinical Criteria for Orexin Receptor Antagonists
Clinical criteria for approval of a PA request for orexin receptor antagonists are all of the following:
- The member's age is consistent with the FDA-approved product labeling for the drug requested.
- The member does not have narcolepsy.
- At least one of the following is true:
- The member has experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction with at least two preferred drugs from the sedative hypnotics drug class.
- The member has a medical history of substance abuse or misuse.
If the clinical criteria for orexin receptor antagonists are met, PA requests may be approved for up to 365 days. Topic #16357 Stimulants
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
Note: Some drugs in the stimulants drug class are designated as legacy stimulant drugs. For more information about designated legacy drugs in this drug class, providers may refer to the Legacy Exemptions for Stimulant Drugs topic.
Drugs in this class are diagnosis restricted. A ForwardHealth-allowed diagnosis code must be indicated on claims for all stimulant drugs.
PA requests for non-preferred stimulants (except for methamphetamine) must be submitted on the PA/PDL for Non-Preferred Stimulants form.
Adderall, Dexedrine, dextroamphetamine-amphetamine, dextroamphetamine solution, dextroamphetamine tablets, Evekeo, and Zenzedi are non-preferred drugs; however, PA for Adderall, Dexedrine, dextroamphetamine-amphetamine; dextroamphetamine solution, dextroamphetamine tablets, Evekeo, or Zenzedi is not required for members who are 6 years of age or younger. Once a member reaches 7 years of age, PA will be required.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Non-Preferred Stimulants
Clinical PA is required for non-preferred stimulants.
Clinical criteria for approval of a PA request for a non-preferred stimulant are both of the following:
- At least one of the following is true:
- The member took Vyvanse for at least 60 consecutive days with a minimum of one dosage adjustment and experienced an unsatisfactory therapeutic response.
- The member took Vyvanse and experienced a clinically significant adverse drug reaction.
- At least one of the following is true:
- The member took a methylphenidate stimulant for at least 60 consecutive days with a minimum of one dosage adjustment and experienced an unsatisfactory therapeutic response.
- The member took a methylphenidate stimulant and experienced a clinically significant adverse drug reaction.
- The member took a dexmethylphenidate stimulant for at least 60 consecutive days with a minimum of one dosage adjustment and experienced an unsatisfactory therapeutic response.
- The member took a dexmethylphenidate stimulant and experienced a clinically significant adverse drug reaction.
If the clinical criteria for non-preferred Stimulants are met, PA requests may be approved for up to 365 days.
Submitting PA Requests for Non-Preferred Stimulants
PA requests for non-preferred stimulants (except for methamphetamine) must be completed and signed by the prescriber and must be submitted using the PA/PDL for Non-Preferred Stimulants form.
PA requests for non-preferred stimulants (except for amphetamine ER ODT, lisdexamfetamine caps and chew, or methamphetamine) may be submitted using the STAT-PA system, on the Portal, by fax, or by mail.
Methamphetamine
PA requests for methamphetamine should be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form and the PA/RF.
PA requests for methamphetamine may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Clinical Criteria for Methamphetamine
Clinical criteria that must be documented for approval of a PA request for methamphetamine are all of the following:
- The member is 6–17 years of age.
- The member has had neuropsychological/psychological assessment that supports a diagnosis of ADHD.
- The prescriber has provided documented and objective evidence (supplied by third-party, unrelated adult observers) of functioning deficits secondary to ADHD in at least two of the following domains of functioning:
- Home
- Work
- School
- Community
- At least one of the following is true:
- The member took Vyvanse for at least 60 consecutive days with a minimum of one dosage adjustment and experienced an unsatisfactory therapeutic response.
- The member took Vyvanse and experienced a clinically significant adverse drug reaction.
- At least one of the following is true:
- The member took a methylphenidate stimulant for at least 60 consecutive days with a minimum of one dosage adjustment and experienced an unsatisfactory therapeutic response.
- The member took a methylphenidate stimulant and experienced a clinically significant adverse drug reaction.
- At least one of the following is true:
- The member took a dexmethylphenidate stimulant for at least 60 consecutive days with a minimum of one dosage adjustment and experienced an unsatisfactory therapeutic response.
- The member took a dexmethylphenidate stimulant and experienced a clinically significant adverse drug reaction.
PA requests must include medical records to support the above criteria have been met, including documentation of all past and current treatments that have been attempted (both pharmacologic and non-pharmacologic).
If clinical criteria for methamphetamine are met, PA requests will be approved for up to 183 days.
Stimulants and Stimulants, Related Agents – Wake Promoting Quantity Limits
Quantity limits apply to all preferred and non-preferred stimulants, with the exception of liquid dosage forms and all preferred and non-preferred stimulants, related agents – wake promoting drugs. When a claim is submitted with a quantity that exceeds the limit, the claim will be denied.
The following applies to drugs in the stimulants drug class and the stimulants, related agents – wake promoting drug class:
- All preferred and non-preferred stimulants (with the exception of liquid dosage forms) and all preferred and non-preferred stimulants, related agents – wake promoting drugs have a cumulative quantity limit of 136 units per month.
- Members are limited to a combined total of 136 units (tablets, capsules, or patches) per month, an exception being members with narcolepsy.
- Members with narcolepsy are allowed a quantity limit override to receive up to 136 units of stimulants in addition to the drug-specific quantity limits for stimulants, related – agents wake promoting drugs.
- Several drugs also have a drug-specific quantity limit per claim:
- Armodafinil 150 mg, 200 mg, and 250 mg; Azstarys; Sunosi 75 mg and 150 mg; and Xelstrym have a drug-specific quantity limit of 34 units per claim.
- Modafinil 200 mg has a drug-specific quantity limit of 68 units per claim.
- Armodafinil 50 mg and modafinil 100 mg have drug-specific quantity limit of 136 units per claim.
The Quantity Limit Drugs and Diabetic Supplies data table contains the most current quantity limits.
Quantity Limit Overrides
Prior to requesting a quantity limit override, the pharmacy provider should contact the prescriber to determine whether it is medically appropriate for a member to exceed the quantity limit. If it is medically appropriate for a member to exceed a quantity limit, pharmacy providers may request an override by calling the DAPO Center. Pharmacy providers may request a quantity limit override for members enrolled in BadgerCare Plus, Wisconsin Medicaid, and SeniorCare.
Note: The pharmacy provider should have clinical information to support a quantity limit override when calling the DAPO Center.
A one-time quantity limit override may be considered for approval in certain situations, including:
- Lost or stolen medication
- Vacation supply
- A medication and/or dosage change ordered by the prescriber
In limited instances, other one-time or longer-term overrides may be considered for approval. The pharmacy provider should have clinical information from the prescriber when calling the DAPO Center.
Examples of when other one-time or longer-term overrides may be considered include:
- The prescriber has identified a specific medical need or clinical condition that requires a larger quantity of the medication.
- The prescriber is reducing, consolidating, or tapering the dose over an extended period.
In addition, pharmacy providers may request a quantity limit policy override for members with narcolepsy. Members with narcolepsy are allowed a quantity limit override to receive up to 136 units of stimulants in addition to the drug-specific quantity limits for stimulants, related agents – wake promoting drugs. Topic #19878 Stimulants, Related Agents – Wake Promoting
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
PA is not required for preferred drugs in the stimulants, related agents – wake promoting drug class.
Clinical PA is required for non-preferred stimulants, related agents – wake promoting drugs.
Non-Preferred Stimulants, Related Agents – Wake Promoting
PA requests for non-preferred drugs in the stimulants, related agents – wake promoting class must be completed, signed, and dated by the prescriber. The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
PA requests for non-preferred drugs in the stimulants, related agents – wake promoting class must be submitted using the Prior Authorization Drug Attachment for Non-Preferred Stimulants, Related Agents—Wake Promoting form and the PA/RF.
PA requests for non-preferred drugs in the stimulants, related agents – wake promoting class may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
For information about general ForwardHealth PA policy for drugs that require PA approval, prescribers and pharmacy providers may refer to the Standard Pharmacy Policy for Covered and Noncovered Drugs topic. Providers may also refer to this topic for information about what may not be considered criteria to support the need for a drug.
Conditions for Which PA Requests for Non-Preferred Stimulants, Related Agents – Wake Promoting Drugs Will Be Considered for Review
PA requests for non-preferred drugs in the stimulants, related agents – wake promoting class will only be approved for use to treat the following identified clinical conditions:
- EDS associated with narcolepsy
- EDS associated with OSA
Clinical Criteria for Non-Preferred Stimulants, Related Agents – Wake Promoting Drugs for Members With Narcolepsy
Clinical criteria for approval of PA requests for non-preferred drugs in the stimulants, related agents – wake promoting class for members with narcolepsy are all of the following:
- The member is 18 years of age or older.
- The member has EDS associated with narcolepsy.
- An overnight PSG sleep study and MSLT have been performed for the member using standard protocols, and the prescribing provider has submitted medical record documentation supporting a clinical correlation between the test results and a diagnosis of narcolepsy.
- The overnight PSG test results and provider interpretation have been submitted with the PA request and include documentation of the following:
- The member's total sleep time was at least 360 minutes.
- The member experienced minimal sleep interruptions (for example, respiratory events or periodic leg movements).
- The provider interpretation indicates that an adequate night's sleep was achieved.
The MSLT results and provider interpretation have been submitted with the PA request and include documentation of the following:
- The MSLT was conducted the morning after the overnight PSG.
- The average sleep latency for all naps was eight minutes or less.
- The member achieved at least two SOREMPs. (A SOREMP within 15 minutes of sleep onset on the preceding nocturnal PSG may replace one of the SOREMPs on the MSLT.)
The member is not currently taking any other drugs in the stimulants, related agents – wake promoting class.
The member is not taking any sedative hypnotics.
For members currently taking CNS depressants (for example, anxiolytics, barbiturates, or opioids), the prescriber has evaluated the CNS depressants and determined they are not contributing to the member's EDS.
At least one of the following is true:
- The member has tried armodafinil and experienced an unsatisfactory therapeutic response after the medication had been titrated to a maximum recommended daily dose.
- The member experienced a clinically significant adverse drug reaction with armodafinil.
- The member has a medical condition that prevents treatment with armodafinil.
- There is a clinically significant drug interaction with another medication the member is taking and armodafinil.
At least one of the following is true:
- The member has tried modafinil and experienced an unsatisfactory therapeutic response after the medication had been titrated to a maximum recommended daily dose.
- The member experienced a clinically significant adverse drug reaction with modafinil.
- The member has a medical condition that prevents treatment with modafinil.
- There is a clinically significant drug interaction with another medication the member is taking and modafinil.
If initial clinical criteria for non-preferred drugs in the stimulants, related agents – wake promoting class for members with narcolepsy are met, PA requests may be approved for up to 183 days. Renewal PA requests for non-preferred drugs in the stimulants, related agents – wake promoting class may be approved for up to 365 days.
Clinical Criteria for Non-Preferred Stimulants, Related Agents – Wake Promoting Drugs for Members With Obstructive Sleep Apnea
Clinical criteria for approval of PA requests for non-preferred drugs in the stimulants, related agents – wake promoting class for members with OSA are all of the following:
- The member is 18 years of age or older.
- The member has EDS associated with OSA.
- The member has had an overnight PSG sleep study with an AHI greater than or equal to five events per hour, confirming the member has OSA. The date of the PSG and the resulting AHI must be included with the PA request.
- The member is not currently taking any other drugs in the stimulants class or the stimulants, related agents – wake promoting class.
- The member is currently using CPAP and will continue to use CPAP in combination with the non-preferred stimulants, related agents – wake promoting drug.
- At least one of the following is true:
- The member has tried armodafinil and experienced an unsatisfactory therapeutic response after the medication had been titrated to a maximum recommended daily dose.
- The member experienced a clinically significant adverse drug reaction with armodafinil.
- The member has a medical condition that prevents treatment with armodafinil.
- There is a clinically significant drug interaction with another medication the member is taking and armodafinil.
- At least one of the following is true:
- The member has tried modafinil and experienced an unsatisfactory therapeutic response after the medication had been titrated to a maximum recommended daily dose.
- The member experienced a clinically significant adverse drug reaction with modafinil.
- The member has a medical condition that prevents treatment with modafinil.
- There is a clinically significant drug interaction with another medication the member is taking and modafinil.
Note: If requested by ForwardHealth, the provider is required to submit the test results and provider interpretation for the PSG.
If initial clinical criteria for non-preferred drugs in the stimulants, related agents – wake promoting class for members with OSA are met, PA requests may be approved for up to 183 days. Renewal PA requests for non-preferred stimulants, related agents – wake promoting drugs may be approved for up to 365 days.
Stimulants and Stimulants, Related Agents – Wake Promoting Quantity Limits
Quantity limits apply to all preferred and non-preferred stimulants, with the exception of liquid dosage forms and all preferred and non-preferred stimulants, related agents – wake promoting drugs. When a claim is submitted with a quantity that exceeds the limit, the claim will be denied.
The following applies to drugs in the stimulants drug class and the stimulants, related agents – wake promoting drug class:
- All preferred and non-preferred stimulants (with the exception of liquid dosage forms) and all preferred and non-preferred stimulants, related agents – wake promoting drugs have a cumulative quantity limit of 136 units per month.
- Members are limited to a combined total of 136 units (tablets, capsules, or patches) per month, an exception being members with narcolepsy.
- Members with narcolepsy are allowed a quantity limit override to receive up to 136 units of stimulants in addition to the drug-specific quantity limits for stimulants, related agents – wake promoting drugs.
- Several drugs also have a drug-specific quantity limit per claim:
- Armodafinil 150 mg, 200 mg, and 250 mg; Azstarys; Sunosi 75 mg and 150 mg; and Xelstrym have a drug-specific quantity limit of 34 units per claim
- Modafinil 200 mg has a drug-specific quantity limit of 68 units per claim
- Armodafinil 50 mg and modafinil 100 mg have drug-specific quantity limit of 136 units per claim
The Quantity Limit Drugs and Diabetic Supplies data table contains the most current quantity limits. Providers may refer to the Online Handbook Quantity Limits topic #3444 and Quantity Limit Drugs and Diabetic Supplies pharmacy data table on the Pharmacy Resources page of the Portal.
Quantity Limit Overrides
Prior to requesting a quantity limit override, the pharmacy provider should contact the prescriber to determine whether it is medically appropriate for a member to exceed the quantity limit. If it is medically appropriate for a member to exceed a quantity limit, pharmacy providers may request an override by calling the DAPO Center. Pharmacy providers may request a quantity limit override for members enrolled in BadgerCare Plus, Wisconsin Medicaid, and SeniorCare.
Note: The pharmacy provider should have clinical information to support a quantity limit override when calling the DAPO Center.
A one-time quantity limit override may be considered for approval in certain situations, including:
- Lost or stolen medication
- Vacation supply
- A medication and/or dosage change ordered by the prescriber
In limited instances, other one-time or longer-term overrides may be considered for approval. The pharmacy provider should have clinical information from the prescriber when calling the DAPO Center.
Examples of when other one-time or longer-term overrides may be considered include:
- The prescriber has identified a specific medical need or clinical condition that requires a larger quantity of the medication.
- The prescriber is reducing, consolidating, or tapering the dose over an extended period.
In addition, pharmacy providers may request a quantity limit policy override for members with narcolepsy. Members with narcolepsy are allowed a quantity limit override to receive up to 136 units of stimulants in addition to the drug-specific quantity limits for stimulants, related agents – wake promoting drugs. Topic #22578 Ulcerative Colitis
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
PA is required for non-preferred drugs.
Velsipity and Zeposia
Velsipity and Zeposia for members with ulcerative colitis require clinical PA.
Note: Zeposia is also a non-preferred drug in the MS agents drug class. PA requests for Zeposia, as a non-preferred MS agent, must be submitted with the Prior Authorization Drug Attachment for MS Agents form.
PA requests for Velsipity or Zeposia for members with ulcerative colitis must be completed, signed, and dated by the prescriber. PA requests for Velsipity or Zeposia for members with ulcerative colitis must be submitted using Section VI (Clinical Information for Drugs With Specific Criteria Addressed in the ForwardHealth Online Handbook) of the PA/DGA form. Clinical documentation supporting the use of Velsipity or Zeposia must be submitted with the PA request.
The PA form must be sent to the pharmacy where the prescription will be filled. The prescriber may send the PA form to the pharmacy, or the member may carry the PA form with the prescription to the pharmacy. The pharmacy provider will use the completed PA form to submit a PA request to ForwardHealth. Prescribers should not submit the PA form to ForwardHealth.
Pharmacy providers are required to submit the completed PA/DGA form and a completed PA/RF to ForwardHealth.
PA requests for Velsipity or Zeposia for members with ulcerative colitis may be submitted on the Portal, by fax, or by mail (but not using the STAT-PA system).
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Velsipity and Zeposia for Members With Ulcerative Colitis
Clinical criteria that must be documented for approval of a PA request for Velsipity or Zeposia for members with ulcerative colitis are all of the following:
- The member has moderate to severe ulcerative colitis.
- The prescription is written by a gastroenterologist or through a gastroenterology consultation.
- Two of the following are true:
- The member has taken Hadlima or Humira for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Selarsdi subQ or Steqeyma subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Simponi subQ for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
- The member has taken Xeljanz or Xeljanz XR for at least three consecutive months and experienced an unsatisfactory therapeutic response or experienced a clinically significant adverse drug reaction.
Supporting clinical information and a copy of the member's current medical records must be submitted with all PA requests for Velsipity or Zeposia for members with ulcerative colitis. The supporting clinical information and medical records must document the following:
- The member's medical condition being treated
- Details regarding previous medication use
- The member's current treatment plan
If the clinical criteria for Velsipity or Zeposia for members with ulcerative colitis are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests for Velsipity or Zeposia for members with ulcerative colitis may be approved for up to 365 days. Renewal PA requests for members who have ulcerative colitis must include supporting clinical information and copies of the member's current medical records demonstrating that the member had a significant reduction in symptoms compared to the member's baseline prior to the initiation of the non-preferred drug.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen. Topic #24303 Weight Management Agents
Note: The Preferred Drug List Quick Reference provides the most current list of preferred and non-preferred drugs in this drug class.
PA is required for all weight management agents, including preferred weight management agents. Weight management agents that are not included in this PDL drug class or do not have separate established clinical criteria are noncovered services.
Weight management agents are covered for dual eligibles enrolled in a Medicare Part D PDP.
PA requests for weight management agents will only be approved for one weight management agent per member at a time. ForwardHealth does not cover treatment with more than one weight management agent at a time.
Submitting PA Requests for Weight Management Agents
Prescribers, or their designees, must request PA for weight management agents using one of these options:
Pharmacy providers may not request PA for weight management agents.
A prescriber, or their designee, should have all PA information completed before calling the DAPO Center to obtain PA.
Prescribers are required to retain a completed copy of the Prior Authorization Drug Attachment for Weight Management Agents form and any supporting documentation.
If a prescriber or their designee chooses to submit a paper PA request for weight management agents by fax or mail, the following must be completed and submitted to ForwardHealth:
- PA/RF
- Prior Authorization Drug Attachment for Weight Management Agents form
- Supporting documentation, as appropriate
The Prior Authorization Fax Cover Sheet is available on the Forms page of the Portal for prescribers or their designees submitting the forms and documentation by fax.
As a reminder, prescribers must complete, sign, and date the PA/RF and the Prior Authorization Drug Attachment for Weight Management Agents form when submitting the PA request on paper.
Information is available about general ForwardHealth policy for drugs that require PA approval. This includes what may not be considered criteria to support the need for a drug.
Clinical Criteria for Weight Management Agents
Clinical criteria for approval of a PA request for weight management agents require one of the following:
- The member has a BMI greater than or equal to 30.
- The member has a BMI greater than or equal to 27 but less than 30 and has two or more of the following risk factors:
- Dyslipidemia
- Hypertension
- Sleep apnea
- Type 2 diabetes mellitus
- Cardiovascular disease supported by a history of at least one of the following:
- Myocardial infarction (heart attack)
- Coronary revascularization
- Angina pectoris
- Stroke
- Intermittent claudication with an ABI of less than or equal to 0.9
- Peripheral arterial revascularization due to atherosclerotic disease or amputation due to atherosclerotic disease
In addition, the member must agree to follow a reduced-calorie diet and increase their physical activity.
If the clinical criteria for weight management agents are met, initial PA requests may be approved for up to 183 days.
Renewal PA requests require the member to have a reduction in BMI compared to their baseline prior to the initiation of the weight management agent. Renewal PA requests for weight management agents may be approved for up to 365 days.
All renewal PA requests require the member to be adherent with the prescribed treatment regimen.
PA renewal requests for weight management agents will not be approved if a member's BMI is below 18.5. Topic #16457 Requesting Prior Authorization for Non-preferred Diabetic Supplies
Providers may submit PA requests for non-preferred blood glucose meters and test strips. To receive PA for non-preferred blood glucose meters and test strips, members are required to meet one of the following clinical criteria:
- The member uses an insulin pump that requires the use of a non-preferred meter.
- The member has a medical condition, such as visual impairment, that requires the use of a specialized (talking) non-preferred meter.
- The member is unable to use a product from each of the preferred manufacturers, and there is clinical rationale to support the use of a non-preferred product.
If clinical criteria for non-preferred blood glucose meters and/or test strips are met, initial PA requests may be approved for up to one year.
Providers may refer to the Diabetic Supply List Quick Reference on the Pharmacy Resources page of the Providers area of the Portal for the most current list of covered preferred diabetic supplies.
Providers must submit a PA request using the Prior Authorization Drug Attachment for Blood Glucose Meters and Test Strips. PA requests may be submitted using the Portal, by fax, or by mail. Topic #15537 Diagnosis-Restricted Drugs
Prescribers are required to indicate a diagnosis on prescriptions for all drugs that are identified by ForwardHealth as diagnosis restricted. If a diagnosis is not indicated on the prescription, pharmacy providers should contact the prescriber to obtain the diagnosis and document the diagnosis on the prescription or pharmacy health care record. It is not acceptable for pharmacy providers to obtain the diagnosis from the member.
The diagnosis submitted on a claim must also be verifiable within the member's prescription record or pharmacy health care record. Upon retrospective review, ForwardHealth may seek recoupment for the payment of the prescription from the pharmacy if the prescription record or pharmacy health care record does not document that the diagnosis submitted on the claim was provided by the prescriber.
Refer to the Diagnosis Restricted Drugs data table for a list of diagnosis-restricted drugs. |